


Dr. Rawnak Sharif Shares Clinical Case: High-Risk AF Patient with Traumatic SDH
Dr. Rawnak Sharif, Resident Medical Officer at Apollo Imperial Hospital, posted on LinkedIn:
“High-Risk AF Patient with Traumatic SDH: Strategic Anticoagulation
Case Summary:
A 69-year-old male with severe ischemic cardiomyopathy (left ventricular ejection fraction 20%, chronic total occlusion) on apixaban presented after alcohol ingestion with vomiting, headache, right ear bleeding and a fall. Imaging revealed a large left-sided subdural haematoma (SDH), intracerebral and subarachnoid haemorrhage, diffuse axonal injury and right parietal/temporal fractures. Computed tomography angiography (CTA) and computed tomography venography (CTV) showed no aneurysm or vascular lesion.
Management Plan:
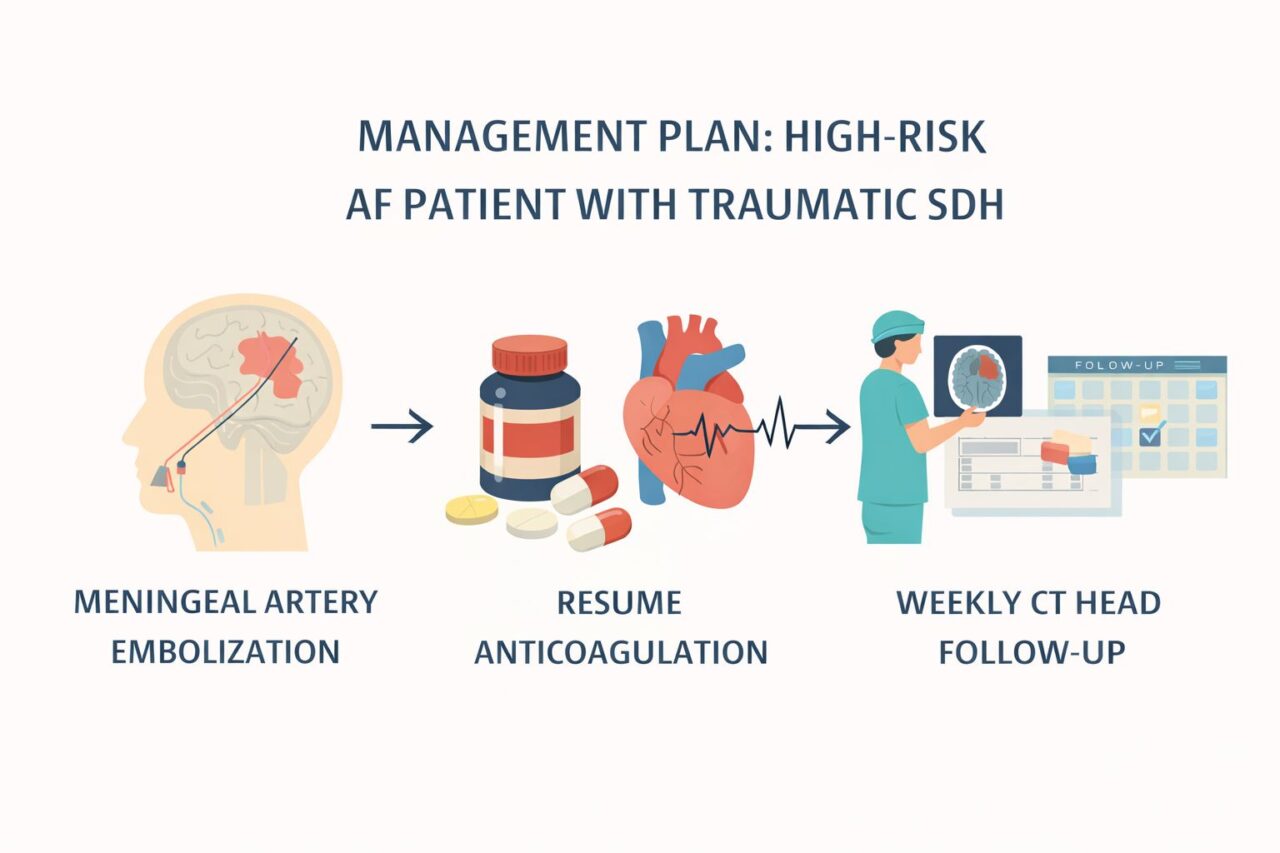
- Meningeal artery embolisation (MMAE): To seal the bleeding source.
- Resumption of apixaban post-embolisation: For atrial fibrillation stroke prevention.
- Conservative neuro care: Antiedema therapy, antiepileptics, nimodipine and vitamin K.
- Weekly CT head follow-up: Until SDH stabilisation.
Clinical Summary for Practising Doctors:
- MMAE: Is increasingly validated for acute, subacute and chronic SDH. It targets the haematoma membrane’s vascular supply to reduce recurrence and promote resolution.
- Resumption of anticoagulation or antiplatelet therapy post-MMAE: Appears safe. Studies show no significant increase in SDH recurrence or haematoma size compared with withholding therapy.
- Early resumption (approximately 1 week to 1 month): May lower thromboembolic risk without increasing bleeding complications.
- Limitations: Most evidence is retrospective; patient selection bias exists. Large prospective trials are ongoing to define optimal timing and patient subsets.
Clinical Rationale:
- Traumatic SDH + AF: Requires balancing haemorrhage control with thromboembolic prevention.
- Embolisation addresses the bleeding source enabling safe anticoagulation resumption.
- Multidisciplinary decision-making (neurology, neurosurgery, cardiology) is essential.
- Structured imaging follow-up guides timing and safety.
1-Minute Bedside Checklist:
- Confirm SDH stability on repeat CT scan.
- Assess thromboembolic risk (CHA₂DS₂-VASc, devices, prior events).
- Assess bleeding risk (volume, location, comorbidities).
- Plan anticoagulation timing (post-embolisation, individually tailored).
- Choose agent (DOAC preferred if eligible).
- Multidisciplinary consultation and patient counselling.
References:
- Acta Neurochir 2025 – MMAE reduces SDH recurrence.
- PubMed 39880622 – Safe anticoagulation post-MMAE.
- PMC 10249073 – Early resumption feasible.
- Trials J 2025 – RELACS RCT, timing anticoagulation post-SDH.
Takeaway:
In high-risk atrial fibrillation patients with traumatic SDH, MMA embolisation enables safe and timely resumption of anticoagulation, reducing thromboembolic risk while minimising rebleeding. Weekly imaging and multidisciplinary care are key to optimal outcomes.”
Explore more cases for deeper insights into hemostasis with Hemostasis Today.
-
Oct 22, 2026, 16:13William Wallace: The Hidden Neurological Impact of Vitamin B12 Deficiency
-
Oct 22, 2026, 16:06Akram Farhadi: Anemia and Low Hemoglobin Associated With Higher Risk of Osteosarcopenia in Older Adults
-
Oct 22, 2026, 15:49Javed Iqbal: NUMC Pulmonary and Critical Care Team Showcases Research at CHEST 2026
-
Oct 22, 2026, 15:37Alina Mitina: Key Concerns Surrounding DVT and Pulmonary Embolism
-
Oct 22, 2026, 14:45Seyed Mehrab Safdari: Prenatal Diagnosis in Hemophilia – Two Decades of Progress and Remaining Challenges
-
Oct 22, 2026, 14:39Mahmoud Abdelnabi: Evaluating the Evidence on Elevated Lp(a) and VTE Before Clinical Translation
-
Oct 22, 2026, 14:34David McIntosh: Fundamental Flaws in National Blood Systems Are Root Causes of Failure
-
Oct 22, 2026, 14:32Aurelio Maggio: Bridging Scientific Progress and Equitable Access to SCD Care in Sub-Saharan Africa
-
Oct 22, 2026, 14:26Khaled Musallam: Longevity and Healthy Aging in Thalassemia