


David McIntosh: Outdated Plasma Collection Methods and the Global Shortage of Plasma-Derived Medicines
David McIntosh, Founder and Chair of United Plasma Action, shared Mokhtar Tazik’s post on LinkedIn:
“Doctor Tazik has once again put his finger on a point of enormous importance for all who care about the millions of less fortunate patients in our deeply unequal World.
It is estimated that, globally, approximately 250 million people struggle against Rare Diseases, without the benefit of the Plasma-Derived Medicines that could help them.
The consequent suffering and premature mortality is a shameful blot on the conscience of Humankind.
Mokhtar is soooo right that the basic principles of Science demand rigorous attention to the evidence – a healthy skepticism and constant vigilance against out-dated beliefs and policies, a readiness – indeed an eagerness – to change course when the evidence points in new directions.
Unfortunately – fatally unfortunately – this is not happening in the field of Plasma-Derived Medicines.
The vital raw material – donated Human Plasma – is in desperately short supply globally.
The Plasma-Derived Medicines supply is consequently pathetically inadequate. It meets less than one quarter of the estimated global patient need.
And – meanwhile – almost all the establishments with any influence in this field still insist on promoting outdated ineffective methods of Plasma collection – based on what they are pleased to call ‘Altruistic Donation’.
This stubborn insistence on never giving donors any significant financial compensation for their efforts is not based on Science. It’s not based on evidence at all. It is merely a pseudo-ethical conviction. It’s rooted in ancient and worthy traditions, but utterly devoid of any scientific basis whatsoever.
On the contrary, it flies in the face of decades of evidence. It is also patently unsupported by any genuine principles of Ethics.
The few countries who do in fact collect enough Plasma, and do in fact meet their own clinical needs, are those who ignore the ‘Altruism’ exhortations and actually deploy effective systems of appropriate donor compensation.
The one country in the World (yes, just one ….) that actually makes any plasma contribution to the needs of others beyond its own borders is the USA – where, of course plasma donors are recognised with reasonable financial compensation and have been for decades.
If we respect and admire altruism, then it would surely seem appropriate to consider which countries in our deeply unequal World are the most righteous – those who provide vital medical supplies for others, or those who praise ‘Altruism’ but fail to meet even their own patients’ needs without importing plasma from the USA.
In the vast majority of countries, importation is so expensive as to be unaffordable.
In the vast majority of countries, Rare Disease patients simply suffer and die untreated.
Doctor Tazik must surely be right that an in-depth reconsideration of this global disaster is long overdue……
More power to your elbow, sir!”
Mokhtar Tazik, Plasma Bussiness Manager and Local Biotest QA at DAC, shared a post on LinkedIn:
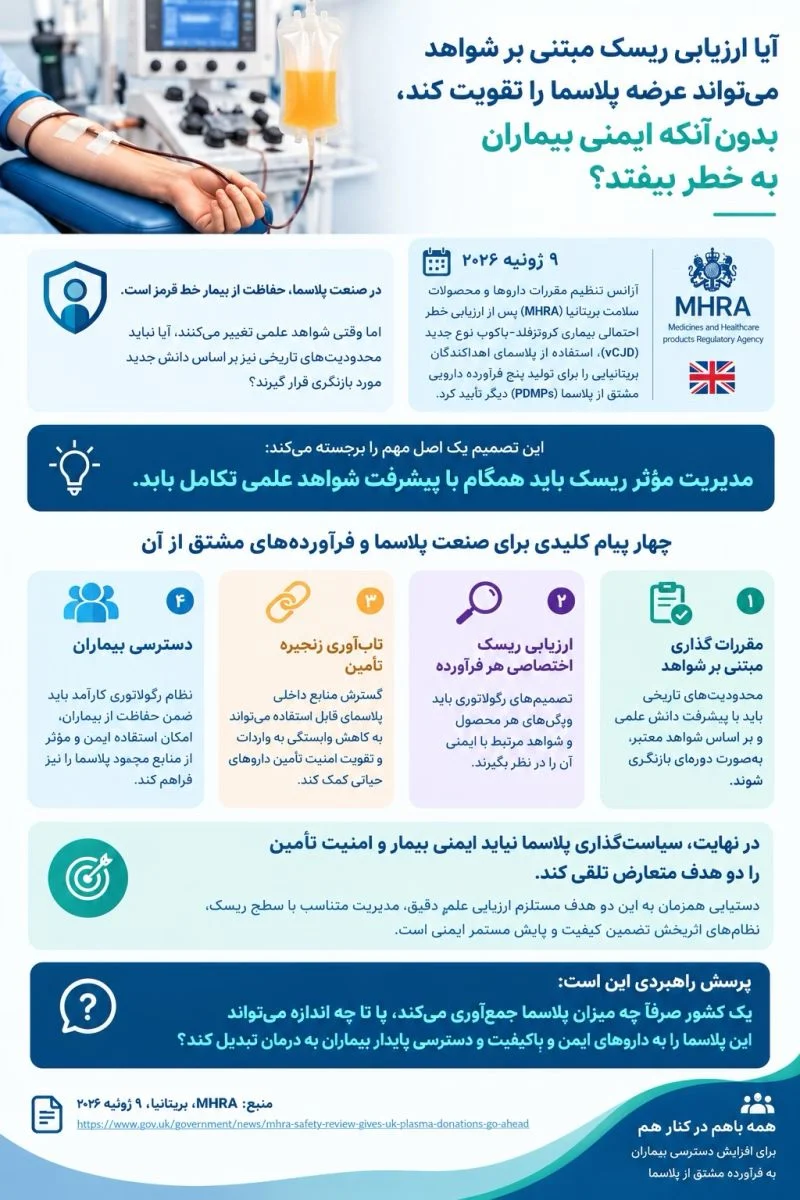
“Can Evidence-Based Risk Assessment Strengthen Plasma Supply Without Compromising Patient Safety?
In the plasma industry, protecting patients is non-negotiable. But how should regulators respond when scientific evidence evolves and historical restrictions can be reassessed?
In July 2026, the UK Medicines and Healthcare products Regulatory Agency (MHRA) announced approval for the use of UK-donor plasma to manufacture five additional PDMPs following a review of the potential risk of variant Creutzfeldt–Jakob disease (vCJD).
This decision highlights an important principle: ‘Effective risk management should implement with scientific evidence’
A similar evidence-based approach is reflected in transfusion medicine.
In Germany, a 2023 regulatory decision allowed the removal of 4-months quarantine requirements for certain plasma components for transfusion, subject to strict initial screening criteria, including NAT.
More recently, a clinical trial published in JAMA in August 2026 evaluated cold-stored platelets kept at 1–6°C for up to 21 days for bleeding control in cardiac surgery. This research further illustrates how established practices can be reassessed using clinical evidence, while carefully evaluating patient safety outcomes.
For the plasma and PDMP sector, several lessons stand out:
- Evidence-based regulation: Historical restrictions should be periodically reassessed as scientific knowledge advances.
- Product-specific risk assessment: Regulatory decisions should consider the characteristics of individual products, their intended use, and the evidence relevant to their safety.
- Supply chain resilience: Expanding the range of safely usable plasma sources and optimizing the management of blood components may help reduce avoidable wastage, strengthen supply security, and improve resource utilization.
- Patient access: A robust regulatory framework should protect patients while enabling the safe and effective use of available plasma resources.
Ultimately, plasma policy should not be outlined as a choice between safety and supply. The objective is to achieve both through strong scientific assessment, proportionate risk management, effective quality systems, and continuous safety monitoring.
Scientific progress should inform regulatory progress ,strengthening supply chain resilience while safe patient access to essential PDMPs.
Now the question would be how evidence-based regulatory reassessment play in strengthening national and regional access to PDMPs?”
More posts featuring David McIntosh on Hemostasis Today.
-
Oct 26, 2026, 20:00José Antonio García Erce: Recognizing Professor Marcela Contreras’ Contributions to Spanish Hematology
-
Oct 26, 2026, 19:47Ahmed Boukaraa: Transfusion Safety – Have You Checked Calcium Levels before Transfusing?
-
Oct 26, 2026, 19:43Mohd J. Maaita: The Classic Golf Ball Appearance in Hemoglobin H Disease
-
Oct 26, 2026, 19:40Nikola Pantic: Presenting National Guidelines for CAT at the 7th Congress of Hematologists of Serbia
-
Oct 26, 2026, 19:40Gurleen Kaur: Anticoagulation in tMCS
-
Oct 26, 2026, 19:35Isaac Okello: Advancing Sickle Cell Research in Uganda
-
Oct 26, 2026, 19:35Aoife Kelly: Delighted to Present My Poster at the Irish Society for Immunology Annual Meeting
-
Oct 26, 2026, 16:40Elena Torre: Rethinking Iron Management in Polycythemia Vera
-
Oct 26, 2026, 16:31Tara King: Building Connections in Transfusion Medicine at AABB