


Chokri Ben Lamine: Matching Anemia Treatment to the Myelofibrosis Patient
Chokri Ben Lamine, Hematologist at King Faisal Specialist Hospital and Research Center, shared a post on X:
“Managing anemia in myelofibrosis: match treatment to anemia, spleen burden and symptoms!
1. Start by identifying the cause before attributing anemia entirely to MF, assess:
- Bleeding or hemolysis
- Iron, vitamin B12 or folate deficiency
- Renal dysfunction
- Treatment-related marrow suppression
- Disease progression
RBC transfusions provide supportive care when clinically indicated.
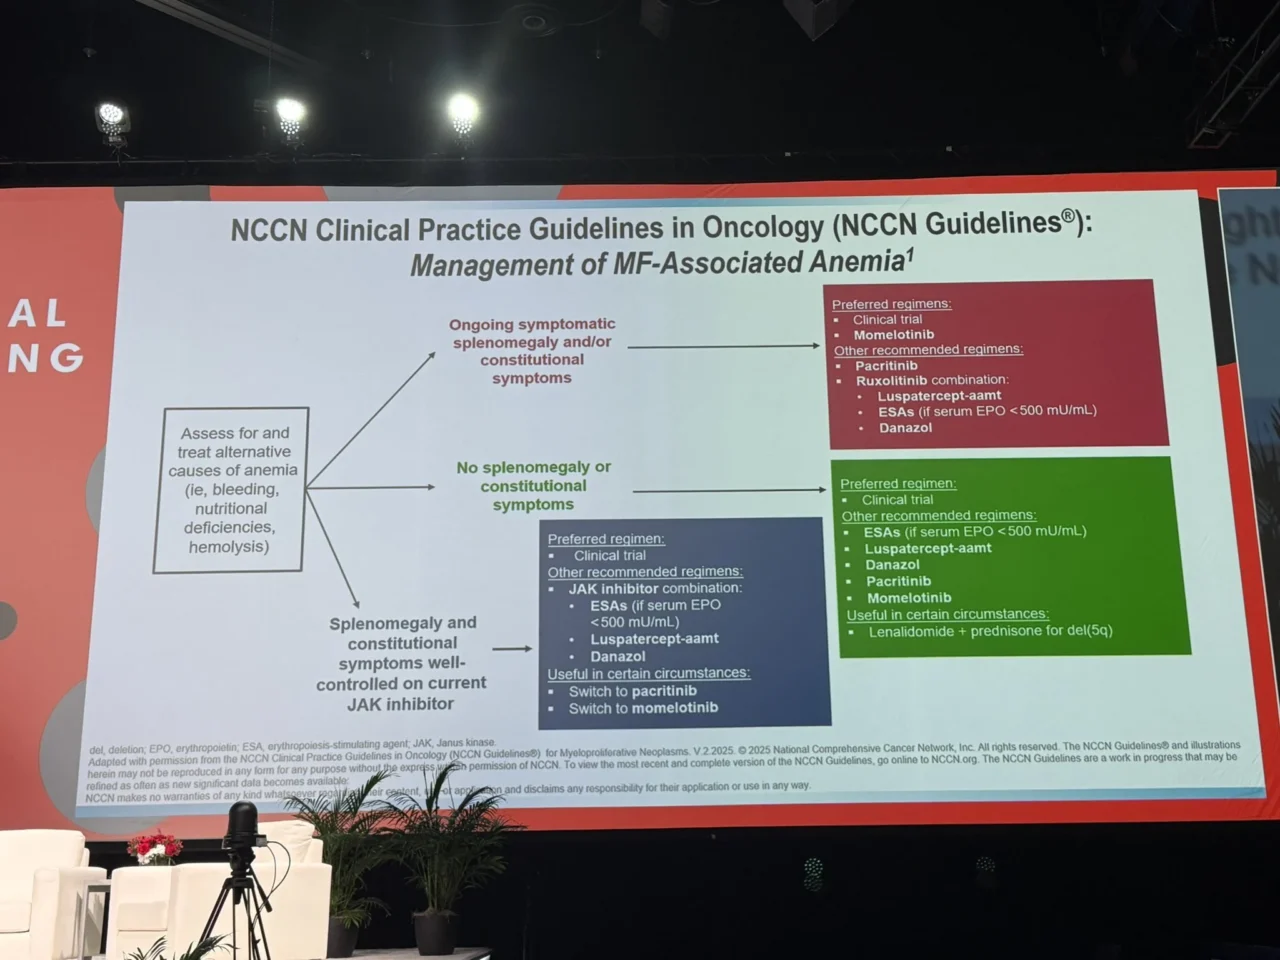
2.The treatment framework shown.
The slide cites NCCN v2.2025, so its categories should be read in that context:
- Anemia and ongoing symptomatic splenomegaly/constitutional symptoms: momelotinib or a clinical trial; other listed approaches include pacritinib or ruxolitinib with anemia-directed therapy.
- Spleen/symptoms controlled on the current JAK inhibitor: consider adding an ESA, danazol or luspatercept, or switching JAK inhibitor when appropriate.
- Anemia without symptomatic spleen disease: prioritize anemia-directed treatment and clinical trials.
The slide uses serum EPO less than 500 mU/mL to identify patients for ESA consideration. Guideline inclusion and regulatory approval are separate considerations.
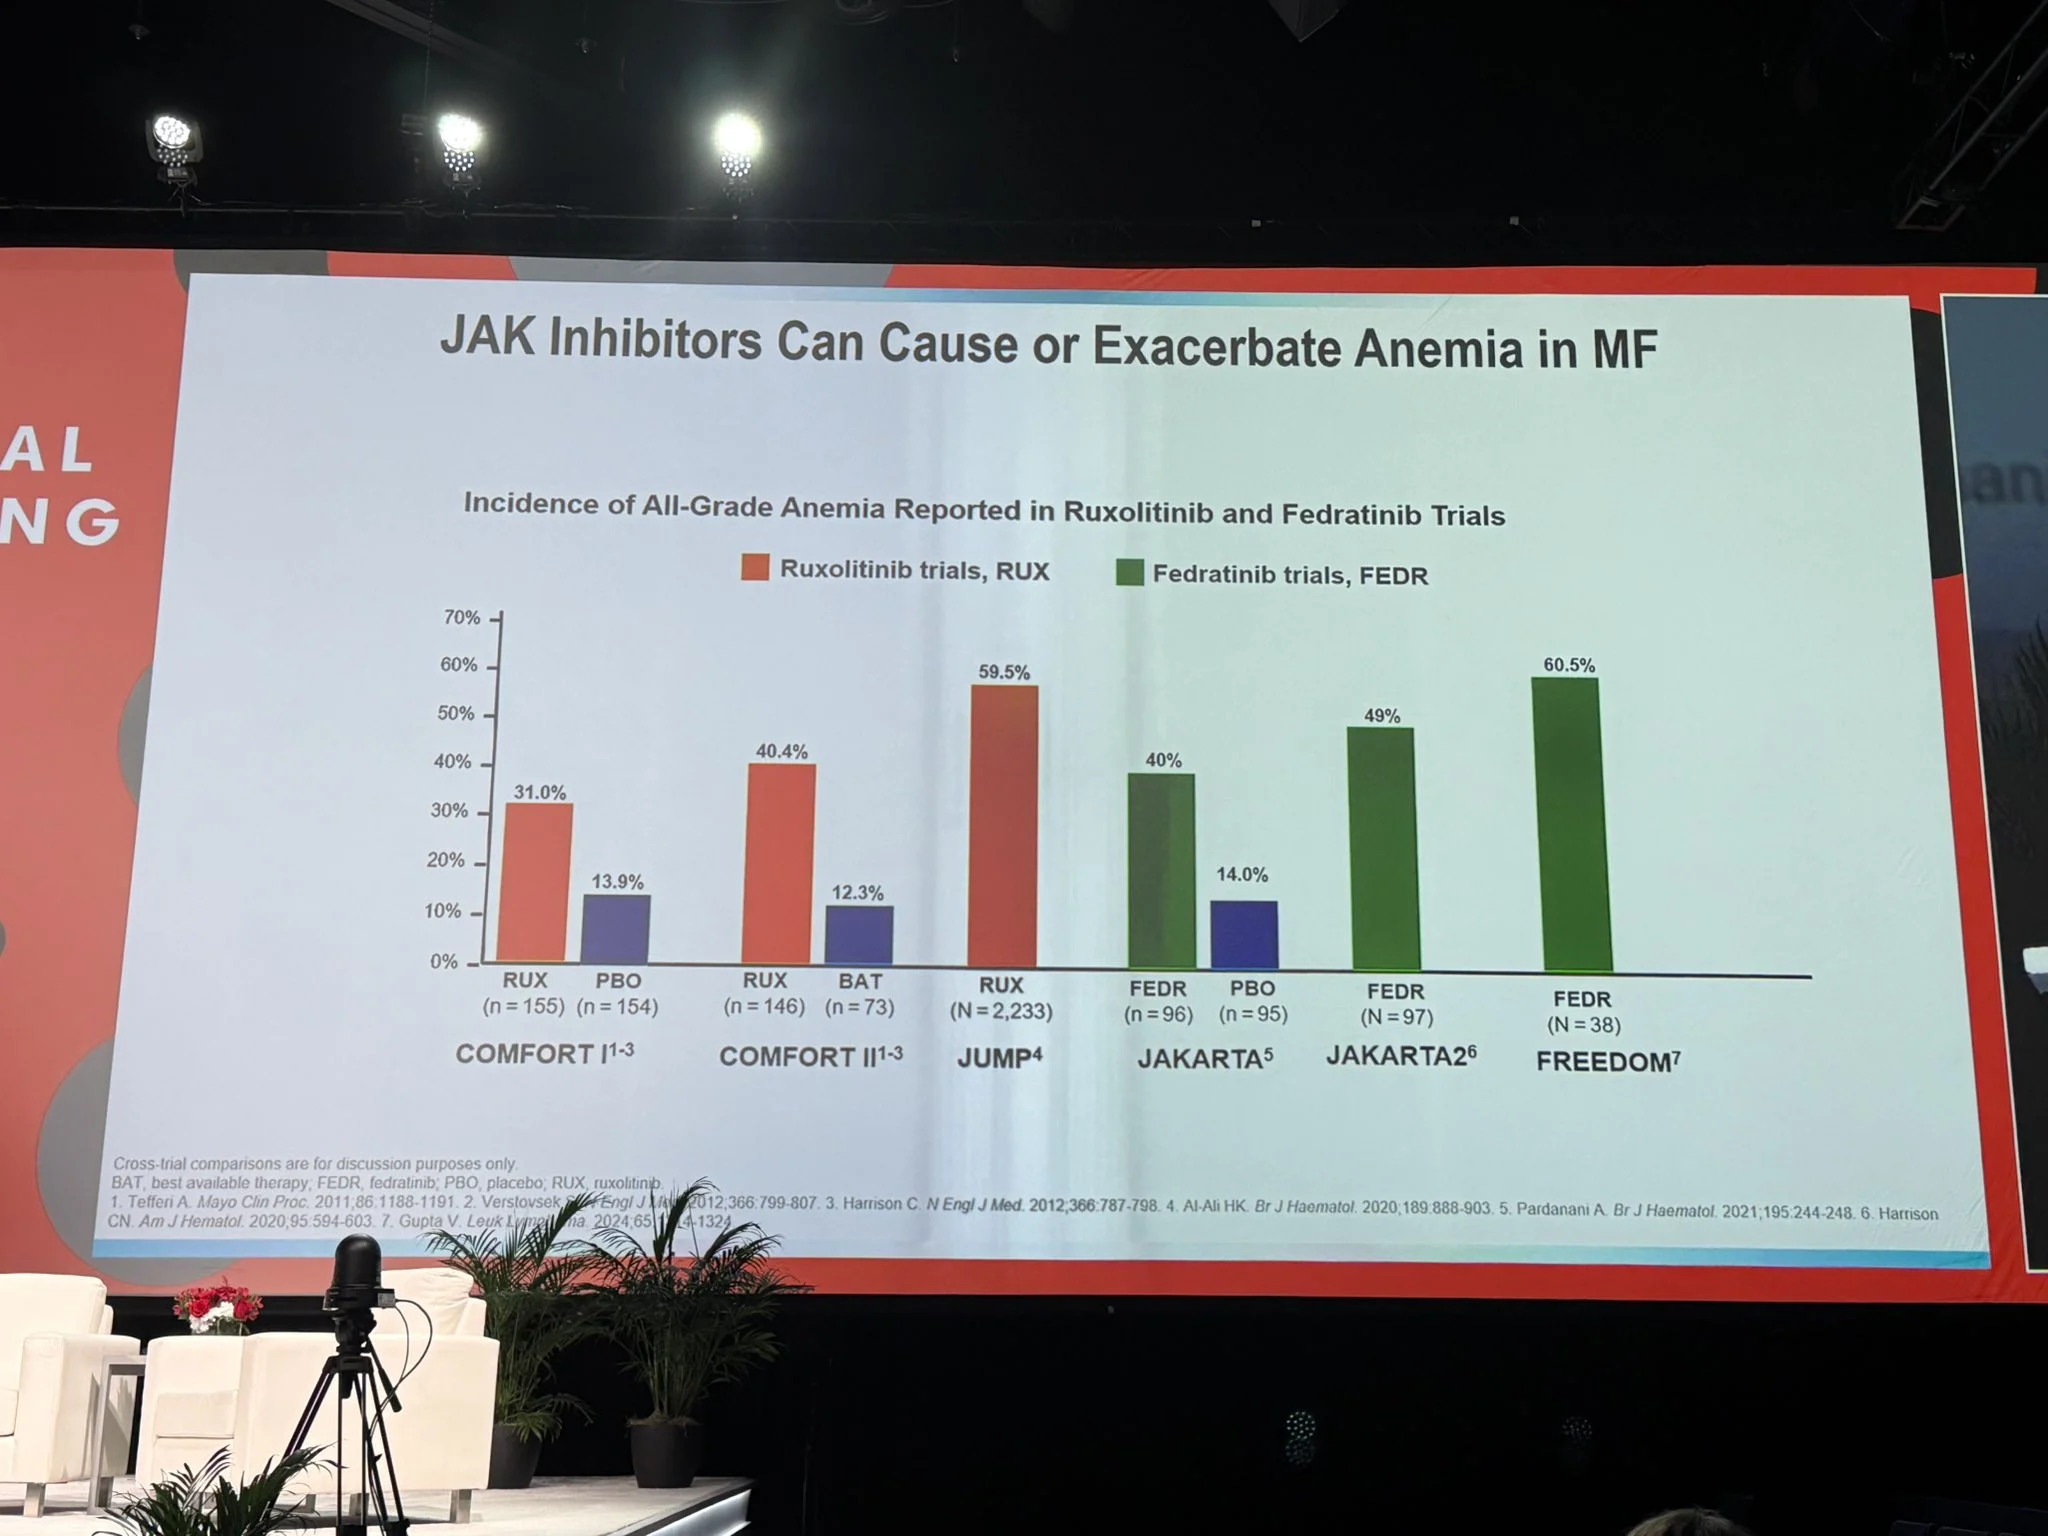
3.JAK inhibitors differ in their effects on anemia.
The slide reports all-grade anemia across selected trials:
- Ruxolitinib: approximately 31–60%
- Fedratinib: approximately 40–61%
These figures come from different populations and reporting methods—they cannot establish which drug causes more anemia.
A falling Hb during treatment requires assessment of timing, severity, transfusion burden and concurrent disease control.
4.Why momelotinib can help anemia
- Momelotinib inhibits JAK1/JAK2 and ACVR1/ALK2.
JAK inhibition addresses inflammatory signaling, spleen enlargement and symptoms.
ACVR1 inhibition lowers hepcidin – increases iron availability – supports erythropoiesis.
Connection to the preceding PV slides:
- Rusfertide mimics hepcidin to restrict erythropoiesis; momelotinib suppresses hepcidin to improve iron availability in MF.
Usual adult dose: 200 mg orally once daily. Its US indication covers intermediate/high-risk MF in adults with anemia.
Prescribing information
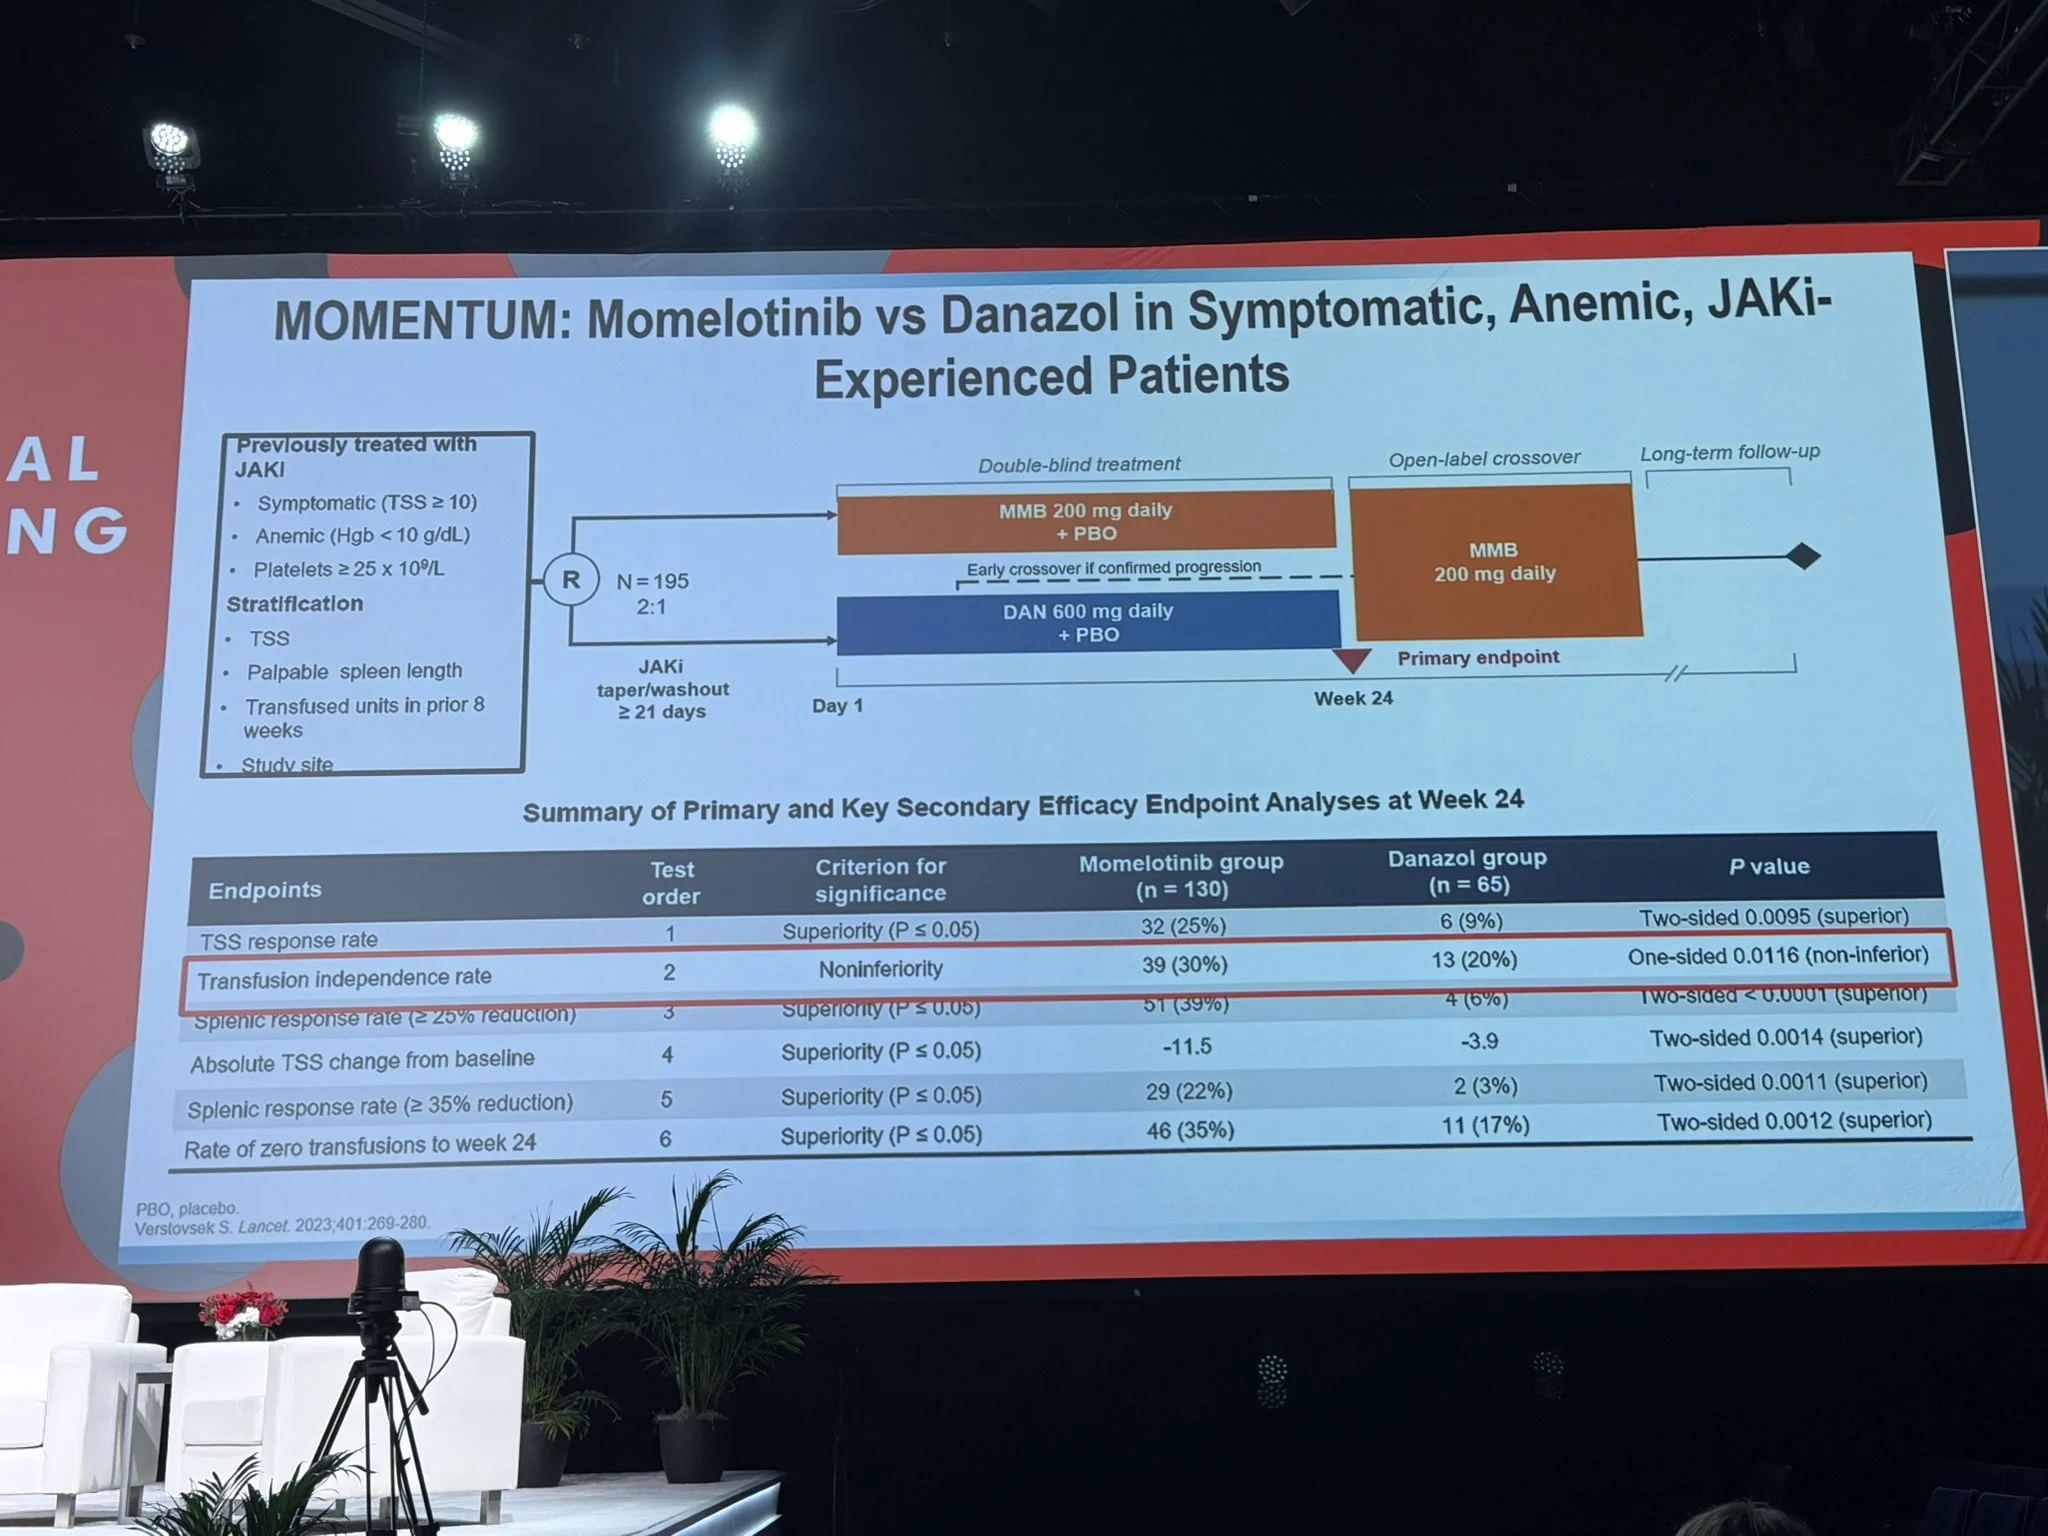
5.MOMENTUM : who was studied?
- Randomized, double-blind phase III trial; N equals 195, randomized 2:1.
Patients had:
- Prior JAK-inhibitor exposure
- Symptoms: total symptom score greater than or equal to 10
- Anemia: Hb less than 10 g/dL
- Platelets greater than or equal to 25 ×10⁹/L
Treatment:
- Momelotinib 200 mg/day versus danazol 600 mg/day
- Primary assessment: week 24.
MOMENTUM publication
6.MOMENTUM results at week 24
Momelotinib versus danazol:
- Greater than or equal to 50% symptom-score reduction: 25% vs 9%
Primary endpoint; superiority demonstrated.
- Transfusion independence: 30% vs 20%
The prespecified test demonstrated noninferiority, not superiority.
- Greater than or equal to 35% spleen-volume reduction: 22% vs 3%
Superiority demonstrated.
- No transfusions through week 24: 35% vs 17%
Superiority demonstrated.
Transfusion independence required no transfusions and no Hb less than 8 g/dL during weeks 12–24. It is different from receiving zero transfusions throughout the entire study period.
Trial results
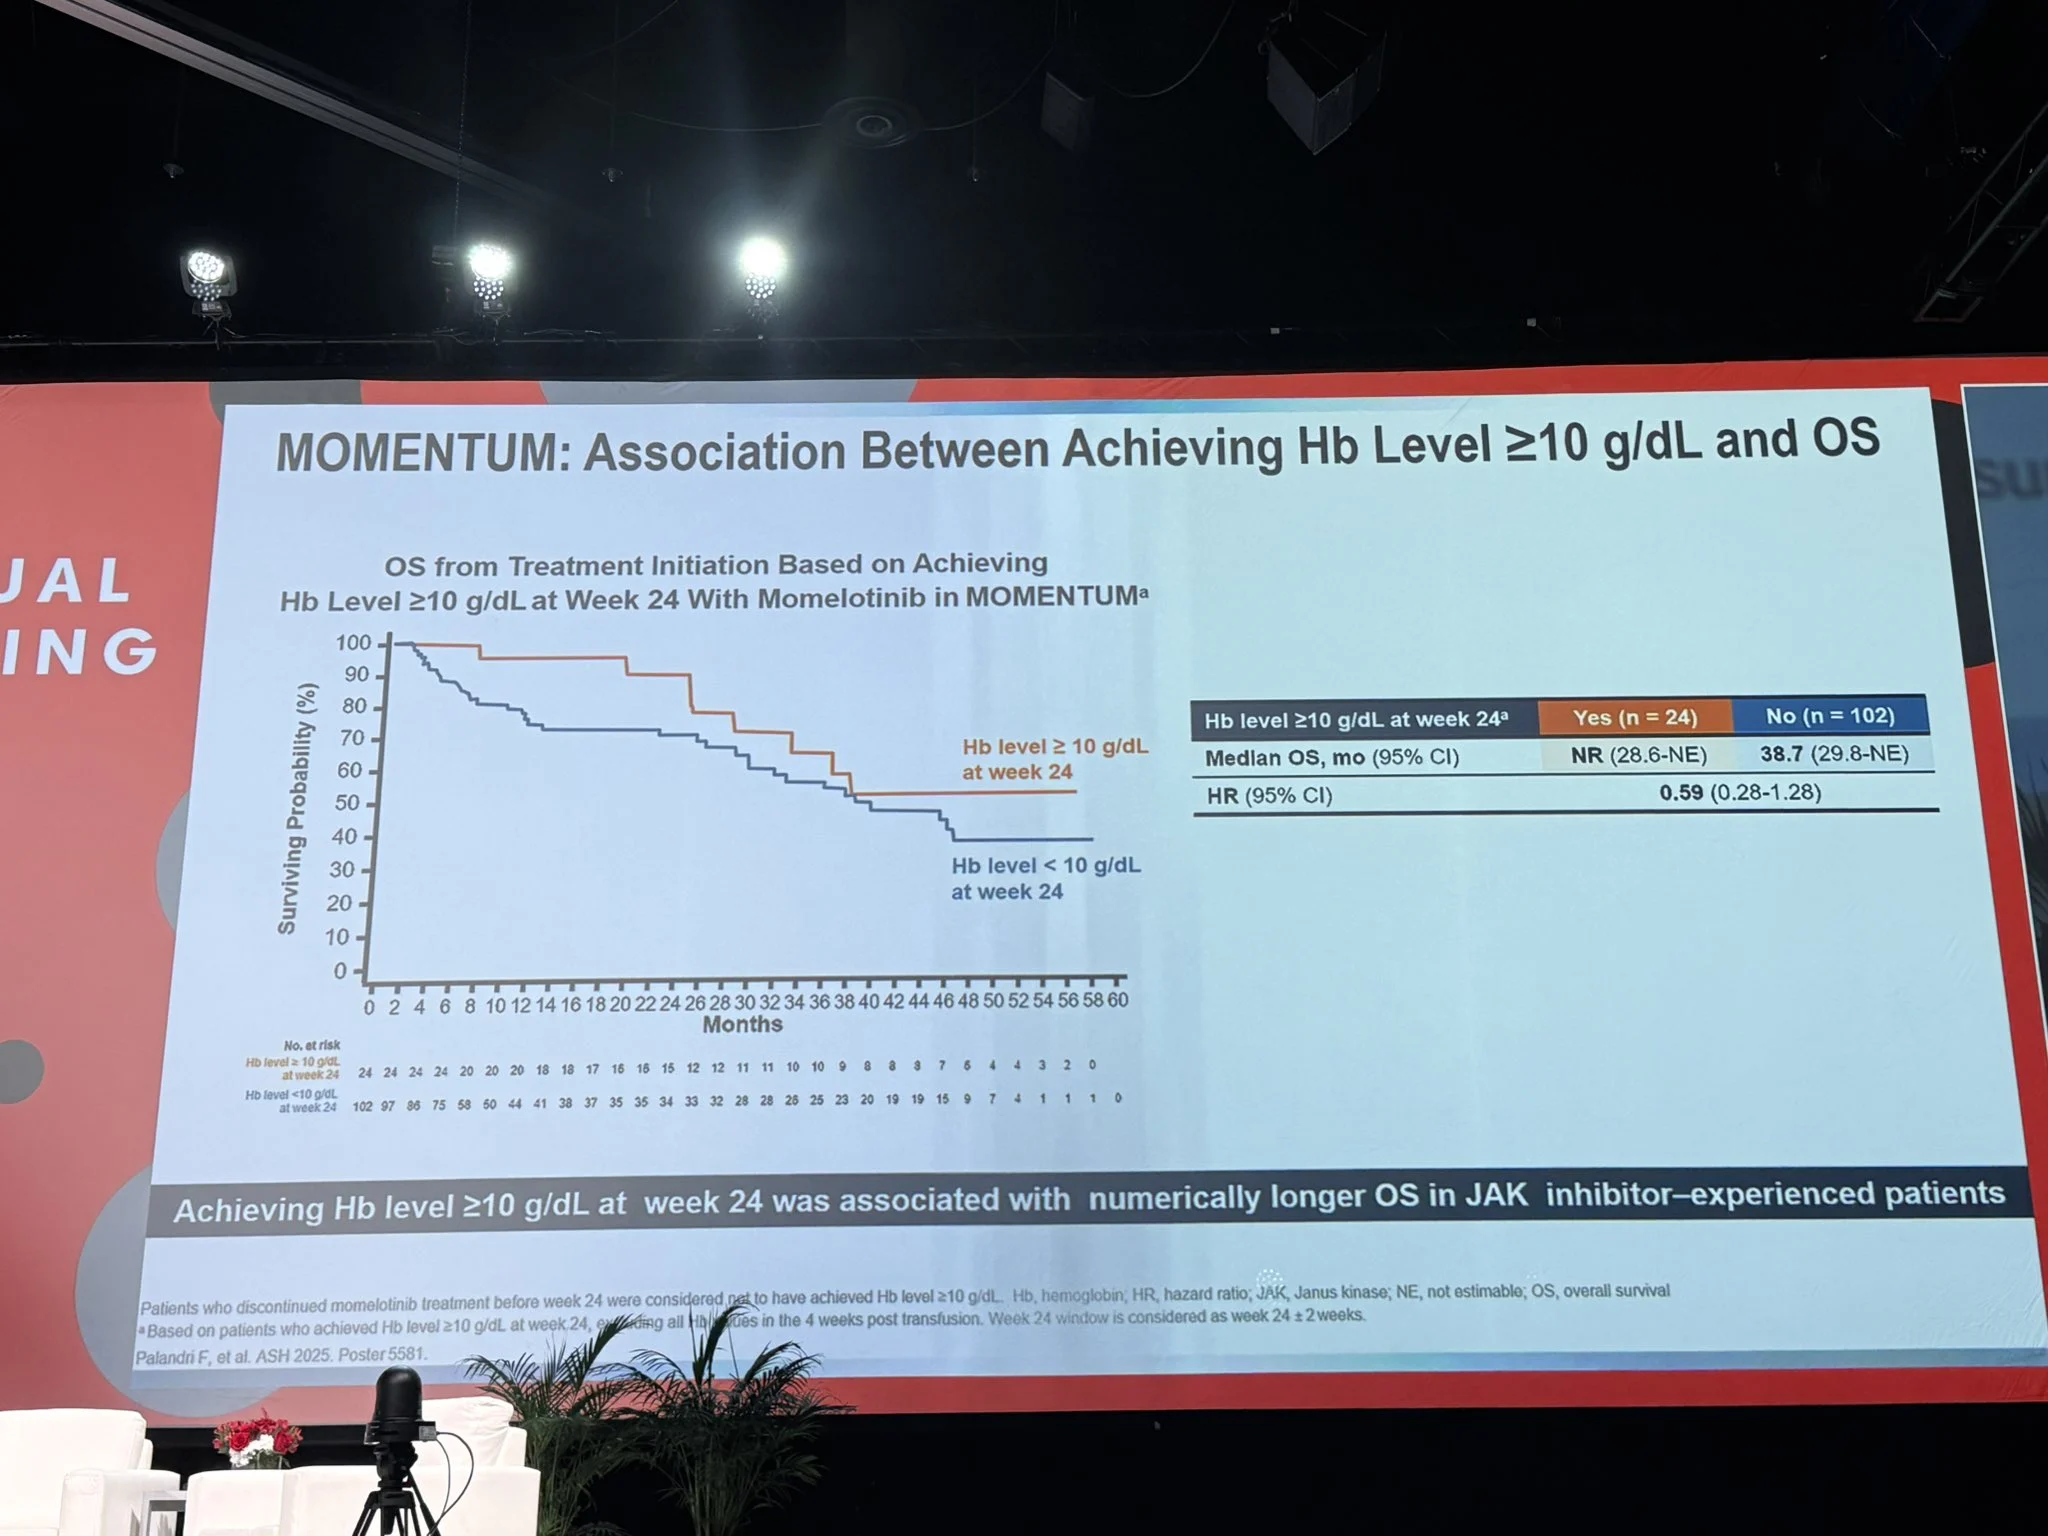
7.Does achieving Hb Greater than or equal to 10 g/dL improve survival?
The exploratory analysis displayed reports:
- Hb greater than or equal to 10 at week 24: n equals 24
- Hb less than 10/nonachievement: n equals 102
- OS hazard ratio: 0.59; 95% CI 0.28–1.28
The confidence interval crosses 1: the survival difference was not statistically significant.
Patients were grouped by a response occurring after treatment began; early discontinuations counted as nonachievement. This creates potential selection and guarantee-time bias.
Appropriate conclusion: Hb improvement was associated with numerically longer survival; this analysis does not prove that correcting Hb prolongs life.”
Other posts featuring Chokri Ben Lamine on Hemostasis Today.
-
Nov 16, 2026, 13:49Bahman Rasouli: A Rare Vascular Manifestation of Recurrent Papillary Thyroid Carcinoma
-
Nov 16, 2026, 13:28Muhammad Danyal: Platelet Patterns in Hepatitis B and C
-
Nov 16, 2026, 12:52Frank Nocken: Alzheimer’s Research Expands Beyond Amyloid-Based Treatments
-
Nov 16, 2026, 12:44Stefan Prendić: How Intronic Variants Affect Rh Blood Group Antigen Expression
-
Nov 16, 2026, 12:26Samwel Mikaye: Understanding Warfarin and Its Clinical Management
-
Nov 16, 2026, 12:14Sophia Delicou: Ensuring Lifelong Health Beyond Stem Cell Transplantation
-
Nov 16, 2026, 12:06Edward Lee Carter: Has PEPPER Changed the Role of Aspirin in Arthroplasty VTE Prophylaxis?
-
Nov 16, 2026, 11:53Eduardo Ortiz Bello: The Endothelium in Hemostasis and Microcirculation
-
Nov 16, 2026, 11:51Phil Spinella: Advancing Transfusion Medicine Through Collaboration