


Mona Alfaraj: Distinguishing HCL from SMZL in Bone Marrow
Mona Alfaraj, Consultant Hematopathologist and Transfusionist, shared a post on LinkedIn:
“While spleen histopathology remains the definitive gold standard for diagnosing Splenic Mariginal Zone lymphoma (SMZL), diagnosing SMZL from the bone marrow is primarily done sometimes to avoid a splenectomy or when splenic tissue is not accessible surgically or when accessible lymph nodes are not available to sample as SMZL characteristically presents without peripheral lymphadenopathy.
But What are the key pathological similarities between HCL and SMZL that necessitate a careful distinguishing approach?
Hairy Cell Leukemia (HCL) and Splenic Marginal Zone Lymphoma (SMZL) share several overlapping features as both are mature, indolent B-cell lymphoproliferative disorders that primarily affect older adults, present with prominent splenomegaly, bone marrow infiltration, while generally sparing the peripheral lymph nodes.
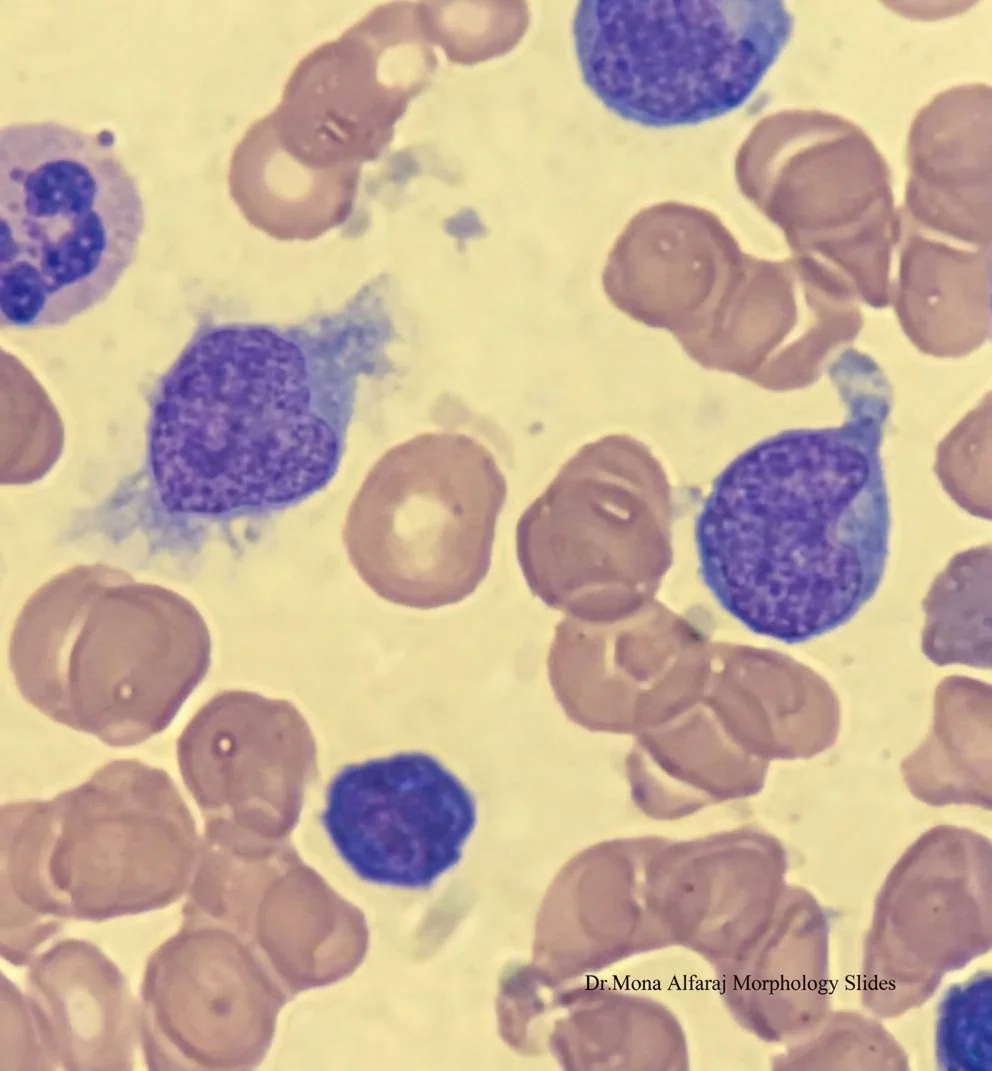
Both manifest with circulating abnormal B-lymphocytes that display cytoplasmic projections or ‘villous/hairy’ borders on a peripheral blood smear.
Both express mature pan-B-cell surface markers, including CD19, CD20, and CD22, and show monoclonal light chain restriction and both are negative for CD5 and CD10 (only less than 10 percent and less than 5 percent of HCL are positive for CD5 or CD10, respectively).
Accurately differentiating HCL from SMZL is clinically critical because their prognoses, therapeutic pathways, and monitoring strategies are entirely different.
Here is a summary of point by-point comparison that I had presented in the 10th hematopathology overview and 7th Saudi lymphoma/myeloma conference to distinguish Hairy Cell Leukemia (HCL) from Splenic Marginal Zone Lymphoma (SMZL) in the bone marrow:
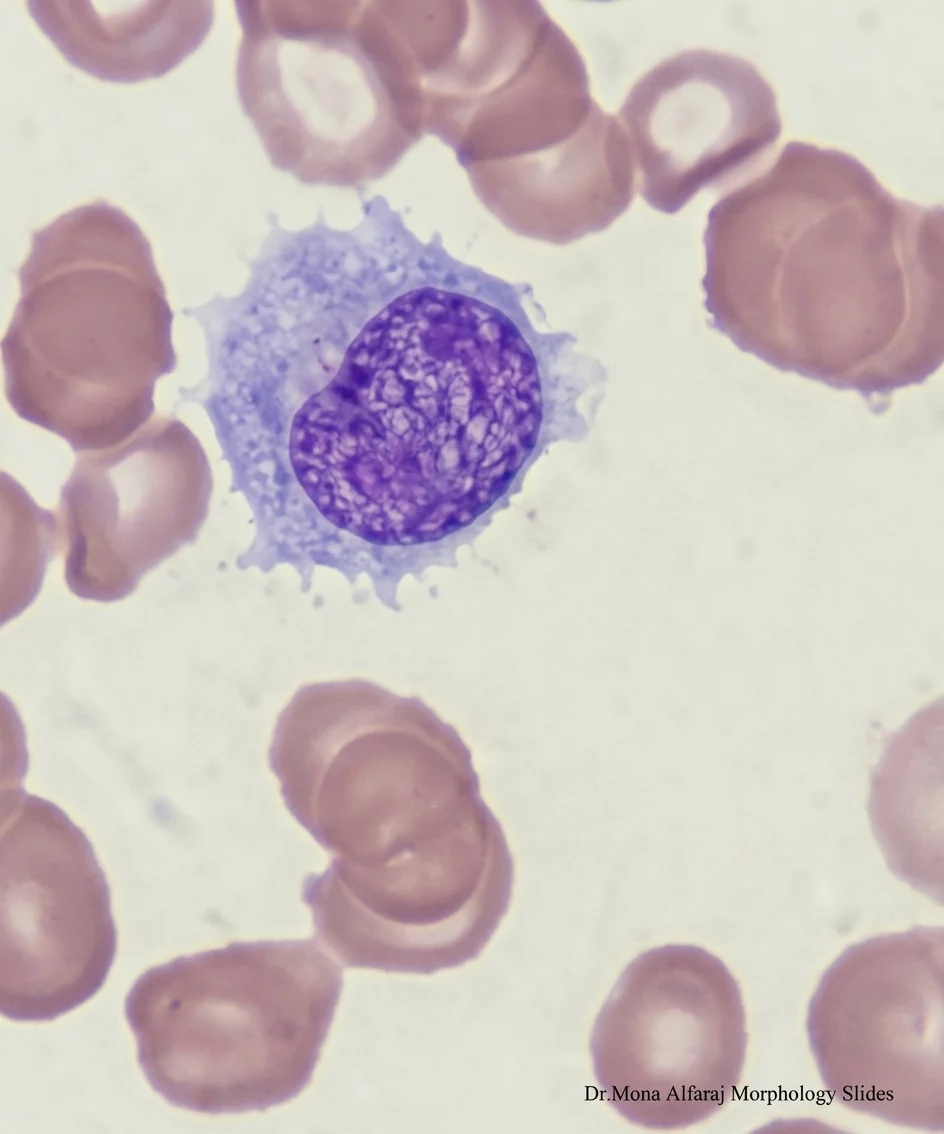
- HCL Cells have abundant pale blue/clear cytoplasm with oval or kidney shaped nucleus and short ,circumferential, hair-like cytoplasmic projections, while SMZL Cells have scant-to-moderate, narrow cytoplasm that lacks the clear, expansive halo seen in HCL with short, unevenly distributed villous projections that are characteristically polarized (clustered at one or both poles of the cell, leaving the rest of the border smooth).
- Nuclei of SMZL cells are usually round and centrally located with more condensed chromatin.
- HCL frequently results in a ‘dry tap’ during bone marrow aspirate procedures due to increased reticulin fibrosis surrounding individual cells while SMZL aspirates are usually successful because of minimal to no increased fibrosis.
- HCL Pattern: Cells infiltrate the marrow in a loose, interstitial or diffuse fashion and display a classic ‘fried-egg’ appearance as cells are widely spaced with abundant clear cytoplasm and distinct cell borders, while pattern of infiltration in SMZL characteristically nodular or intrasinusoidal.
Immunophenotype:
- HCL Markers: Strongly positive for Annexin A1, CD103, CD25, and CD11c.
- SMZL Markers: Typically negative for Annexin A1, CD103, CD25 and cyclin D1 (though CD11c can sometimes be weakly positive).
Genetic Mutation in HCL is almost universally driven by the BRAF V600E mutation while SMZL lacks this mutation and 20-30 percent may have 7q31-32 deletion.”
Stay updated with Hemostasis Today.
-
Oct 16, 2026, 09:44New International Consensus on Covert Brain Infarction – International Journal of Stroke
-
Oct 16, 2026, 06:17Neha Rastogi Panda: Precision Diagnosis and Organ Preservation in Splenic Abscess
-
Oct 16, 2026, 05:53Alejandro González Veliz: Looking Beyond Coronary Anatomy to Understand Ischemia
-
Oct 16, 2026, 04:16Asmaa M. Gouda: Advancing Blood Bank Leadership at Alexandria University Hospitals
-
Oct 16, 2026, 03:52Saja Al-Zamili: Minimally Invasive Hematoma Evacuation in Intracerebral Hemorrhage
-
Oct 16, 2026, 03:13Bhumika Satija: Beyond the Diploma A Growing Passion for Blood Banking and Transfusion Medicine
-
Oct 16, 2026, 03:03Jamie Nash: Microfluidics in Transfusion Medicine Advancing Blood Component Quality Assessment
-
Oct 16, 2026, 02:53World Thrombosis Day 2026 Advancing Women’s Health Through Better Thrombosis Research and Care – World Thrombosis Day
-
Oct 16, 2026, 02:42Areej Wasi: Myocardial Infarction in Young Adults Advancing Cardiology Education and Medical Leadership