


Arun V J: Blood Loss Isn’t Always an Emergency and Blood Isn’t Always the Answer
Arun V J, Consultant in the Department of Transfusion Medicine at Malabar Medical College, shared on LinkedIn:
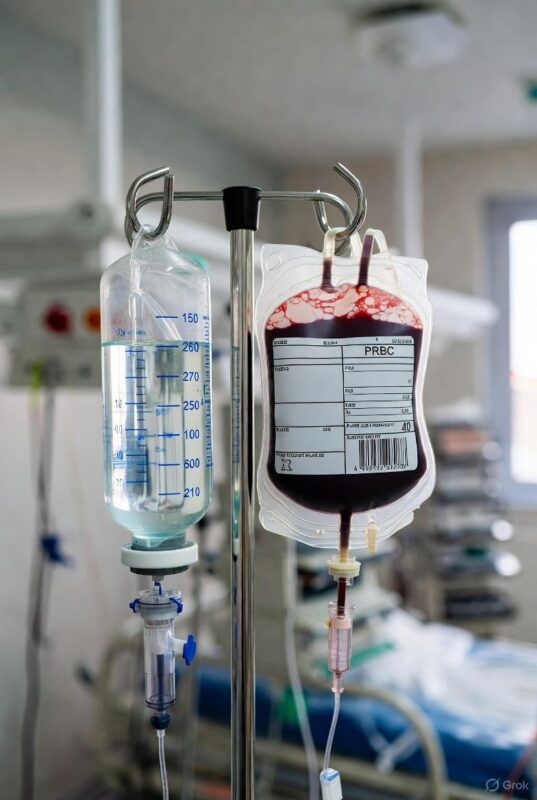
”Blood Loss Isn’t Always an Emergency… and Blood Isn’t Always the Answer
You don’t always need a blood transfusion.
And giving blood too early can sometimes do more harm than good.
As clinicians, families, and even patients, we often forget what actually matters:
Transfusions are not about fixing a number.
They’re about fixing oxygen delivery.
So what do we do before reaching for blood?
We bridge the patient safely. And we do it the right way.
Here are the basics we should all remember (and teach):
1. Blood Is for Oxygen and Clotting — Not for Every Drop Lost
Mild to moderate blood loss?
The body compensates beautifully.
We assess the whole patient, not just Hb on paper.
Symptoms, perfusion, lactate, mental clarity — these tell the real story.
2. Crystalloids: Great in a Crisis, Terrible as a Long-Term Plan
Normal saline and Ringer lactate can stabilise pressure quickly.
But they:
• clear fast
• dilute clotting factors
• carry zero oxygen
• can worsen outcomes when overused
They’re a bridge, not a solution.
3. Colloids: Stay Longer, Still Not Blood
Albumin, gelatins, starches…
They stay in the bloodstream longer but still don’t carry oxygen or help with clotting.
Same rule:
Use wisely. Don’t drown the patient.
4. Alternatives to Blood Exist — but They Can’t Replace Blood
Iron, erythropoietin, tranexamic acid, vitamin K, oxygen therapy, cell salvage…
All useful.
All meaningful.
But none can perform the full job of blood during significant bleeding.
They reduce unnecessary transfusions and help recovery — but they’re not substitutes.
Crystalloids vs Colloids vs Blood — What’s the Real Difference?
Crystalloids = quick boost
Colloids = longer boost
Blood = actual treatment
That simple distinction saves lives.
5. The Real Decision Point:
Is the Body Getting Enough Oxygen?
A patient with Hb 7 may be stable.
A patient with Hb 9 may be crashing.
Numbers lie. Physiology doesn’t.
Look at:
• mental status
• perfusion
• lactate
• work of breathing
• urine output
This is how you know when blood becomes life-saving.
6. Artificial Blood? Promising… but Not Here Yet
Trials are ongoing.
The science is exciting.
But we’re not replacing human blood any time soon.
The Message We All Need to Hear
Crystalloids and colloids buy time.
Alternatives support recovery.
But blood saves lives when oxygen delivery fails.
Knowing when to use each one is leadership.
Teaching it is responsibility.
Practicing it wisely is patient safety.
If you found this useful, hit Repost so more clinicians, students, and NGOs can understand this better.
And if you want deeper insights like this in simple language, here’s where I write more.
Let’s make good knowledge travel.”
Stay updated with Hemostasis Today.
-
Sep 20, 2026, 12:11Giacomo Buso: Silent Atherosclerosis Begins Earlier Than Expected
-
Sep 20, 2026, 12:0310 Posts Not to Miss This Week
-
Sep 20, 2026, 11:27Edward Lee Carter: Prasugrel Dosing Matters in P2Y12 Inhibitor Comparisons After PCI
-
Sep 20, 2026, 09:51Ceasovschih Alexandr: A Closer Look at Lipid Disorders in CKM Syndrome
-
Sep 20, 2026, 09:05World Stroke Academy: Can Adjunct IAT Improve Tissue Reperfusion?
-
Sep 20, 2026, 06:46Neeraj Songara: From Donated Blood to Engineered Therapeutics
-
Sep 20, 2026, 06:24Louise St. Germain Bannon: Improving Awareness and Care for Women Across the Lifespan
-
Sep 20, 2026, 05:17Maxime Dely: When ABO Compatibility Isn’t Enough for Safe Transfusion
-
Sep 20, 2026, 04:54William Aird: What Does a Complete History and Physical Really Mean?