


Nikhil Agrawal Breaks Down Perioperative Anticoagulation
Nikhil Agrawal, Internal Medicine Specialist (MBBS) at Safdarjung Hospital, shared a thread on X:
”Perioperative Anticoagulation
This is one of the hardest decisions in medicine.
Stopping too early increases clots.
Stopping too late increases bleeding.
This thread simplifies everything.
Start with the fundamental question
Perioperative AC is about preventing two dangers
• Surgical bleeding
• Thrombosis when AC is stopped
Every patient needs BOTH risks assessed before making any move.
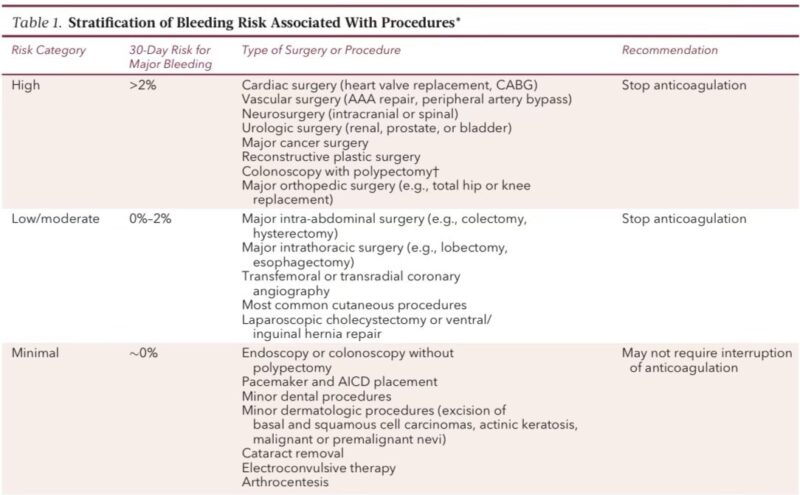
Step 1. Classify the procedure bleeding risk
Three levels guide the entire plan
• Minimal
• Low to moderate
• High
This determines whether AC is continued, temporarily held, or fully reversed.
Minimal bleeding risk (AC usually continued)
Examples
• Dental procedures
• Minor dermatology
• Pacemaker implantation
• Cataract surgery
• Arthrocentesis
• Diagnostic endoscopy
These have extremely low procedure-related bleeding even if AC is continued.
Low to moderate bleeding risk (AC usually interrupted)
Common examples
• Laparoscopic cholecystectomy
• Hernia repair
• Most abdominal and thoracic surgeries
• Coronary angiography
These procedures typically need short DOAC hold or warfarin interruption.
High bleeding risk procedures (strict AC control needed)
Examples
• Neurosurgery
• Major vascular surgeries
• Major cancer surgeries
• Total hip or knee replacement
• Surgeries with neuraxial anesthesia
These require near-complete anticoagulant clearance and controlled restart.
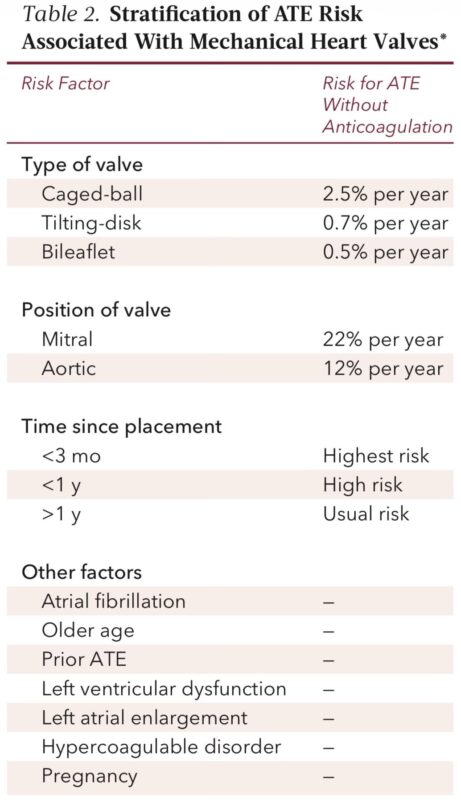
Step 2. Assess thrombosis risk
You must stratify thrombosis risk from
• Mechanical valves
• Atrial fibrillation
• VTE
This step decides whether interruption is safe and whether bridging is required.
Mechanical valve patients equals highest risk group
High-risk features
• Mitral mechanical valve
• Caged-ball or tilting-disk valves
• Valve placed <3 months
• Prior stroke
• AF or LV dysfunction
Mitral mechanical valves have up to 22 percent annual stroke risk without AC.
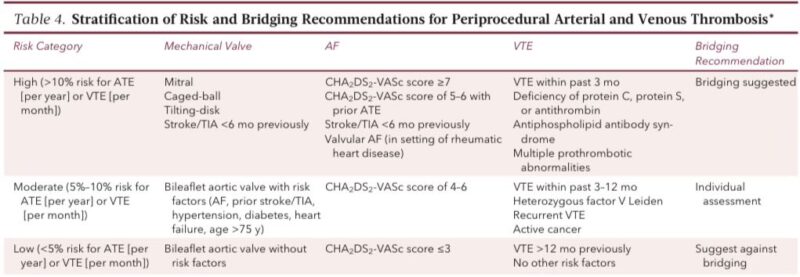
Atrial fibrillation thrombosis risk (CHA2DS2-VASc)
Risk levels
• 0 to 3 → low
• 4 to 6 → moderate
• ≥7 or recent stroke → high
BRIDGE trial: low and moderate AF patients bleed more if bridged without any reduction in stroke.
VTE thrombosis risk depends mainly on timing
• VTE <3 months → high risk
• VTE 3 to 12 months → moderate
• VTE >12 months → low
Strong thrombophilias (APS, protein C/S, AT deficiency) push the patient into high-risk category irrespective of timing.

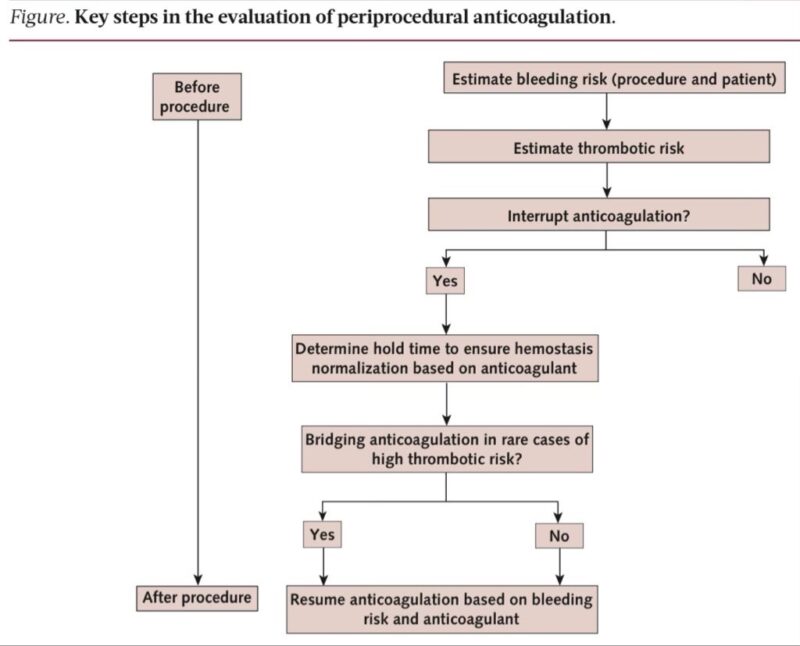
Step 3. Decide if AC must be interrupted
Simple rule
• Minimal bleeding risk → continue AC
• Low/moderate → interrupt safely
• High bleeding risk → interrupt and ensure INR normalization or full DOAC washout before incision
This step prevents intraoperative bleeding catastrophes.
Step 4. Bridging decisions (for warfarin only)
Bridging equals giving LMWH or UFH during warfarin interruption.
Modern evidence: bridging should be used only in very high thrombosis risk patients because it increases bleeding without reducing thrombosis in most others.
(PERIOP2 + BRIDGE trials)
Who truly needs bridging (rare but crucial)
Use bridging only when stopping AC is extremely unsafe:
• Mechanical mitral valve
• Caged-ball or tilting-disk valve
• CHA2DS2-VASc ≥7
• Recent stroke or TIA
• VTE <3 months
• APS or multiple thrombophilias
These are the ONLY groups where bridging has a favorable risk–benefit ratio.
Warfarin perioperative plan (clear and detailed)
Stopping
• Stop 5 days before surgery
• Check INR 7–10 days before, then again night before
• If INR >1.5 → give 1.25–2.5 mg vitamin K
Restarting
• Low/mod risk → restart 12 hours post-op
• High bleed risk → restart 24–36 hours post-op
Bridging ONLY if patient is very high thrombosis risk.

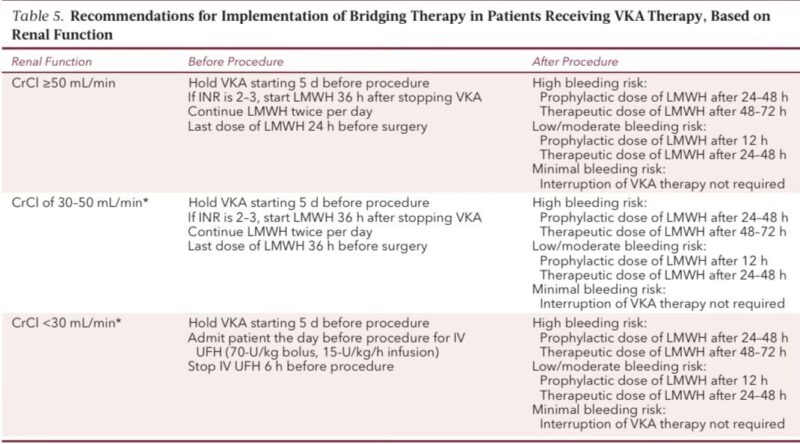
Bridging protocol (if indicated)
• Start LMWH 36 hours after last warfarin dose
• Last LMWH dose 24 hours before procedure
• If CrCl <30 → use UFH instead
• Stop UFH 6 hours before incision
Restart after surgery only when hemostasis is secure.
DOAC perioperative plan (simple, precise, evidence-backed)
Low/mod bleed risk
• Hold apixaban/rivaroxaban 1 day before
• Dabigatran: 1 day if CrCl ≥50, 2 days if <50
High bleed risk
• Hold apixaban/rivaroxaban 2 days
• Dabigatran: 2 days if CrCl ≥50, 4 days if <50
This is directly from the PAUSE protocol with very low bleeding/thrombotic rates.

Emergency surgery (need reversal)
If there’s no time for natural clearance:
Warfarin
• Vitamin K
• PCC preferred over FFP
DOACs
• Dabigatran → Idarucizumab
• Factor Xa inhibitors → Andexanet Alfa or PCC
Note: Andexanet may cause thrombosis and DOAC rebound.”
Stay updated with Hemostasis Today.
-
Nov 21, 2026, 20:00Jeyda Star: The FAST Signs of Stroke and the Reality of Life Afterward
-
Nov 21, 2026, 19:59Daniel Lindholm: Women Showed the Largest Improvement in Stroke Risk Over Time in Heart Failure
-
Nov 21, 2026, 19:56Neil Arrowsmith: Raising Awareness of Pulmonary Embolism in Young People
-
Nov 21, 2026, 19:52Muhammad Zeeshan Jamal: Thrilled to Present Our Research on Intermediate-Risk Acute PE in Abu Dhabi
-
Nov 21, 2026, 19:50Mounisha Devireddy: Proud to Share Our Research on High-Risk PE in Pregnancy
-
Nov 21, 2026, 19:47Melissa Hollo: How Severe Anemia Increases the Odds of Acute HF During Pregnancy and Postpartum
-
Nov 21, 2026, 19:44Ashenafi Tazebew Amare: Building Sustainable Systems to Close the Anti-D Immunoglobulin Access Gap in LMICs
-
Nov 21, 2026, 19:43Sheharyar Raza: Interpreting Clotting Times Through Reptilase Time and Thrombin Time Assays
-
Nov 21, 2026, 19:42Minoo Ahmadinejad: Serving on the ISTH 2027 Scientific Theme Committee for Women’s Health