


Tareq Abadl: CMV and Transfusion – Leukoreduction vs CMV-Seronegative
Tareq Abadl, Medical Laboratory Specialist and Director of the Blood Bank at Dr. Abdelkader Al-Mutawakkil Hospital, shared a post on LinkedIn:
“CMV and Transfusion — Leukoreduction vs CMV-Seronegative
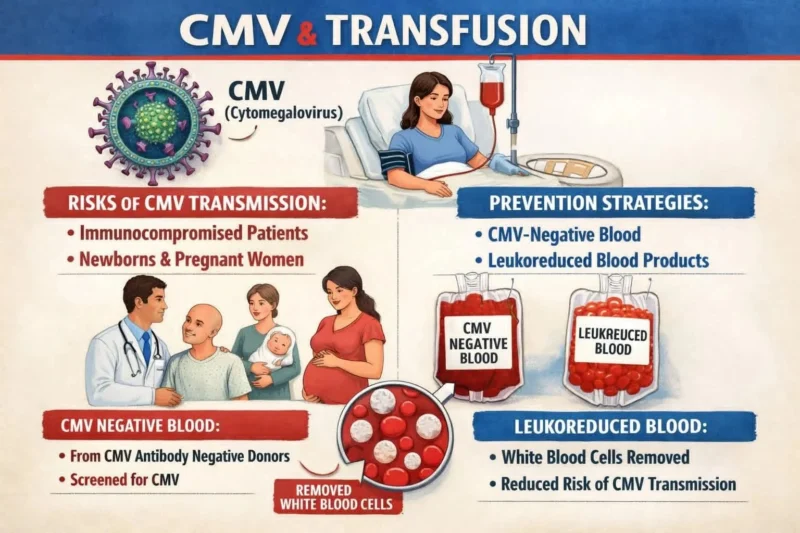
Cytomegalovirus (CMV) can be transmitted through blood components, but modern transfusion practice has reduced this risk dramatically.
For most at-risk patients, pre-storage leukoreduced (‘CMV-safe’) components are considered an effective alternative to routinely using CMV-seronegative units — with a few important exceptions.
What Major Authorities Say?
Organizations such as the AABB, the Centers for Disease Control and Prevention (CDC), and national blood services like Canadian Blood Services recognize that:
- Pre-storage leukoreduction significantly reduces transfusion-transmitted CMV (TT-CMV).
- Many programs consider leukoreduced (CMV-safe) and CMV-seronegative components clinically equivalent for most indications.
Important Exceptions
Maximal prevention is still recommended in certain high-risk settings:
- Intrauterine transfusion (IUT)
- Some extremely low-birthweight neonates
Selected transplant or severely immunocompromised patients (based on local policy)
- In these cases, request CMV-seronegative units in addition to leukoreduction.
- Always follow your institution’s policy and consult neonatology/transplant teams when needed.
Practical Blood Bank Guidance
Default practice:
Provide pre-storage leukoreduced components for routine transfusion.
For listed exceptions:
Request CMV-seronegative units plus leukoreduction.
Document the clinical indication clearly in the order.
System optimization:
Tag ‘CMV-safe’ components automatically in the LIS.
Add a required checkbox for ‘CMV-seronegative requested’ with documented reason.
Audit compliance and outcomes periodically.
Why Leukoreduction Works?
CMV resides mainly in white blood cells.
Leukoreduction removes the majority of this cellular reservoir, dramatically lowering TT-CMV risk.
That’s why many blood services shifted away from maintaining large universal seronegative inventories — it simplifies logistics while remaining protective for most patients.
Summary
- Leukoreduction: effective protection for most patients
- CMV-seronegative units: reserved for specific high-risk scenarios
- Always align practice with local policy and patient risk profile
Modern transfusion medicine balances safety, practicality, and evidence — not tradition.”
Find more posts featuring Tareq Abadl on Hemostasis Today.
-
Oct 7, 2026, 16:44Amor Salah: 2026 NCS/SCCM Guidelines for Managing Antithrombotic-Associated ICH
-
Oct 7, 2026, 16:04NETs in Thrombosis: From Mechanism to Therapeutic Target
-
Oct 7, 2026, 15:28Amir Samimi: Prognostic Value of Platelet Count in Resected HNSCC
-
Oct 7, 2026, 15:21Eloïse Laouenan: Bridging Immunity and Thrombosis in MVTE
-
Oct 7, 2026, 15:10Uthra Sundaram: Honouring Donors During International Plasma Awareness Week
-
Oct 7, 2026, 15:04Daniel Victor Ortigoza: Should Frail Older Patients With AF Switch From VKA to DOACs?
-
Oct 7, 2026, 14:53Susan Noone: Donor Turned Recipient Shares Lifesaving Transfusion Story
-
Oct 7, 2026, 14:49Aimee Burtenshaw: The Impact of the Infected Blood Inquiry on Hospital Transfusion Laboratories
-
Oct 7, 2026, 14:41Vikash Jaiswal: Does Timing Matter for Calcium in Pre-Eclampsia Prevention?