


David Ferreira: Identifying the True Drivers of Recurrent Thrombosis
David Ferreira, President of the General Assembly of APIH, shared a post on LinkedIn:
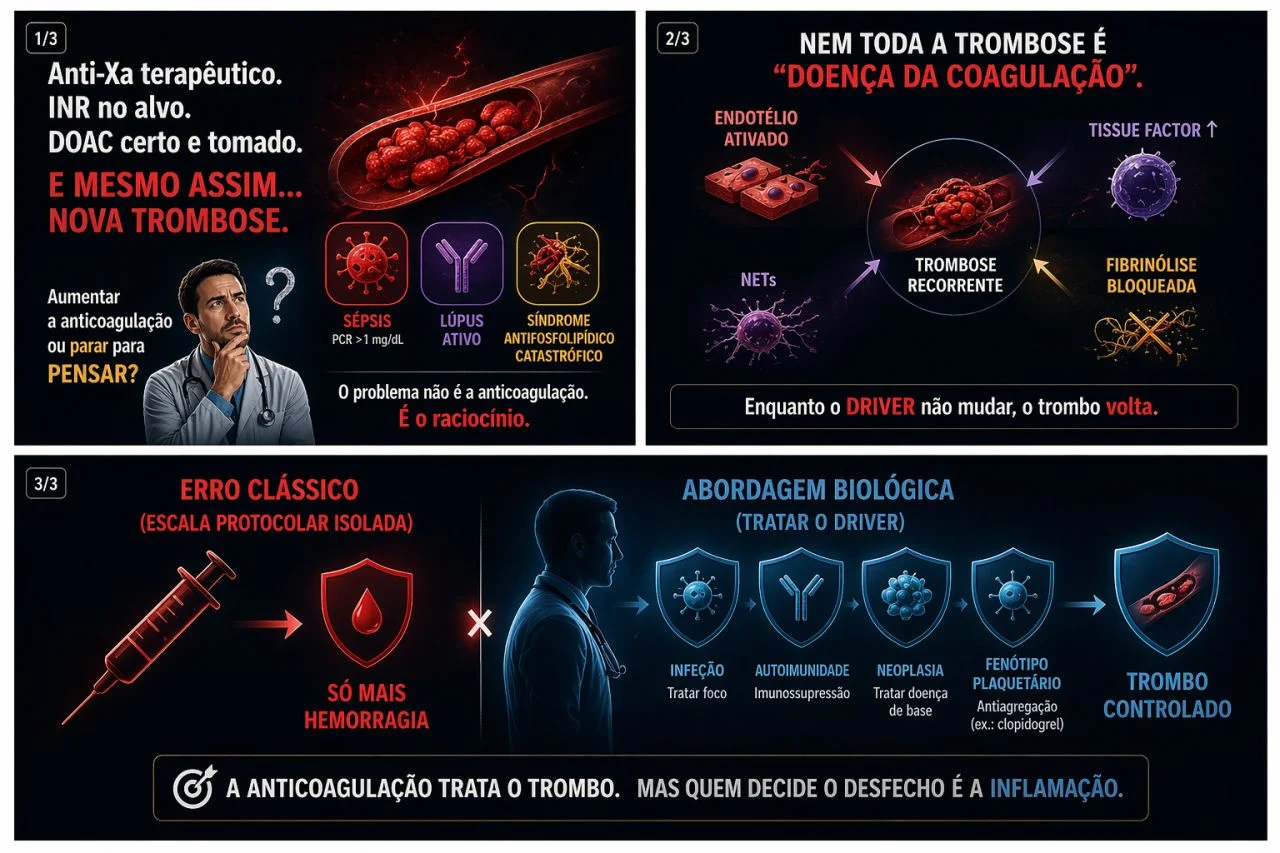
“Therapeutic anti-Xa.
INR on target.
DOAC in the right dose — and taken.
And yet… new thrombosis.
What now?
Increase hypocoagulation?
Change drugs?
Or stop for 30 seconds to think?
There is a pattern that repeats itself — and is rarely questioned: thrombosis patient – correct hypocoagulation – new thrombosis – escalate or change hypocoagulation.
Three very real examples:
- Sepsis. Activated endothelium, systemic inflammation.
Will it solve with more hypocoagulation? - Lupus Flare/ Immune system in overdrive.
Will it solve with more hypocoagulation? - Catastrophic antiphospholipid syndrome (or similar phenotype). Cascading microthrombosis, consumption.
Will it solve with more hypocoagulation?
The problem is not hypoglutilation.
It is the reasoning. We increased doses. We changed drugs.
Because these patients are not thrombosing due to ‘lack of anticoagulant.’
They are thrombosing because:
- Activated endothelium
- High tissue factor
- NETs
- blocked fibrinolysis
In a word – Thrombo-Inflammation!
The system is thus mandatorily programmed to thrombo.
And how do we respond?
More hypocoagulation, hypocoagulant exchange.
This is not therapeutic failure.
It is conceptual failure.
The right question is not ‘What’s the next hypocoagulant?’, but ‘What is fueling this thrombosis?’
And in practice, what changes?
Confirm that you are well hypocoagulated.
Search for the driver.
And then act where it matters:
- Sepsis/infection – aggressive focus control
- Active autoimmune disease – immunosuppression (e.g., corticosteroids) plus/minus targeted therapy
- Severe antiphospholipid syndrome – combined approach (hypocoagulation plus immune modulation depending on context)
- Active neoplasm – treat the underlying disease
- Arterial/platelet phenotype – consider antiplatelet therapy (e.g., clopidogrel) in an appropriate context
Hypocoagulation continues.
But it is no longer the center of the strategy.
Because the reality is this:
Hypocoagulation treats the thrombus.
But who decides the outcome… it is inflammation.
If this bothers you, great.
It’s supposed.
At the end of the day, the most important thing about auscultation is not the stethoscope.
It is between the ears of those who wear it.”
 Stay updated with Hemostasis Today.
-
Nov 18, 2026, 01:45Shikha Jha: My Takeaways from the 4th GANSID International Congress
-
Nov 18, 2026, 01:34Zeeshan Ahmed Khattak: Treatment of Fever and Neutropenia in Hematology/Oncology and Hematopoietic Cell Transplant Patients
-
Nov 17, 2026, 23:45Cajetan Reichardt: LAAO vs. OAC in AF – Balancing Nonprocedural Bleeding and Ischemic Stroke Risk
-
Nov 17, 2026, 23:42Brian Tegtmeyer: Expanding Pre-Hospital Administration of Low-Titer O Positive Whole Blood
-
Nov 17, 2026, 23:41Mansi Kala: Advancing Hematology – From Evidence to Clinical Excellence
-
Nov 17, 2026, 23:40Nathan Connell: Registered for the WFH Comprehensive Care Summit 2027 in Prague
-
Nov 17, 2026, 23:38Yaariv Khaykin: Does Reducing AF Burden After Ablation Change the Need for Anticoagulation?
-
Nov 17, 2026, 23:38Amos Gitonga Mbaabu: Strengthening Care and Advocacy for Haemophilia and SCD across Southern Africa
-
Nov 17, 2026, 23:35Muhammad Sameed Altaf: A Decade of Working Together for Thalassemia Awareness and Patient Support