

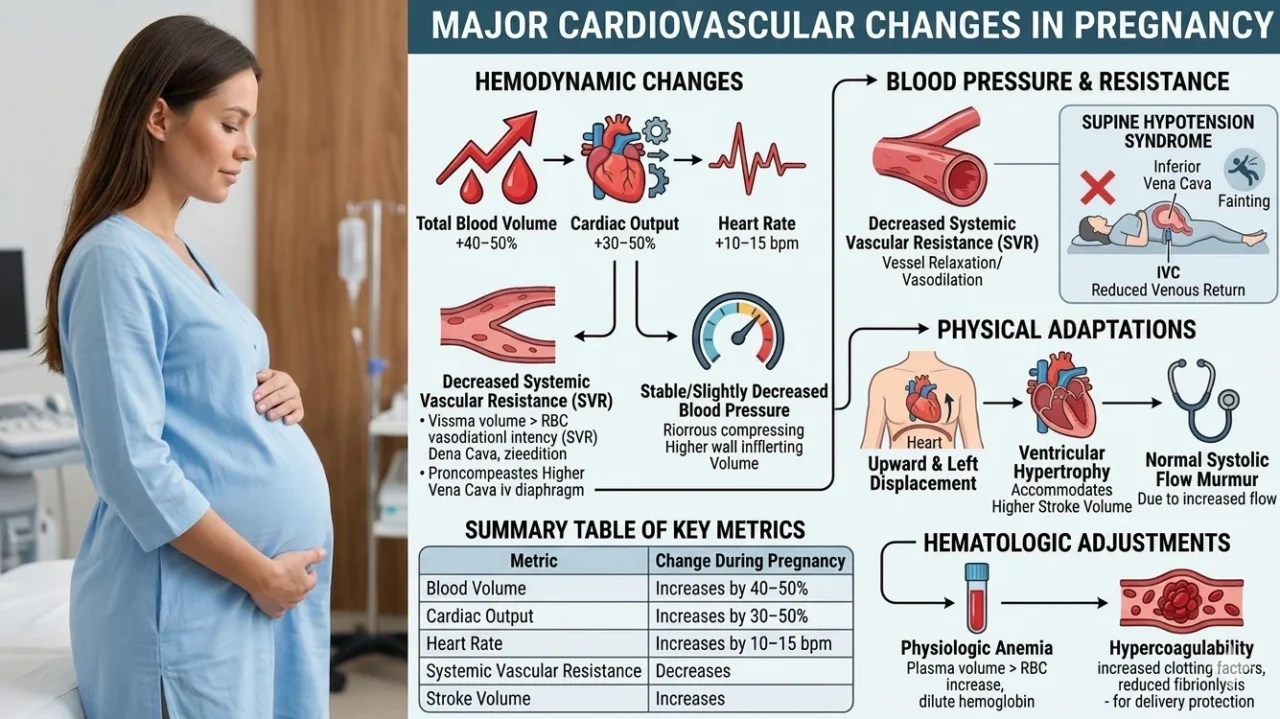
Aynetu Girma Moges: Major Cardiovascular Changes in Pregnancy
Aynetu Girma Moges, Humanitarian Aid Worker in SRH and GBV at the Ethiopian Midwives Association, shared a post on LinkedIn:
“Cardiovascular Changes (Physiological Adaptation) during Pregnancy
During pregnancy, the cardiovascular system undergoes significant adaptations to meet the increased metabolic demands of both the mother and the developing fetus.
These changes begin as early as five weeks gestation and peak during the second and third trimesters.
1. Hemodynamic changes:
The most notable shifts involve the volume and flow of blood throughout the body.
- Blood Volume Increase: Total blood volume increases by 40% to 50%. This is primarily due to an increase in plasma volume, which helps protect against the blood loss typically experienced during childbirth.
- Cardiac Output: This rises by 30% to 50%. The increase is achieved through a combination of a higher heart rate and a larger stroke volume (the amount of blood pumped with each beat).
- Heart Rate: A gradual increase occurs throughout pregnancy, typically reaching 10 to 15 beats per minute above the pre-pregnancy baseline.
2. Blood pressure and vascular resistance:
Despite the massive increase in blood volume, blood pressure usually remains stable or even decreases slightly due to changes in the blood vessels.
- Systemic Vascular Resistance (SVR): There is a marked decrease in resistance. Progesterone and nitric oxide cause the smooth muscles in the blood vessels to relax (vasodilation), which keeps blood pressure from spiking despite the extra volume.
- Blood Pressure Trends: Systolic and diastolic blood pressure often drop during the second trimester before returning to pre-pregnancy levels near the end of the third trimester.
- Supine Hypotension Syndrome: When lying flat on the back, the heavy uterus can compress the inferior vena cava, reducing blood return to the heart and causing a sudden drop in blood pressure and dizziness.
3. Physical and structural changes
The heart itself adapts physically to the increased workload.
- Heart Displacement: As the uterus grows and pushes the diaphragm upward, the heart is displaced upward and to the left.
- Ventricular Hypertrophy: The heart muscle may slightly enlarge (increase in mass) to accommodate the higher stroke volume, a process that usually reverses after delivery.
- Auscultation Changes: Because of the increased blood flow and heart displacement, it is common (and often normal) to hear a systolic flow murmur during a physical examination.
4. Hematologic adjustments
- Physiologic Anemia: While red blood cell mass increases, the plasma volume increases much more significantly. This ‘dilution’ leads to a lower hemoglobin concentration, often referred to as the physiologic anemia of pregnancy.
- Hypercoagulability: Pregnancy is a ‘pro-thrombotic’ state.”
Stay updated with Hemostasis Today.
-
Nov 18, 2026, 01:45Shikha Jha: My Takeaways from the 4th GANSID International Congress
-
Nov 18, 2026, 01:34Zeeshan Ahmed Khattak: Treatment of Fever and Neutropenia in Hematology/Oncology and Hematopoietic Cell Transplant Patients
-
Nov 17, 2026, 23:45Cajetan Reichardt: LAAO vs. OAC in AF – Balancing Nonprocedural Bleeding and Ischemic Stroke Risk
-
Nov 17, 2026, 23:42Brian Tegtmeyer: Expanding Pre-Hospital Administration of Low-Titer O Positive Whole Blood
-
Nov 17, 2026, 23:41Mansi Kala: Advancing Hematology – From Evidence to Clinical Excellence
-
Nov 17, 2026, 23:40Nathan Connell: Registered for the WFH Comprehensive Care Summit 2027 in Prague
-
Nov 17, 2026, 23:38Yaariv Khaykin: Does Reducing AF Burden After Ablation Change the Need for Anticoagulation?
-
Nov 17, 2026, 23:38Amos Gitonga Mbaabu: Strengthening Care and Advocacy for Haemophilia and SCD across Southern Africa
-
Nov 17, 2026, 23:35Muhammad Sameed Altaf: A Decade of Working Together for Thalassemia Awareness and Patient Support