

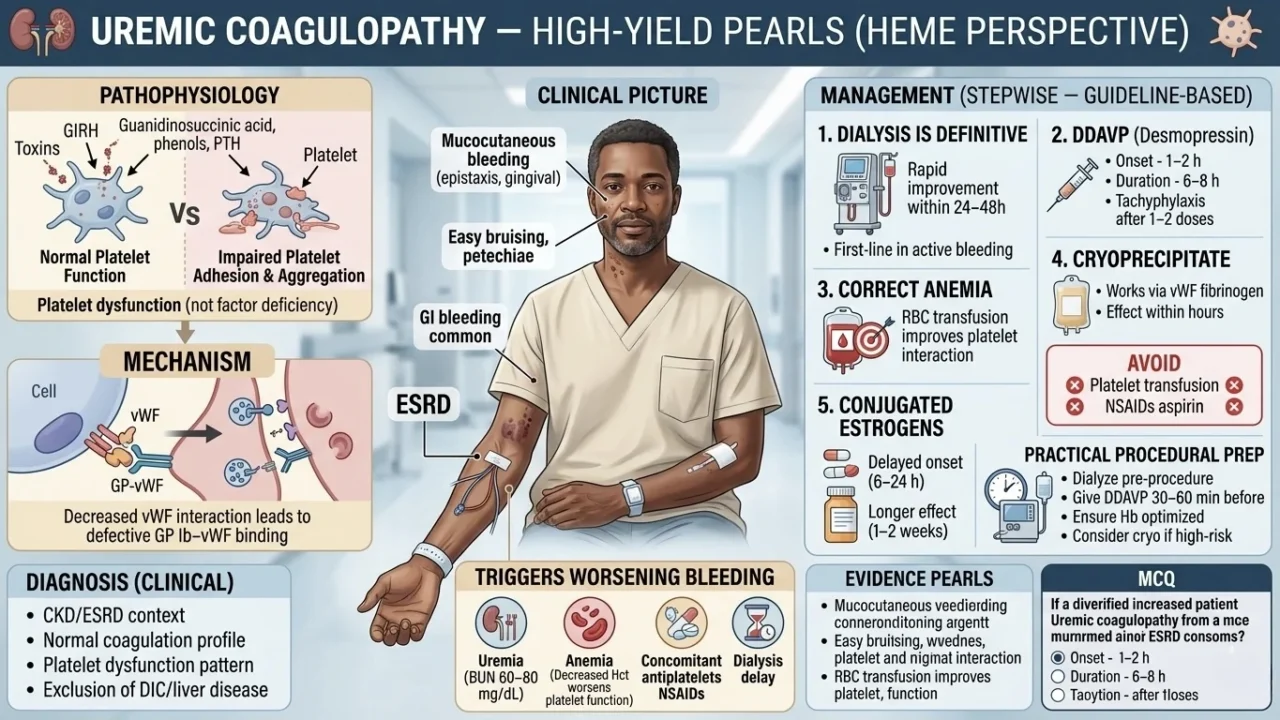
Chokri Ben Lamine: High-Yield Pearls from a Heme Perspective on Uremic Coagulopathy
Chokri Ben Lamine, Assistant Consultant at King Faisal Specialist Hospital and Research Center, shared a post on X:
“Uremic Coagulopathy — High-Yield Pearls (Heme Perspective)
- Pathophysiology is platelet dysfunction (not factor deficiency)
- Mechanism is impaired platelet adhesion with aggregation
- Key toxins include guanidinosuccinic acid, phenols, PTH
- Decreased vWF interaction leads to defective GP Ib–vWF binding
- Platelet count is usually normal
- PT/PTT is usually normal
- Bleeding time and PFA-100 is prolonged
Clinical picture
- Mucocutaneous bleeding (epistaxis, gingival)
- Easy bruising, petechiae
- GI bleeding common
- Increased Post-procedure bleeding risk
Triggers worsening bleeding
- Uremia (BUN 60–80 mg/dL)
- Anemia ( Decreased Hct worsens platelet function)
- Concomitant antiplatelets NSAIDs
- Dialysis delay
Diagnosis (clinical)
- CKD/ESRD context
- Normal coagulation profile
- Platelet dysfunction pattern
- Exclusion of DIC/liver disease
Management (stepwise — guideline-based)
1.Dialysis is definitive
- Rapid improvement within 24–48h
- First-line in active bleeding
2.DDAVP (Desmopressin)
- 0.3 mcg/kg IV over 20–30 min
- Onset – 1–2 h
- Duration – 6–8 h
- Tachyphylaxis after 1–2 doses
3.Correct anemia
- Target Hb 10 g/dL
- RBC transfusion improves platelet interaction
4.Cryoprecipitate
- If bleeding persists
- Works via vWF fibrinogen
- Effect within hours
5.Conjugated estrogens
- 0.6 mg/kg IV daily 5 days
- Delayed onset (6–24 h)
- Longer effect (1–2 weeks)
Avoid
- Platelet transfusion (limited role unless thrombocytopenia)
- NSAIDs aspirin
Practical procedural prep
- Dialyze pre-procedure
- Give DDAVP 30–60 min before
- Ensure Hb optimized
- Consider cryo if high-risk
Evidence pearls
- DDAVP is transient but effective (standard of care for urgent bleeding)
- Dialysis is cornerstone (KDIGO CKD guidelines)
- Estrogens are useful in recurrent bleeding when dialysis insufficient
MCQ
Patient with ESRD and epistaxis and normal PT and PTT:
What is the best immediate therapy?
- FFP
- Platelets
- DDAVP
- Vitamin K
Answer:
C (DDAVP) — fastest hemostatic correction
OSCE scenario
ESRD patient needs central line
Plan:
Perform dialysis, then administer DDAVP pre-procedure, optimize hemoglobin, and avoid NSAIDs”
Other posts featuring Chokri Ben Lamine on Hemostasis Today.
-
Nov 9, 2026, 09:29Veronica Sanchez: A Framework for Woman’s Health
-
Nov 8, 2026, 19:31Anna Kajaste-Rudnitski: Presenting AAV-Induced p53 Signalling in Human CNS Cells at ESGCT 26
-
Nov 8, 2026, 19:29David McIntosh: Cybersecurity Matters, but Blood Availability Remains the Bigger Challenge
-
Nov 8, 2026, 19:26Wenxue Ma: An Integrative Framework for Macrophage-Mediated Therapeutic Resistance in Cancer
-
Nov 8, 2026, 19:25Yildiz Yigit: Presenting a Polycythemia Vera Case at the MPN Subcommittee Session
-
Nov 8, 2026, 18:56Denis Oduor: Strengthening the Regulation and Delivery of Blood Transfusion and Transplantation Services
-
Nov 8, 2026, 18:28Raghavendra Rao: A Narrative Review on Chronic Venous Disease during Pregnancy
-
Nov 8, 2026, 17:57Dhiren Patel: PLD1-Derived Phospholipids Regulate NAD Kinase and ROS Production in Neutrophils
-
Nov 8, 2026, 17:48Andra T.: What Causes Antiphospholipid Syndrome? – Four Steps, not One Cause