


Chukwuemeka Amarachi: Thalassemia – Types, Diagnosis and Management
Chukwuemeka Amarachi, Medical Laboratory Scientist (BMLS), shared a post on LinkedIn:
“Thalassemia
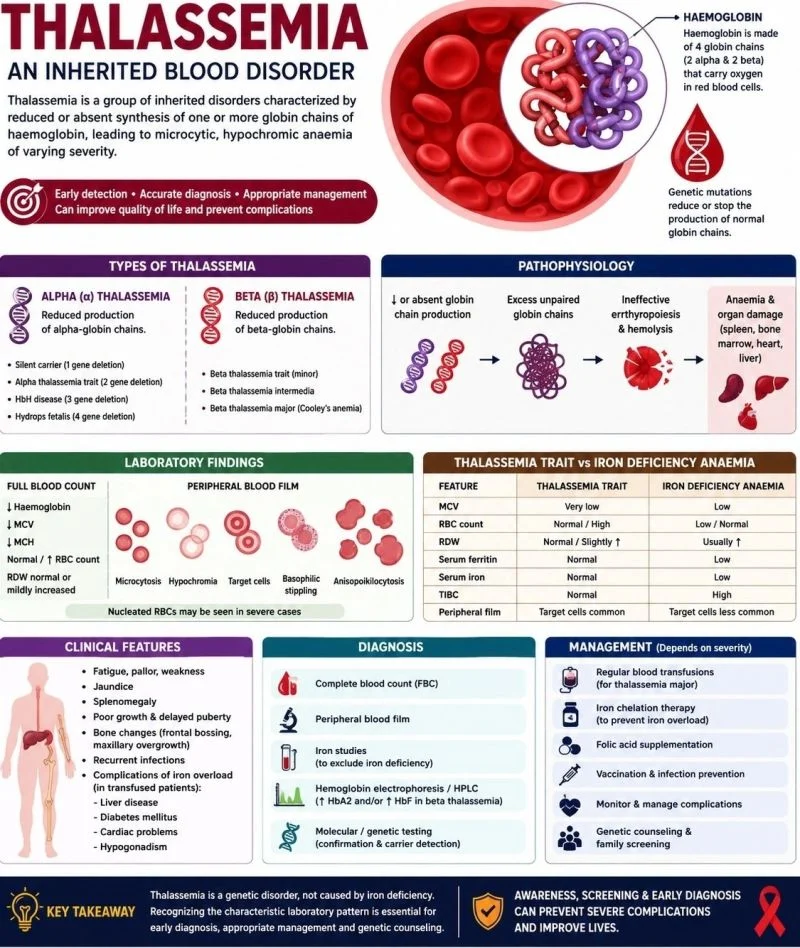
Thalassemia is an inherited blood disorder in which the body produces reduced amounts or abnormal forms of globin chains, which are components of haemoglobin.
This leads to microcytic, hypochromic anaemia of varying severity.
Types of Thalassemia
The main types are:
- Alpha (α) thalassemia – reduced production of α-globin chains.
- Beta (β) thalassemia – reduced or absent production of β-globin chains.
Beta thalassemia can be classified as:
- Minor/trait: usually mild or asymptomatic anaemia.
- Intermedia: moderate disease with variable transfusion requirements.
- Major: severe anaemia, usually presenting in early childhood and often requiring regular blood transfusions.
Signs and symptoms
Depending on severity, patients may develop:
- Pallor and fatigue
- Weakness and shortness of breath
- Jaundice
- Enlarged spleen (splenomegaly)
- Poor growth and delayed development in severe childhood disease
- Bone changes due to expansion of bone marrow
- Iron overload, particularly in patients receiving repeated transfusions
Laboratory findings
A typical blood picture may show:
- FBC
- Decreased Haemoglobin
- Decreased MCV
- Decreased MCH
- RBC count may be normal or relatively high, especially in thalassemia trait
- RDW may be normal or increased depending on the type
- Peripheral blood film
- Microcytosis
- Hypochromia
- Target cells
- Anisopoikilocytosis
- Basophilic stippling may occur
- Nucleated RBCs may appear in severe disease
Haemoglobin analysis
- Hb electrophoresis or HPLC can help identify and classify many forms, particularly β-thalassemia.
Thalassemia vs iron deficiency anaemia
- Feature – thalassemia trait – iron deficiency
- MCV – very low – low
- RBC count – often normal/high – usually low/normal
- Ferritin – usually normal – low
- Target cells – common – less prominent
- RDW – often normal/slightly high – usually high
Treatment
Treatment depends on severity and may include:
- Regular blood transfusions for severe disease
- Iron chelation when transfusion-related iron overload develops
- Folic acid in selected patients
- Management of complications
- Haematopoietic stem-cell transplantation can be potentially curative in suitable patients.
Key point: Thalassemia is genetic and is not caused by iron deficiency, although a person with thalassemia can also develop iron deficiency.”
Stay updated with Hemostasis Today.
-
Nov 21, 2026, 20:00Jeyda Star: The FAST Signs of Stroke and the Reality of Life Afterward
-
Nov 21, 2026, 19:59Daniel Lindholm: Women Showed the Largest Improvement in Stroke Risk Over Time in Heart Failure
-
Nov 21, 2026, 19:56Neil Arrowsmith: Raising Awareness of Pulmonary Embolism in Young People
-
Nov 21, 2026, 19:52Muhammad Zeeshan Jamal: Thrilled to Present Our Research on Intermediate-Risk Acute PE in Abu Dhabi
-
Nov 21, 2026, 19:50Mounisha Devireddy: Proud to Share Our Research on High-Risk PE in Pregnancy
-
Nov 21, 2026, 19:47Melissa Hollo: How Severe Anemia Increases the Odds of Acute HF During Pregnancy and Postpartum
-
Nov 21, 2026, 19:44Ashenafi Tazebew Amare: Building Sustainable Systems to Close the Anti-D Immunoglobulin Access Gap in LMICs
-
Nov 21, 2026, 19:43Sheharyar Raza: Interpreting Clotting Times Through Reptilase Time and Thrombin Time Assays
-
Nov 21, 2026, 19:42Minoo Ahmadinejad: Serving on the ISTH 2027 Scientific Theme Committee for Women’s Health