


Risika Samanta: Pediatric ITP in a 12-year-old – An Atypical Presentation without a Viral Prodrome
Risika Samanta, Student at KPC Medical College and Hospital, Member of RP Club, Research and Publication Society of KPC Medical College and Hospital, shared a post on LinkedIn:
“Pediatric ITP in a 12-year-old: An Atypical presentation without a Viral Prodrome
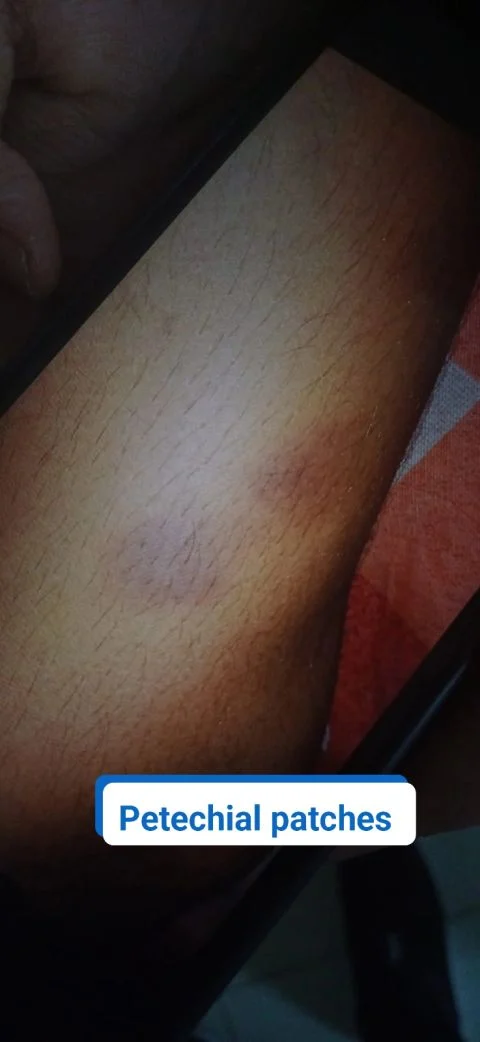
A 12-year-old boy presented with a 1-month history of multiple ecchymotic patches all over the body, in Pediatrics OPD. The patches had no increment in size, spontaneously resolved within few days.
Upon further interrogation, patient’s informant revealed that he developed gum bleeding (‘wet purpura’). No history of any viral fever, major trauma, bone pain, weight loss, or lymphadenopathy.
Key findings in investigations:
- CBC: Isolated thrombocytopenia (platelets in the range of 25,000- 50,000/mm³) with normal Hb and WBC.
- Peripheral smear: Large platelets (suggestive of ITP)
- Coagulation profile (PT and aPTT): Normal (these exclude coagulopathy)
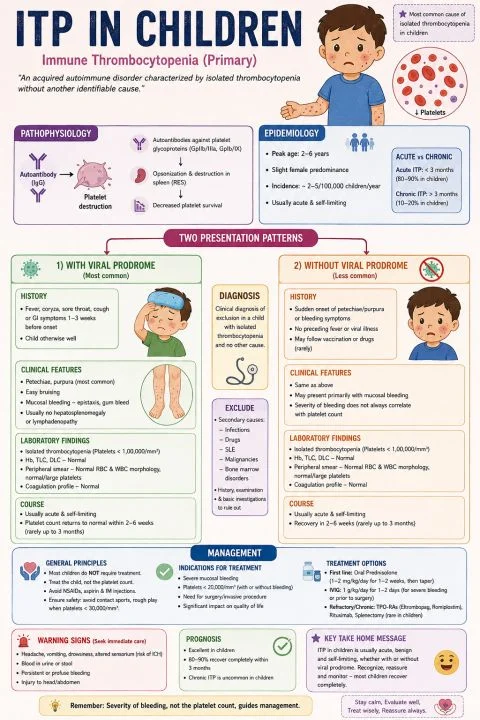
So, the case was finally diagnosed as Immune Thrombocytopenic Purpura (ITP) – a ‘diagnosis of exclusion’ (Neo-Antibody detection has very low specificity, hence diagnosed via ruling out other diagnoses) characterized by isolated thrombocytopenia because of the autoimmune destruction of glycoproteins (Gplb/lX, Gpllb/llla) present on the platelets which are crucial for platelet adhesion, aggregation during primary hemostasis.
Generally, in children, this happens after 1-2 weeks after a viral infection (less severe and self limiting). But, only in 20% cases, it happens without viral Prodrome and can appear very severe.
Management:
- As per first-line therapy for ITP, IVIG: 0.8–1 g/kg single dose is given.
- short-course corticosteroids: Prednisolone 2–4 mg/kg/day for 1–2 weeks is given, then taper.
- As, the patient’s platelet was severely low, transfusion was done twice and platelet was monitored time to time.
- Proper counselling was done on bleeding precautions, avoid NSAIDs and contact sports, and close follow-up as this can recur later (especially, this is not self-limiting and without viral Prodrome).
Stay updated with Hemostasis Today.
-
Nov 20, 2026, 17:27Adam Bryant: Great Science, Valuable Connections and a Wonderful Haematology Community at Blood 2026
-
Nov 20, 2026, 17:25Gurpreet Kaurr: Scientific Discussions, New Perspectives and Inspiration at HAEMATOCON 2026
-
Nov 20, 2026, 17:24Bispecific FVIIIa-Mimetic Antibodies in Haemophilia A – CRH French Reference Center for Hemophilia Lyon
-
Nov 20, 2026, 17:23Khalid Rehman: Psychosocial Burden Among Caregivers of Patients with Beta-Thalassemia Major in Pakistan
-
Nov 20, 2026, 17:20Dhinesh Selvaraju: Caplacizumab Becomes the First FDA-Approved Treatment for Pediatric aTTP
-
Nov 20, 2026, 17:19Paris Margaritis: Presenting Preclinical Data on GENV-HEM at the WFH Workshop
-
Nov 20, 2026, 17:18WFH Opens Public Comment on Draft Guidelines for Hemostatic Agents and Prophylaxis
-
Nov 20, 2026, 17:18Ketan Asawale: Consensus on the Management of Cancer-Associated Thrombosis in India
-
Nov 20, 2026, 17:16Ajay Samkaria: The Evolution of Hemostasis Diagnostics with the ACL TOP 70 Series