


Alexsander Santiago: Tranexamic Acid – Why Timing Matters in Critical Bleeding
Alexsander Santiago, Health Education Coordinator at Terapia Intensiva em Foco, shared a post on LinkedIn:
“Tranexamic acid is not about ‘stopping bleeding.’
It is about buying time before physiology collapses.
And in critical care, that difference matters.
We often discuss TXA as if it were a universal hemostatic reflex:
- Patient bleeding – give tranexamic acid.
But that is not good enough.
Because the real question is not:
- ‘Is there blood loss?’
The real question is:
- ‘Is this a time-sensitive bleeding phenotype in which fibrinolysis is part of the problem and early treatment can still change the trajectory?’
That is where TXA becomes clinically meaningful.
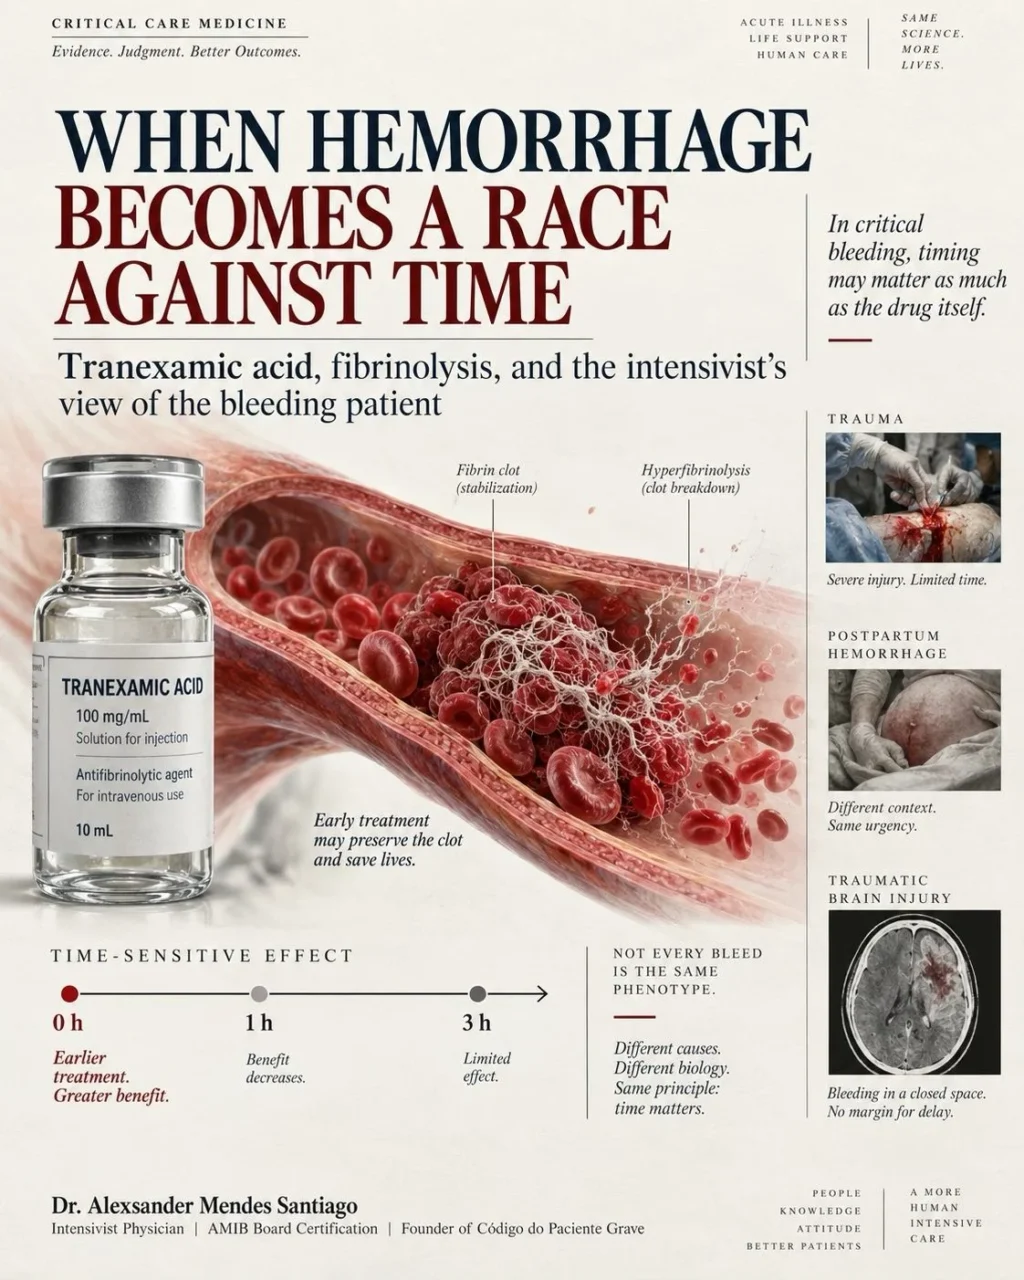
In trauma, timing changed the conversation.
In postpartum hemorrhage, timing changed the conversation.
In selected traumatic brain injury, timing still matters because bleeding in a closed space leaves little margin for delay.
The lesson is bigger than the drug itself:
- Critical bleeding is not only about volume loss.
- It is about tempo.
- A patient can still be bleeding before shock is fully declared.
- A clot can still be salvageable before hemodynamic collapse becomes obvious.
- A trajectory can still be reversible before organ failure becomes the dominant story.
That is why I think TXA should not be framed as a ‘bleeding drug.’
It is better understood as a time-sensitive antifibrinolytic tool.
And like every serious tool in the ICU, its value depends on context.
Not every hypotensive patient is bleeding.
Not every bleed is driven by hyperfibrinolysis.
Not every hemorrhagic situation benefits equally.
And not every late intervention deserves to be called a missed miracle.
Sometimes the mistake is not failing to give TXA.
Sometimes the mistake is failing to think early enough.
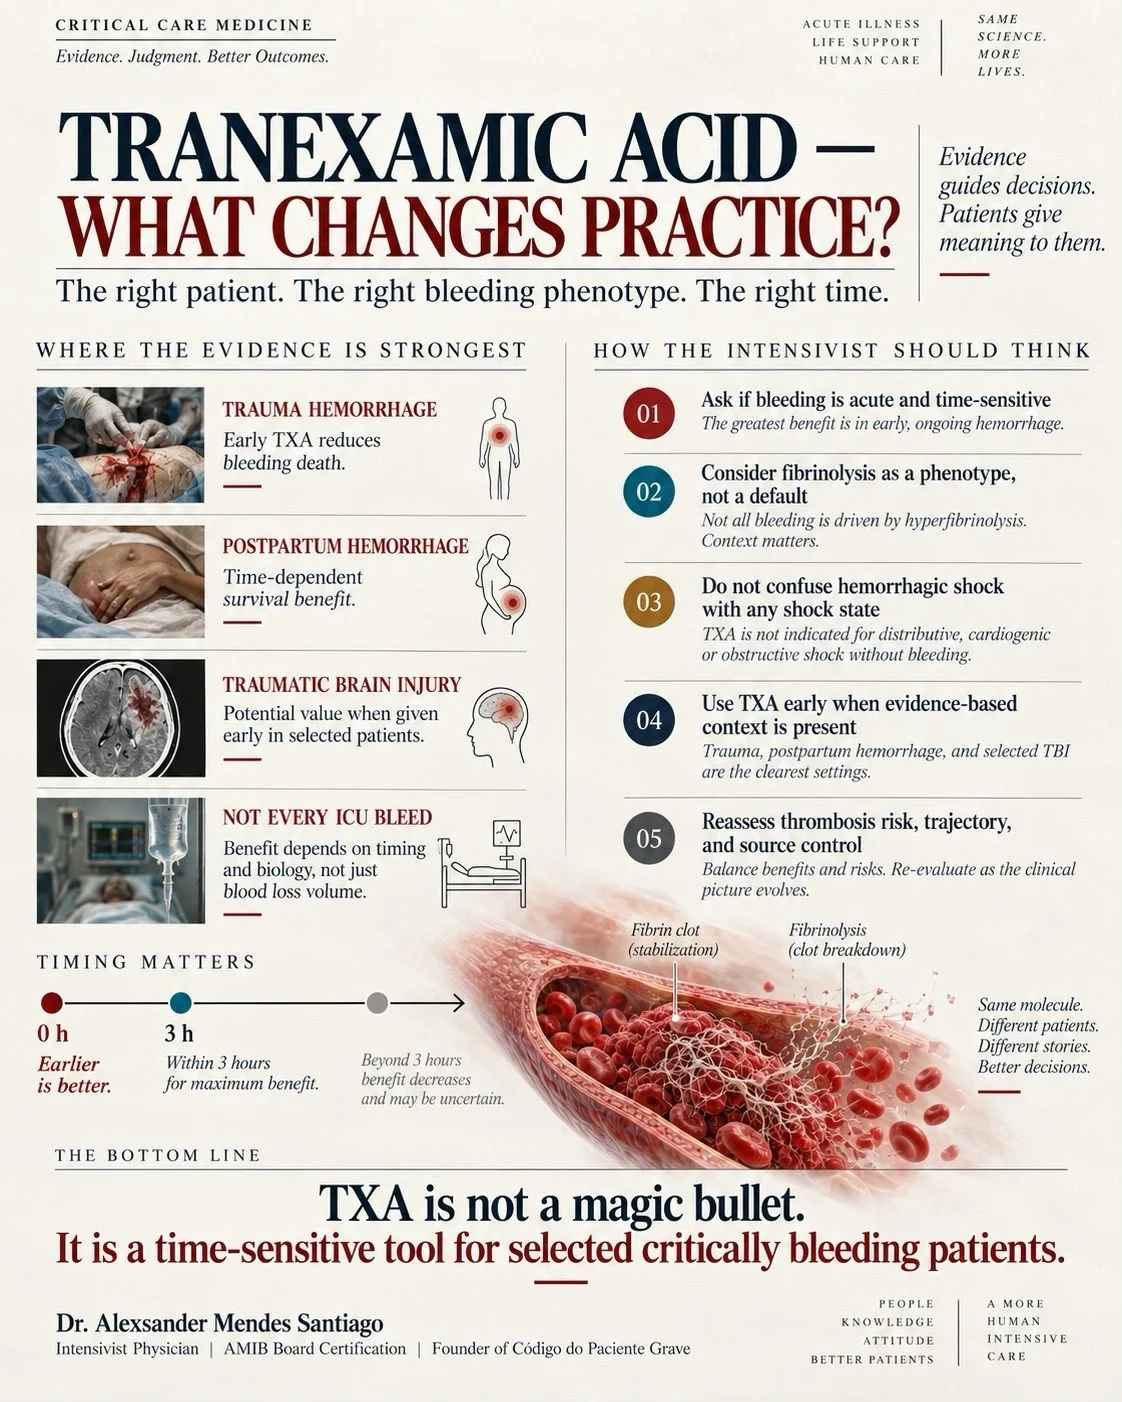
For the intensivist, the reasoning should be practical:
- Is this an acute, clinically significant hemorrhage?
- Is the patient still within a window where biology can be modified?
- Is fibrinolysis plausibly contributing to ongoing loss?
- Is this one of the settings where evidence is strongest?
- Have we remembered that TXA never replaces source control, resuscitation, and organ support?
Because TXA does not rescue bad reasoning.
It only helps when sound reasoning reaches the patient on time.
That may be the most important message:
- TXA is not magic.
- It is timing, phenotype, and judgment.
And in the critically bleeding patient, those three things can be the difference between stabilization and collapse.”
Stay updated with Hemostasis Today.
-
Nov 13, 2026, 16:17Shailendra Singh: Bombay Hospital Jaipur Inaugurates New Facility with Voluntary Blood Donation Camp
-
Nov 13, 2026, 16:10Minka Zivkovic: UMC Utrecht Announces Research Analyst Vacancy in Thrombosis and Haemostasis
-
Nov 13, 2026, 16:02Rounak Dubey: Elsevier’s Upcoming Handbook Explores Digitalization in Transfusion Medicine
-
Nov 13, 2026, 15:50Maha Othman: CanVECTOR 2026 Highlights Research on Immunothrombosis and Cancer-Associated Thrombosis
-
Nov 13, 2026, 15:48Cedric Hermans: Advances in Gene Therapy for Haemophilia A
-
Nov 13, 2026, 15:45Strengthens Global Collaboration in Thrombosis and Hemostasis for 2027 – ISTH
-
Nov 13, 2026, 15:42David McIntosh: The Global Blood Shortage Crisis and the Urgent Need for National Action
-
Nov 13, 2026, 15:41JTH Highlights Future Directions in Thromboprophylaxis for Hospitalized Children
-
Nov 13, 2026, 15:21Wolfgang Miesbach։ Gene Therapy for Haemophilia B Is Cheaper Than Lifelong Factor IX Prophylaxis in Sweden