


David Ferreira: Identifying the True Drivers of Recurrent Thrombosis
David Ferreira, President of the General Assembly of APIH, shared a post on LinkedIn:
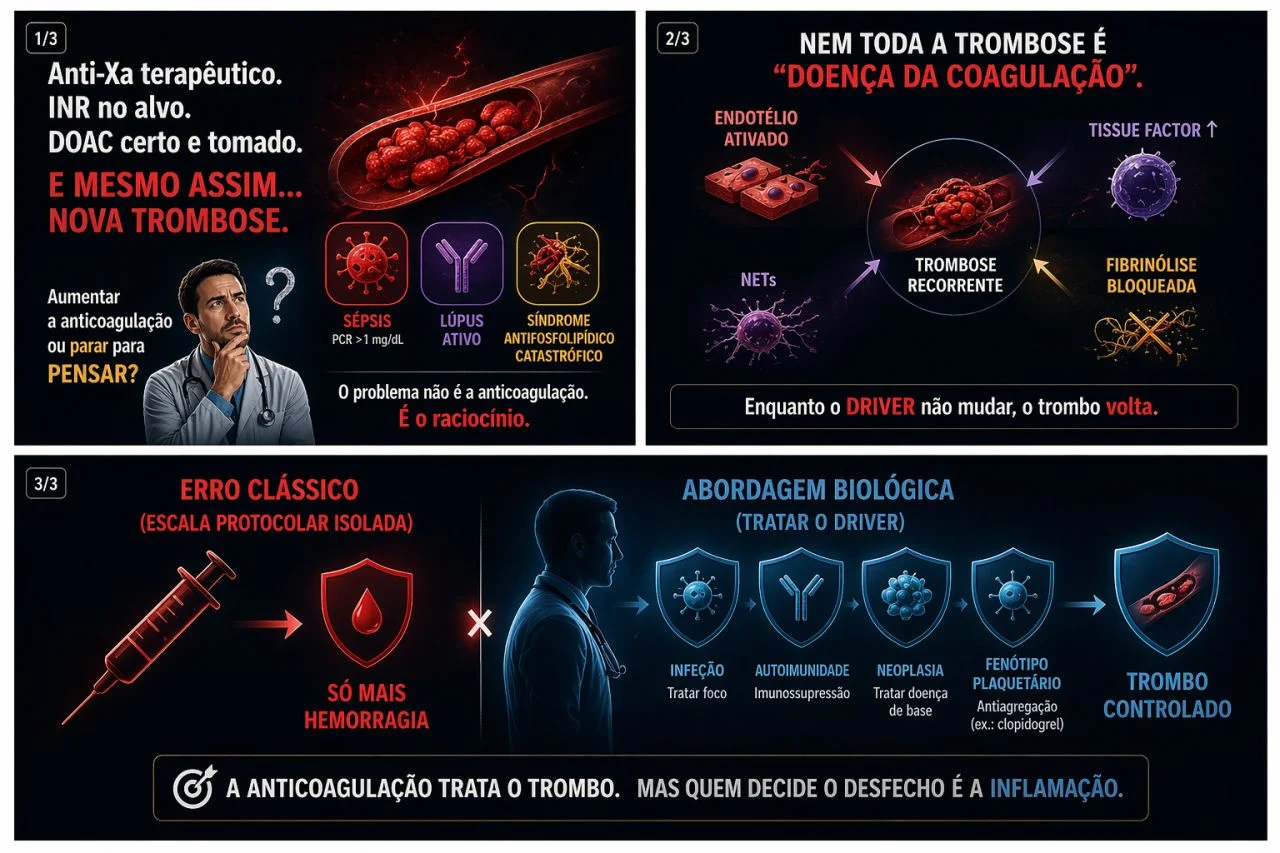
“Therapeutic anti-Xa.
INR on target.
DOAC in the right dose — and taken.
And yet… new thrombosis.
What now?
Increase hypocoagulation?
Change drugs?
Or stop for 30 seconds to think?
There is a pattern that repeats itself — and is rarely questioned: thrombosis patient – correct hypocoagulation – new thrombosis – escalate or change hypocoagulation.
Three very real examples:
- Sepsis. Activated endothelium, systemic inflammation.
Will it solve with more hypocoagulation? - Lupus Flare/ Immune system in overdrive.
Will it solve with more hypocoagulation? - Catastrophic antiphospholipid syndrome (or similar phenotype). Cascading microthrombosis, consumption.
Will it solve with more hypocoagulation?
The problem is not hypoglutilation.
It is the reasoning. We increased doses. We changed drugs.
Because these patients are not thrombosing due to ‘lack of anticoagulant.’
They are thrombosing because:
- Activated endothelium
- High tissue factor
- NETs
- blocked fibrinolysis
In a word – Thrombo-Inflammation!
The system is thus mandatorily programmed to thrombo.
And how do we respond?
More hypocoagulation, hypocoagulant exchange.
This is not therapeutic failure.
It is conceptual failure.
The right question is not ‘What’s the next hypocoagulant?’, but ‘What is fueling this thrombosis?’
And in practice, what changes?
Confirm that you are well hypocoagulated.
Search for the driver.
And then act where it matters:
- Sepsis/infection – aggressive focus control
- Active autoimmune disease – immunosuppression (e.g., corticosteroids) plus/minus targeted therapy
- Severe antiphospholipid syndrome – combined approach (hypocoagulation plus immune modulation depending on context)
- Active neoplasm – treat the underlying disease
- Arterial/platelet phenotype – consider antiplatelet therapy (e.g., clopidogrel) in an appropriate context
Hypocoagulation continues.
But it is no longer the center of the strategy.
Because the reality is this:
Hypocoagulation treats the thrombus.
But who decides the outcome… it is inflammation.
If this bothers you, great.
It’s supposed.
At the end of the day, the most important thing about auscultation is not the stethoscope.
It is between the ears of those who wear it.”
 Stay updated with Hemostasis Today.
-
Sep 30, 2026, 01:52Javed Anees: DADA2 – When a Young Stroke Is More Than a Stroke
-
Sep 30, 2026, 01:51How a Venous Thrombus Becomes Revascularized – ISTH
-
Sep 29, 2026, 22:45Victor Agunyego: Paracetamol – The Most Common Drug We Underestimate
-
Sep 29, 2026, 22:42Nova Sinclair: Advancing the Future of Hematology – Meet Our 2027 Organizing Committee
-
Sep 29, 2026, 22:41Lorenz Räber: Intracoronary Imaging in PCI – Why, When, How, and Which Modality?
-
Sep 29, 2026, 22:31Selma Turkovic: Pleased to Deliver the Opening Presentation at Kingston Hospital
-
Sep 29, 2026, 22:31Miguel Teran: Ultrasound and Simulation in Arterial Blood Sampling
-
Sep 29, 2026, 22:28Mohammad Refaei: Navigating Your Career in Hematology From Training to Practice
-
Sep 29, 2026, 22:27Matteo Foschi: 10 Clinical Pearls for Antithrombotic Therapy in Secondary Stroke Prevention