


Heba Youssef: When to Start Anticoagulation Therapy After Intracerebral Hemorrhage
Heba Youssef, Clinical Nutrition pharmacist at Helwan General Hospital, shared a post on LinkedIn:
“Timing Anticoagulation After Intracerebral Hemorrhage – One of the Hardest Calls in ICU
Few decisions in neurocritical care demand as much clinical judgment as this one:
When – if ever – do we restart anticoagulation after an intracranial hemorrhage?
Start too early – risk of catastrophic rebleeding.
Wait too long – life-threatening thromboembolism.
There is no universal answer.
But there is a framework.
The guiding principle: Individualization over protocol
Anticoagulation is almost always delayed after ICH – but the exact timing must be tailored to each patient’s unique risk profile, weighing hemorrhagic risk against thromboembolic risk with precision.
Before any restart is even considered
A structured pre-restart checklist should be non-negotiable:
- Hematoma stability confirmed on repeat CT.
- No evidence of active or ongoing bleeding.
- Blood pressure rigorously controlled.
- Neurological status stable.
Factors that shape the decision
Favoring earlier restart:
- Mechanical heart valves.
- Recent massive PE.
- High-risk DVT.
Favoring delayed restart:
- Large lobar hemorrhage
- Cerebral amyloid angiopathy (CAA)
- Uncontrolled hypertension.
- Elderly patients with multiple comorbidities.
Suggested timelines – a framework, not a formula
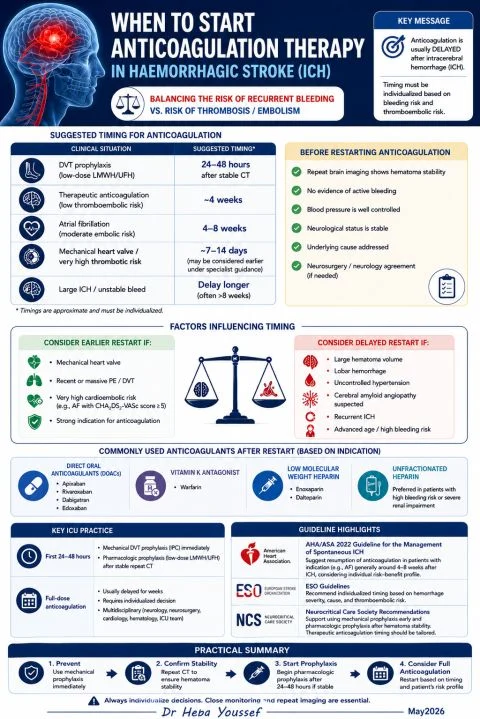
Indication , Suggested Window
- DVT Prophylaxis – 24–48 hrs post stable CT
- High-Risk Thrombosis (e.g., mechanical valves) – approximately 7–14 days (specialist-guided)
- Atrial Fibrillation (moderate risk) – 4–8 weeks
These windows are informed by the AHA/ASA 2022 ICH Guidelines, ESO Guidelines, and Neurocritical Care Society recommendations — but every case requires multidisciplinary input and serial reassessment.
This is not a decision made once.
It requires:
- Repeat imaging
- Multidisciplinary team collaboration
- Ongoing risk-benefit reassessment
I’ve developed a comprehensive infographic summarizing these principles as a practical decision-support tool for clinicians navigating this challenge at the bedside.
Save it. Share it with your team.
And I’d love to hear how your institution approaches this – drop your protocol or experience in the comments.”
Stay updated with Hemostasis Today.
-
Nov 16, 2026, 15:35Jim Hoffman: Could Blood Purification Change the Fight Against Cancer?
-
Nov 16, 2026, 15:16How Do Artificial Hearts Affect Platelet Function? – Platelets Journal
-
Nov 16, 2026, 15:10Assessing Coagulation Activation in DOAC – Treated Patients – JTH
-
Nov 16, 2026, 15:00Davide Antonio Mei: Should Anticoagulation Continue After AF Ablation?
-
Nov 16, 2026, 14:55Danielle Boyle: Beyond Platelet Counts – Why Patient Stories Matter
-
Nov 16, 2026, 14:28Jan Sloves: The Future of Vascular Ultrasound
-
Nov 16, 2026, 13:49Bahman Rasouli: A Rare Vascular Manifestation of Recurrent Papillary Thyroid Carcinoma
-
Nov 16, 2026, 13:28Muhammad Danyal: Platelet Patterns in Hepatitis B and C
-
Nov 16, 2026, 12:52Frank Nocken: Alzheimer’s Research Expands Beyond Amyloid-Based Treatments