


Risika Samanta: Pediatric ITP in a 12-year-old – An Atypical Presentation without a Viral Prodrome
Risika Samanta, Student at KPC Medical College and Hospital, Member of RP Club, Research and Publication Society of KPC Medical College and Hospital, shared a post on LinkedIn:
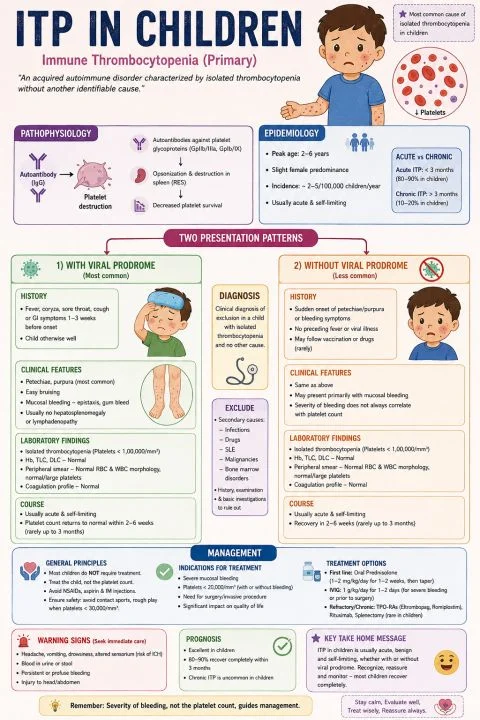
“Pediatric ITP in a 12-year-old: An Atypical presentation without a Viral Prodrome
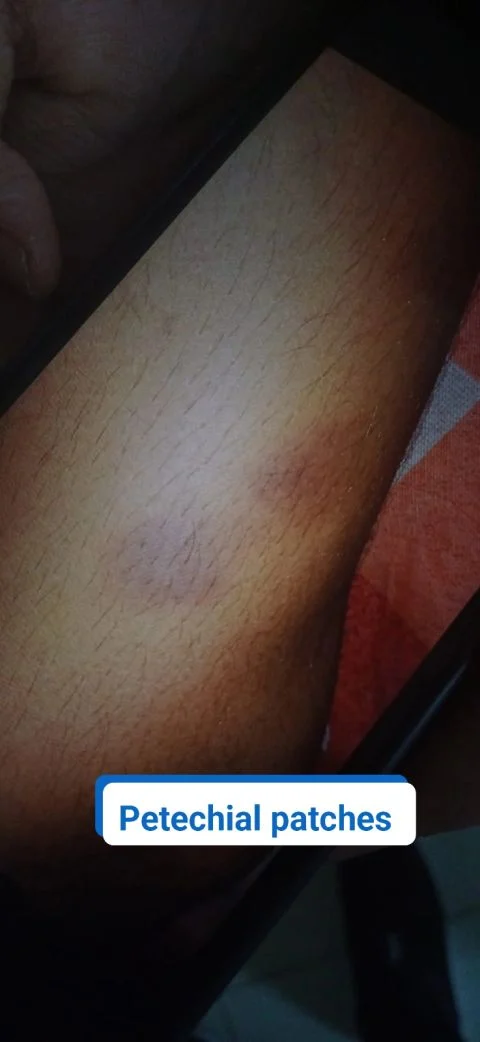
A 12-year-old boy presented with a 1-month history of multiple ecchymotic patches all over the body, in Pediatrics OPD. The patches had no increment in size, spontaneously resolved within few days.
Upon further interrogation, patient’s informant revealed that he developed gum bleeding (‘wet purpura’). No history of any viral fever, major trauma, bone pain, weight loss, or lymphadenopathy.
Key findings in investigations:
- CBC: Isolated thrombocytopenia (platelets in the range of 25,000- 50,000/mm³) with normal Hb and WBC.
- Peripheral smear: Large platelets (suggestive of ITP)
- Coagulation profile (PT and aPTT): Normal (these exclude coagulopathy)
So, the case was finally diagnosed as Immune Thrombocytopenic Purpura (ITP) – a ‘diagnosis of exclusion’ (Neo-Antibody detection has very low specificity, hence diagnosed via ruling out other diagnoses) characterized by isolated thrombocytopenia because of the autoimmune destruction of glycoproteins (Gplb/lX, Gpllb/llla) present on the platelets which are crucial for platelet adhesion, aggregation during primary hemostasis.
Generally, in children, this happens after 1-2 weeks after a viral infection (less severe and self limiting). But, only in 20% cases, it happens without viral Prodrome and can appear very severe.
Management:
- As per first-line therapy for ITP, IVIG: 0.8–1 g/kg single dose is given.
- short-course corticosteroids: Prednisolone 2–4 mg/kg/day for 1–2 weeks is given, then taper.
- As, the patient’s platelet was severely low, transfusion was done twice and platelet was monitored time to time.
- Proper counselling was done on bleeding precautions, avoid NSAIDs and contact sports, and close follow-up as this can recur later (especially, this is not self-limiting and without viral Prodrome).
Stay updated with Hemostasis Today.
-
Oct 5, 2026, 22:25Allie Boutin: Raising Awareness and Supporting the Community During ITP Awareness Month
-
Oct 5, 2026, 15:31Irma Bagdoniene: Multidisciplinary Management of High-Risk Familial Hypercholesterolaemia and CAD
-
Oct 5, 2026, 15:00Serena Williams and Pulmonary Embolism: From Personal Crisis to Lessons in Venous Thromboembolism
-
Oct 5, 2026, 14:55Marco Moscarelli: 3D Reconstruction Enhances Volumetric Assessment of Post-TAVI Thrombosis
-
Oct 5, 2026, 13:24Abdul Muqtadir Abbasi: Diagnostic Pearls for Evaluating Isolated Thrombocytopenia in Residents
-
Oct 5, 2026, 13:16Katerina Pavenski: Rethinking What ‘Normal’ Means for Iron Deficiency
-
Oct 5, 2026, 13:09Rick Matthews: Balancing Established VTE Partnerships with Innovative Interventional Technologies
-
Oct 5, 2026, 13:01Nawsherwan Mohammad: Recognizing TTP Before the ADAMTS13 Result Arrives
-
Oct 5, 2026, 12:51Bruno Pougault: The Hidden Challenges Behind Anti Xa Testing