


Thirunavukkarasu Angappan/LinkedIn
Nov 20, 2026, 12:29
Thirunavukkarasu Angappan: Antithrombin in ECMO – Two Datasets, Two Opposite Answers
Thirunavukkarasu Angappan, Vice President of Operations and Manufacturing at PopVax, shared a post on LinkedIn:
“Antithrombin in ECMO: two datasets, two opposite answers
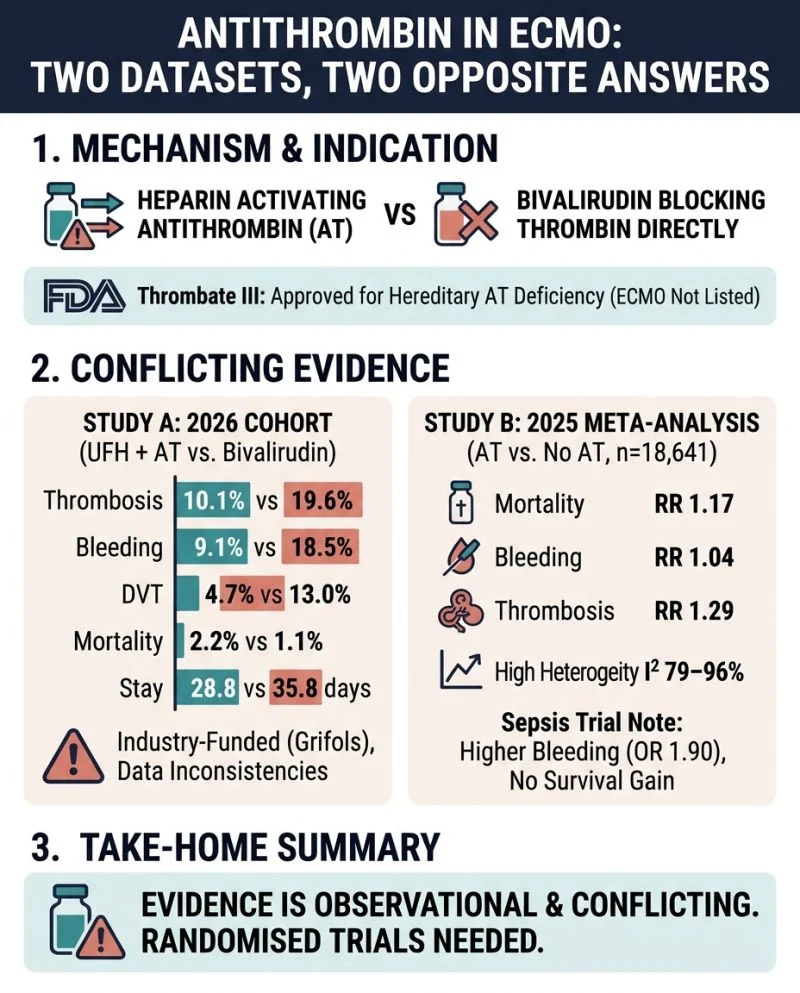
Heparin works by activating antithrombin (AT). So when heparin seems to fail in patients on extracorporeal membrane oxygenation (ECMO, a heart and lung support machine), some centres add human AT concentrate. Does it help? Two studies point in opposite directions.
- Study A (2026, retrospective cohort): adults on ECMO given unfractionated heparin (UFH) plus AT concentrate versus bivalirudin, a drug that blocks thrombin directly and needs no AT. After matching: 276 patients per group in TriNetX (a US health-record network) and 264 per group in Premier (a US hospital database).
- What Arenella et al. found: thrombosis 10.1% versus 19.6% (adjusted odds ratio 0.41; 95% confidence interval, CI, 0.24 to 0.69). Bleeding 9.1% versus 18.5% (0.38; 0.21 to 0.65). Deep vein thrombosis 4.7% versus 13.0%. Hospital mortality 2.2% versus 1.1%, p = 0.50. Premier stay: 28.8 versus 35.8 days.
- Read with care: Grifols, a maker of AT concentrate, funded the study; 3 of 6 authors are Grifols employees, and two more report consulting or advisory ties. Heparin resistance had no consistent definition. The paper’s totals do not add up, and bivalirudin stay is 35.8 days in the table but 35.5 in the text.
- Study B (2025 meta-analysis): Zeng et al. pooled six studies, one randomised trial of 48 patients and five retrospective cohorts, 18,641 patients. AT versus none: mortality risk ratio 1.17 (0.85 to 1.60), bleeding 1.04 (0.90 to 1.21), thrombosis 1.29 (0.81 to 2.05). Studies disagreed strongly (I² of 79% to 96%; I² measures inconsistency between studies).
- Subgroups pointed both ways: in cardiac ECMO, mortality risk ratio 1.60 but thrombosis 0.45; in adults, thrombosis 2.55. Zeng et al. note the cardiac mortality signal rests mainly on one study of 9,193 patients, and the adult result may be a false positive.
- A sepsis warning (not ECMO): Tsuchida et al. pooled 7 randomised trials (2,647 patients): no survival benefit (odds ratio 0.88; 0.67 to 1.16). Bleeding was higher with AT (odds ratio 1.90; 1.52 to 2.37), pooled from three trials.
- Why the answers differ: Study A compares AT plus heparin with a different anticoagulant. Study B compares AT with no AT, mostly in retrospective data. Different questions, different patients.
- On the label: the US Food and Drug Administration lists Thrombate III for hereditary AT deficiency. ECMO is not a listed indication.
- Synthesis: AT concentrate may help selected patients, such as those with proven AT deficiency, but the evidence in ECMO is observational and conflicting. The 2026 result is a hypothesis from industry-funded data. A randomised trial is needed.
Would you give AT concentrate by a measured AT level, or by a clinical suspicion of heparin resistance?”
Other posts featuring Thirunavukkarasu Angappan on Hemostasis Today.
-
Nov 20, 2026, 11:38Muhammad Kashif: Therapeutic Plasma Exchange – Key Concepts at a Glance
-
Nov 20, 2026, 11:33Tyler McConville: Why Hemostatic Function Matters More Than Cell Counts in Trauma and Transfusion
-
Nov 20, 2026, 11:28Stéphanie Forté: Bringing Cutting-Edge Genomic and Proteomic Tools to Sickle Cell Disease Patients
-
Nov 20, 2026, 11:19EHC Urges Equal Early Diagnosis for Bleeding Disorders
-
Nov 20, 2026, 11:14Pushpinder Singh: How Do We Know if Haemodialysis is Effective?
-
Nov 20, 2026, 11:09Neel Patel: Honoured to Serve Across Five Faculty Roles at Hematocon 2026
-
Nov 20, 2026, 11:03Alok Khorana: First FXI Inhibitor Approved in the US
-
Nov 20, 2026, 06:51How YERM Shapes the Careers of Future Hematology Researchers – EHA
-
Nov 20, 2026, 06:44Ann Van De Velde: Emerging Advances in Hemoglobinopathies, Sickle Cell Disease and Rare Anemias