


AbQader Bedil: A Practical Diagnostic Workflow for Von Willebrand Disease
AbQader Bedil, Medical Laboratory Technologist at French Medical Institute for Mothers and Children- FMIC, Laboratory Incharge at Stanikza Diagnostic clinic, shared a post on LinkedIn:
“Von Willebrand disease (VWD)
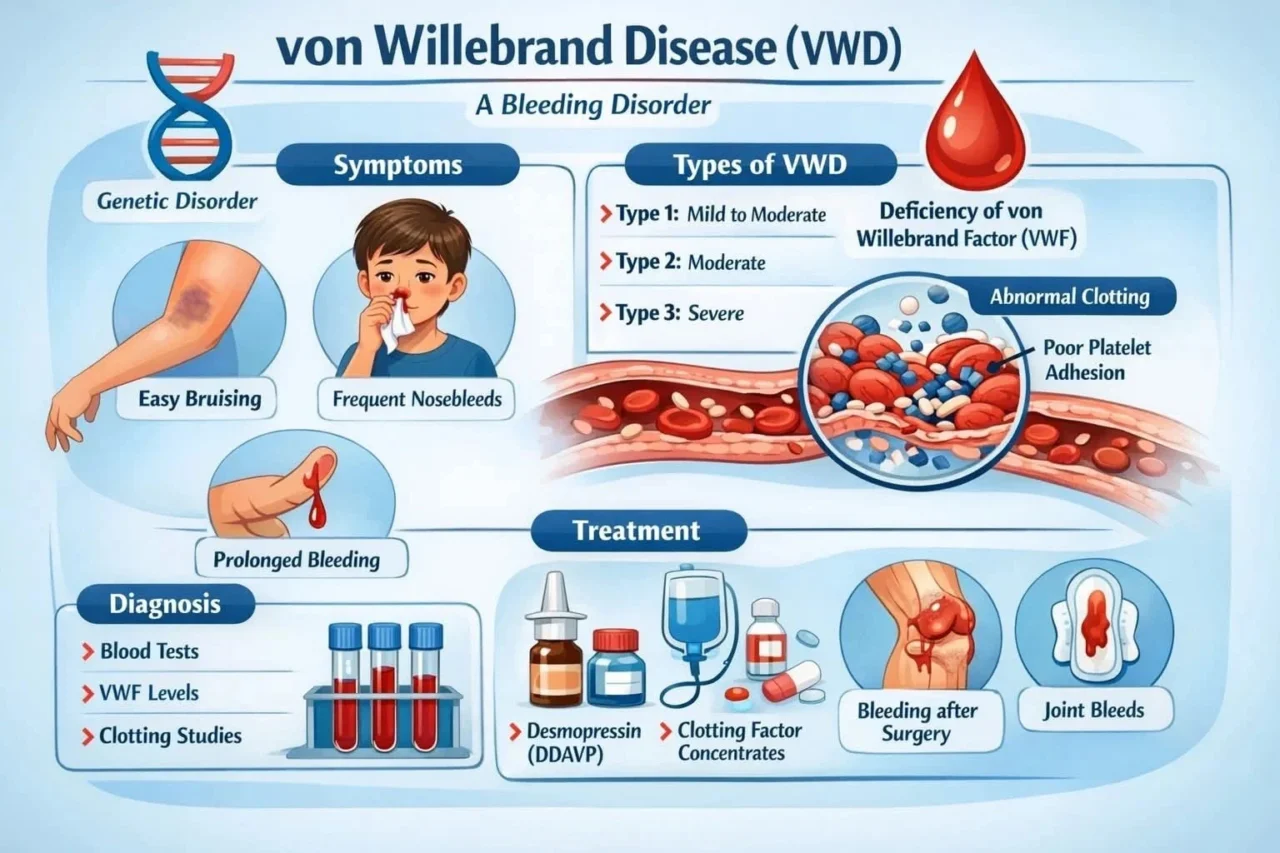
VWD is the most common inherited bleeding disorder — and also the one that most often gets misdiagnosed because people order the wrong single test and trust the result.
Here’s a fast, practical workflow you can use.
1․ Who to test:
Test when there’s a bleeding history (mucosal bleeding, heavy menstrual bleeding, excessive bleeding after procedures) or a first-degree relative with VWD.
Use a bleeding assessment tool (BAT) when possible to document severity.
2․ First-line lab panel
Run VWF antigen (VWF:Ag), a platelet-dependent VWF activity assay (modern: VWF:GPIbM or equivalent; legacy: VWF:RCo) and factor VIII activity (FVIII:C) together as the initial screen.
Don’t rely on a single isolated number.
3․ Interpretation quick rules
Per the guideline cutoffs, VWF level(s) less than0.30 IU/mL (VWF:Ag or activity) support type 1 VWD; in patients with bleeding, levels less than 0.50 IU/mL are also clinically important.
Repeat testing off acute illness and outside of pregnancy/estrogen exposure when feasible.
4․ Which activity assay
Newer assays that measure VWF binding to recombinant GPIb (eg VWF:GPIbM) are generally preferred over the old ristocetin cofactor (VWF:RCo) because they are more reproducible and less operator-dependent.
If your lab still uses VWF:RCo, flag the limitations in the report.
5․ When to send extra tests
If activity less than antigen (low ratio) or abnormal multimer pattern, then consider VWF multimer analysis, VWF collagen binding (VWF:CB) and targeted genetic testing for suspected type 2 variants.
For suspected type 2B, targeted genetic testing is preferred over low-dose RIPA where available.
6․ Common pitfalls labs must call out
Blood type O reduces baseline VWF by approximately 25% — say that in the comment. Acute-phase reactions, pregnancy, estrogen therapy and recent desmopressin can raise VWF and mask mild deficiency.
Repeat testing when the patient is clinically stable.”
Stay updated with Hemostasis Today.
-
Nov 18, 2026, 15:11Vansh Yaduvanshi: Why Compatible Blood Groups Do Not Always Mean Compatible Blood
-
Nov 18, 2026, 14:49Estetrol-Based Contraception in PCOS and Its Effects on Coagulation – RPTH Journal
-
Nov 18, 2026, 14:41Factor V Deficiency: Diagnostic Challenges and the Role of Combined Factor V and VIII Deficiency
-
Nov 18, 2026, 14:29Maxime Dely: When Patient Encounters Become Life Lessons
-
Nov 18, 2026, 14:23Basanta Khatiwada: Advancing Haematology Through Research and Innovation at HAEMATOCON 2026
-
Nov 18, 2026, 14:13Alvin Katumba: Sickle Cell Disease Research Recognised With a 2026 ASH Abstract Achievement Award
-
Nov 18, 2026, 13:34Vincenzo De Angelis: Strengthening Plasma Management and Quality Control in Eastern Europe
-
Nov 18, 2026, 13:34Standardizing Bleeding Outcome Assessment in Hemophilia Clinical Trials – JTH
-
Nov 18, 2026, 13:34Nicolas Gendron: The Ecological Transition in Thrombosis and Haemostasis