


W. Alberto Sifuentes Giraldo: Temporal Structure of Cardiovascular and Thromboembolic Risk in AAV
W. Alberto Sifuentes Giraldo, Rheumatologist at Hospital Nuestra Señora de Sonsoles (Sacyl), shared a post on X about a recent article by Clemens Untersulzner et al., published in Rheumatology, adding:
“Temporal Structure of Cardiovascular and Thromboembolic Risk in AAV
Advances in treatment have transformed ANCA-associated vasculitis (AAV) from a fatal disease into a chronic condition. Consequently, cardiovascular disease and thromboembolism (CVD-TE) have become major comorbidities.
However, standard clinical practice has often overlooked this risk because traditional research reported it as a uniform average over time, masking its true temporal pattern.
Study Overview and Methodology
A nationwide matched cohort study by Lindberg et al. utilized Swedish registry data (2005–2020) to pinpoint when CVD-TE risk is highest:
- Cohort: 4,317 adults with AAV—3,159 with granulomatosis with polyangiitis (GPA) and 1,158 with microscopic polyangiitis (MPA).
- Control Groups: 21,582 general population controls (matched by age, sex, and county) and 25,568 first-degree siblings.
- Evaluated Outcomes: Myocardial infarction (MI), ischemic stroke, hemorrhagic stroke, deep vein thrombosis (DVT), pulmonary embolism (PE), CVD-TE-related death, and a composite of all six. High specificity for venous events was ensured by requiring an anticoagulant prescription within 30 days of diagnosis.
Key Findings
1. Comparable Risk Across Entities: After adjusting for age, sex, cardiovascular comorbidity, and kidney disease, the composite CVD-TE risk was elevated in both GPA and MPA, with no significant differences between the two diagnoses.
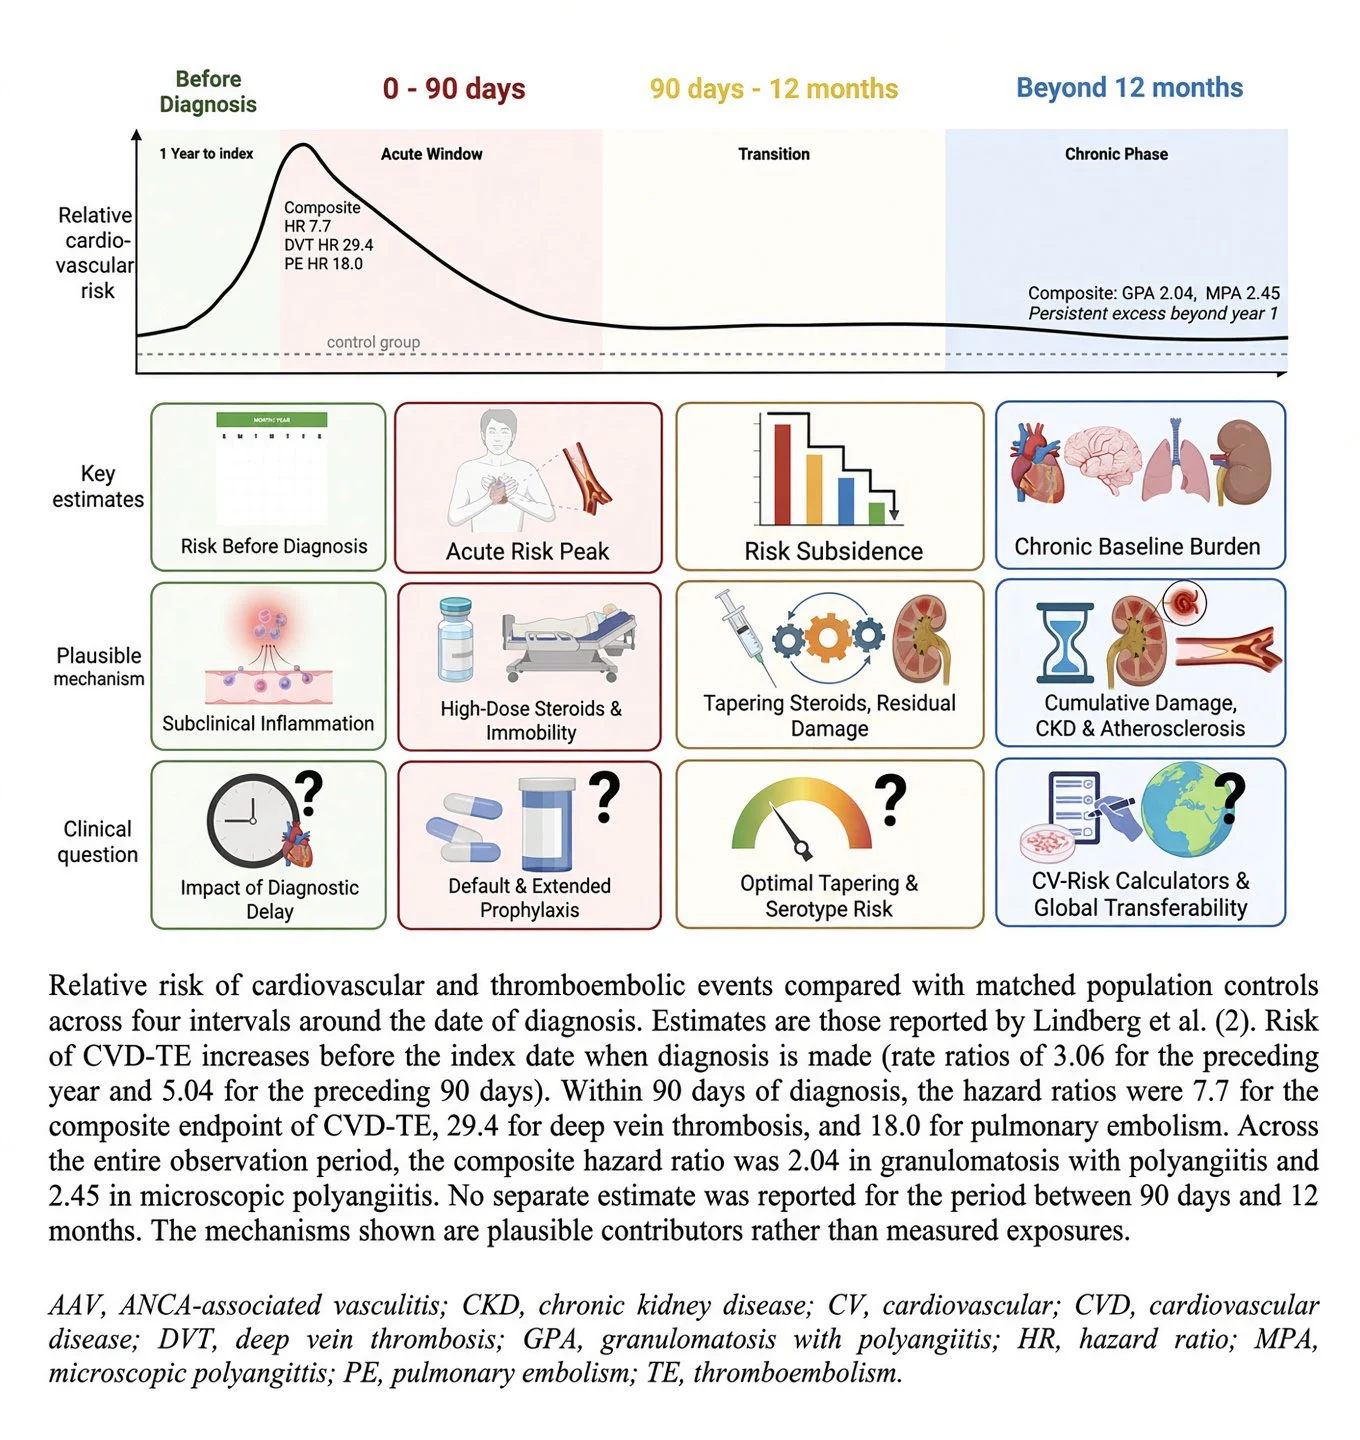
2. Extreme Early-Phase Risk Peak: The excess risk is heavily concentrated around the time of diagnosis:
- First 90 Days: Hazard ratios (HRs) peaked dramatically at 29.4 for DVT and 18.0 for PE, compared to 3.53 and 3.67 over full follow-up.
- Composite Risk: Reached an HR of 7.69 in the first three months. Stroke risk peaked at 3.39 (vs. 1.29 overall).
- Pre-Diagnosis Elevation: Risk was already elevated before formal diagnosis (rate ratio of 5.04 in the 90 days prior), supporting similar findings from Denmark.
- Long-Term Trajectory: Beyond the first year, cumulative hazard curves ran nearly parallel, maintaining a much lower but persistent risk.
3. Genetic Implications: Siblings of AAV patients showed no elevated CVD-TE risk compared to control siblings, and patients had a higher risk than their own siblings. This indicates that shared genetic susceptibility plays a minimal role in the observed CVD-TE excess.
Clinical and Methodological Takeaway
Reporting CVD-TE risk as a single overall hazard ratio is misleading because it assumes constant risk over time.
An overall average flattens the acute initial surge and fails to represent either the early hyper-acute phase or the lower chronic phase accurately.
Recognizing this early peak is essential for designing targeted, timely preventive strategies and early interventions.”
Title: Cardiovascular risk in ANCA-associated vasculitis: a plea for early intervention
Authors: Clemens Untersulzner, Andreas Kronbichler

Other posts featuring W. Alberto Sifuentes Giraldo on Hemostasis Today.
-
Oct 31, 2026, 01:11Alexander Misono: Venous Ultrasound and Early Intervention in Deep Vein Thrombosis
-
Oct 31, 2026, 00:54How Has Human Evolution Shaped the Delicate Balance between Bleeding and Clotting? – Seminars in Thrombosis and Hemostasis
-
Oct 30, 2026, 23:56Laboratory Testing and Interpretation in Modern Haemophilia Care – South African Haemophilia Foundation
-
Oct 30, 2026, 23:45Jesus Ardila Novoa: Why HbF Levels and Hydroxyurea Absorption Matter in Children With SCA
-
Oct 30, 2026, 23:41Ana Paula Tagliari: Presenting a First-in-Human Experience With Mechanical Thrombectomy at TCT 2026
-
Oct 30, 2026, 23:38Alok Khorana: The Role of Platelets in Immune Suppression in Primary Brain Tumors
-
Oct 30, 2026, 23:33Obi Light Ogbonnia: I Gifted Him My Isi Agu, and He Gifted My Family the Sun
-
Oct 30, 2026, 17:43Santagata Davide: Can Targeting Inflammation Help Prevent Thrombosis?
-
Oct 30, 2026, 17:38Patrick Ellsworth: Supporting Patients and Families Through Bleeding Disorders Awareness and Community Initiatives