


Thirunavukkarasu Angappan: Hemophilia Care Gap – What Plasma Fractionation Can and Cannot Fix
Thirunavukkarasu Angappan, Vice President of Operations and Manufacturing at PopVax, shared a post on LinkedIn:
“Hemophilia care gap: what plasma fractionation can and cannot fix
Hemophilia A and B are bleeding disorders caused by a shortage of factor VIII (FVIII) or factor IX (FIX).
Plasma-derived medicinal products (PDMP) are one route to treatment. Here is where the verified evidence stands.
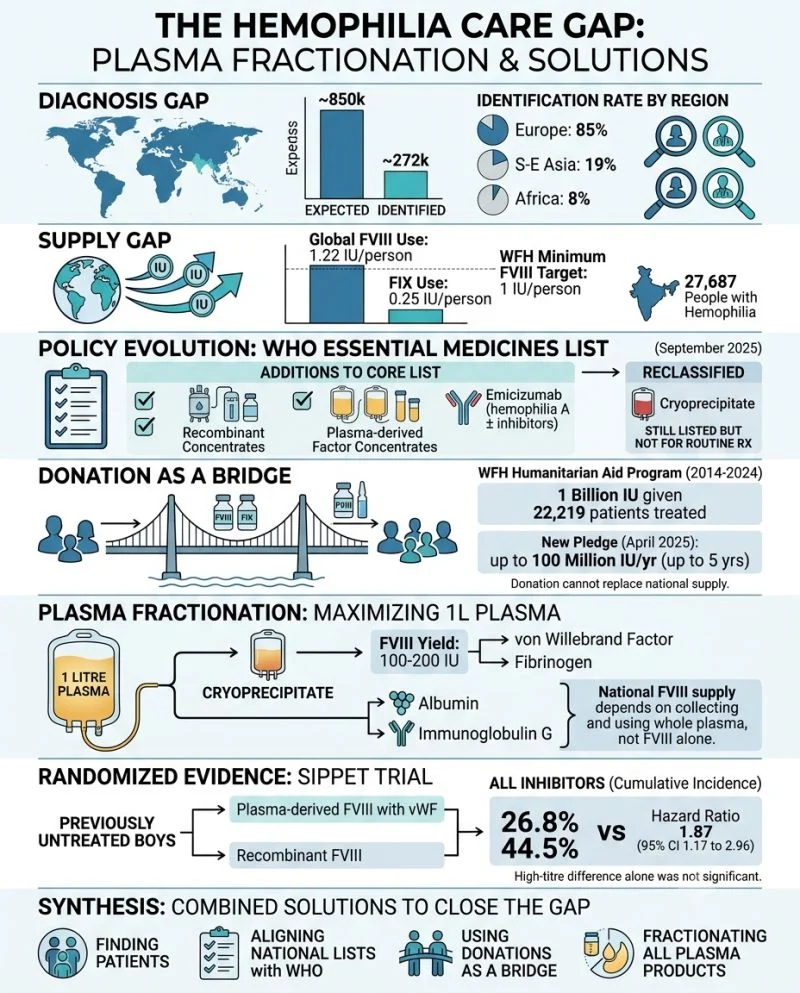
- The diagnosis gap: in the World Federation of Hemophilia (WFH) Annual Global Survey 2024 (135 of 152 member organisations responding), 271,918 people with hemophilia (224,353 with hemophilia A and 45,600 with hemophilia B) were identified, against about 850,000 expected, of whom about 289,000 would have severe disease. Identification was 85% in Europe, 19% in South-East Asia and 8% in Africa.
- The supply gap: global FVIII use was 1.22 international units (IU) per person and FIX 0.25 IU in 2024. The WFH sets 1 IU per person as the minimum FVIII target. India alone reported 27,687 people with hemophilia.
- Policy has moved: as reported in September 2025, the World Health Organization (WHO) Essential Medicines List added emicizumab for hemophilia A (with and without inhibitors), moved plasma-derived factor concentrates from the complementary to the core list, and added recombinant concentrates to the core list. Cryoprecipitate remains listed but is no longer recommended for routine hemophilia or von Willebrand disease treatment.
- A bridge, not a system: Sanofi and Sobi gave one billion IU of factor product to the WFH Humanitarian Aid Program in 2014 to 2024, treating 22,219 people with inherited bleeding disorders. In April 2025 they pledged up to 100 million IU a year for up to five years. Donation helps, but it is time-limited and cannot replace national supply.
- What fractionation offers: from one litre of plasma, Burnouf reported FVIII yields of about 100 to 200 IU (2007 figures), alongside albumin and immunoglobulin G. FVIII comes from cryoprecipitate, which also yields von Willebrand factor and fibrinogen. A national FVIII supply therefore depends on the plasma collected and on using the whole plasma, not FVIII alone.
- What the randomised evidence says about product type: in SIPPET (Survey of Inhibitors in Plasma-Product Exposed Toddlers), previously untreated boys given plasma-derived FVIII with von Willebrand factor developed fewer inhibitors overall than those given recombinant FVIII (26.8% versus 44.5%; hazard ratio 1.87, 95% confidence interval 1.17 to 2.96). The high-titre difference alone was not significant, so this is not a verdict on every product.
Synthesis: no single product closes the gap. The evidence points to a combination: finding patients, aligning national lists with WHO, using donations as a bridge, and, where plasma is available, planning fractionation around all plasma products.
Where is your country’s bigger barrier today: finding patients or securing factor supply?”
Other posts featuring Thirunavukkarasu Angappan on Hemostasis Today.
-
Nov 6, 2026, 10:29Luisa Weiss: How Platelets Drive Inflammation in Aortic Valve Disease
-
Nov 6, 2026, 10:18Dave Cartland: A Rare Case of Portal Vein Thrombosis After Moderna Vaccination
-
Nov 6, 2026, 10:10Iván Camilo Triana Avellaneda: Uncovering Distinct Clinical Phenotypes of DVT
-
Nov 6, 2026, 10:06Rafael Zubirán: Lp(a) – The Missing Link Between Inflammation and Thrombosis
-
Nov 6, 2026, 09:59Syeda Jazilah Faisal: Upstream Heparin in STEMI – Improving Coronary Reperfusion Before PCI
-
Nov 6, 2026, 09:51N. Mariana S. Vasquez: Understanding the 3 Main Types of Leg Ulcers
-
Nov 6, 2026, 08:22How Bleeding Disorders Affect Social Life and Well-Being? – EHC
-
Nov 6, 2026, 08:13Jared Rice: Why Neonatal Coagulation Cannot Be Interpreted Like Adult Coagulation
-
Nov 6, 2026, 08:07Matthew Smeds: Endovascular Salvage of Acute IVC Thrombosis After Liver Transplantation