

Anis Mahjoubi: MRI Findings of Krukenberg Tumors
Anis Mahjoubi, MR Clinical Application Specialist, shared a post on LinkedIn:
“MRI signs of Krukenberg tumors (ovarian metastases with signet ring cells, usually from gastric or colorectal primaries):
MRI features are often characteristic but not fully specific. Key findings include:
Morphologic features :
Bilateral in approximately 80 percent of cases (highly suggestive when present).
Well defined or sharp margins.
Oval or rounded configuration often preserved (even when large).
Predominantly solid, mixed solid cystic, or (less often) mostly cystic.
Smooth external contour; lobulated appearance common.
Ascites frequently associated.
Signal intensity characteristics :
Solid components (due to dense stromal or fibrous reaction):
T1 weighted: Hypointense to intermediate.
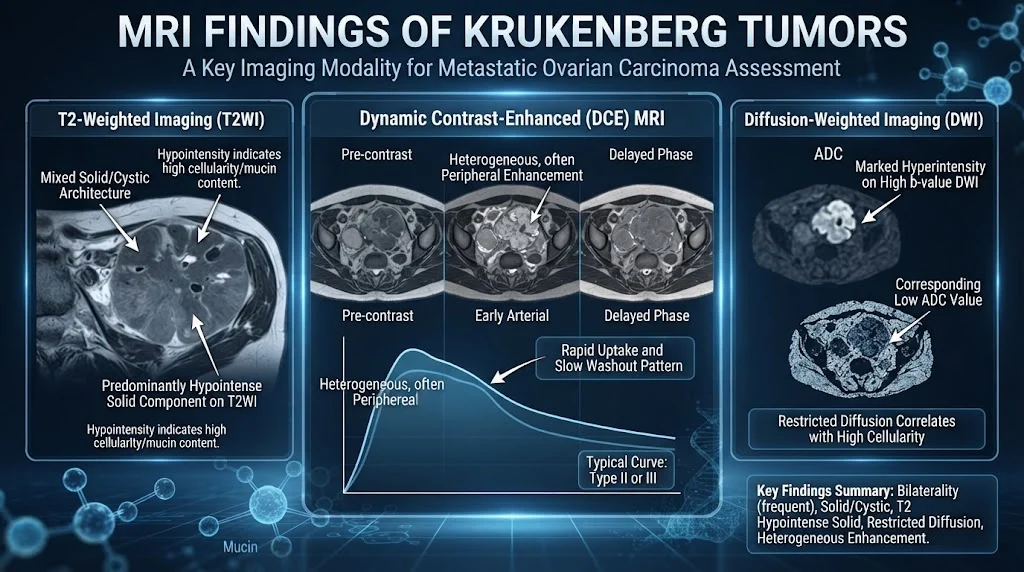
T2 weighted: Characteristically hypointense (low signal) , this is one of the most helpful clues, especially when bilateral, with sharp margins and oval shape. The hypointensity corresponds to dense collagenous stroma.
Variable overall signal if edema or mucin is present.
Cystic or mucinous components:
T2 weighted: Hyperintense (high signal from mucin or fluid).
T1 weighted: Variable (can be hyperintense if thick mucin or proteinaceous or hemorrhagic content).
Non enhancing.
Contrast enhancement and diffusion
Post or gadolinium (T1 C plus): Solid components and walls of intratumoral cysts show strong or vivid heterogeneous enhancement.
Dynamic curves often show rapid early uptake followed by washout (type 3 curve).
DWI or ADC: Restricted diffusion in the solid components (high signal on high b value DWI, low ADC values).
Additional helpful signs
Uniform cystic locules or ‘moth eaten’ cystic areas within solid tissue.
Hypointense solid peripheral or randomly distributed components on T2.
Look for the primary tumor (gastric wall thickening, colonic mass, etc.) and other metastases.
Differential considerations on MRI :
Primary ovarian carcinoma (especially mucinous).
Fibroma or fibrothecoma (very T2 hypointense but usually unilateral and less enhancing).
Other ovarian metastases or lymphoma.
Note: MRI alone cannot definitively distinguish Krukenberg tumors from primary ovarian malignancies. Clinical context (known primary, younger age, bilaterality) and histology remain essential. Always correlate with CT or PET for staging and search for the primary site.”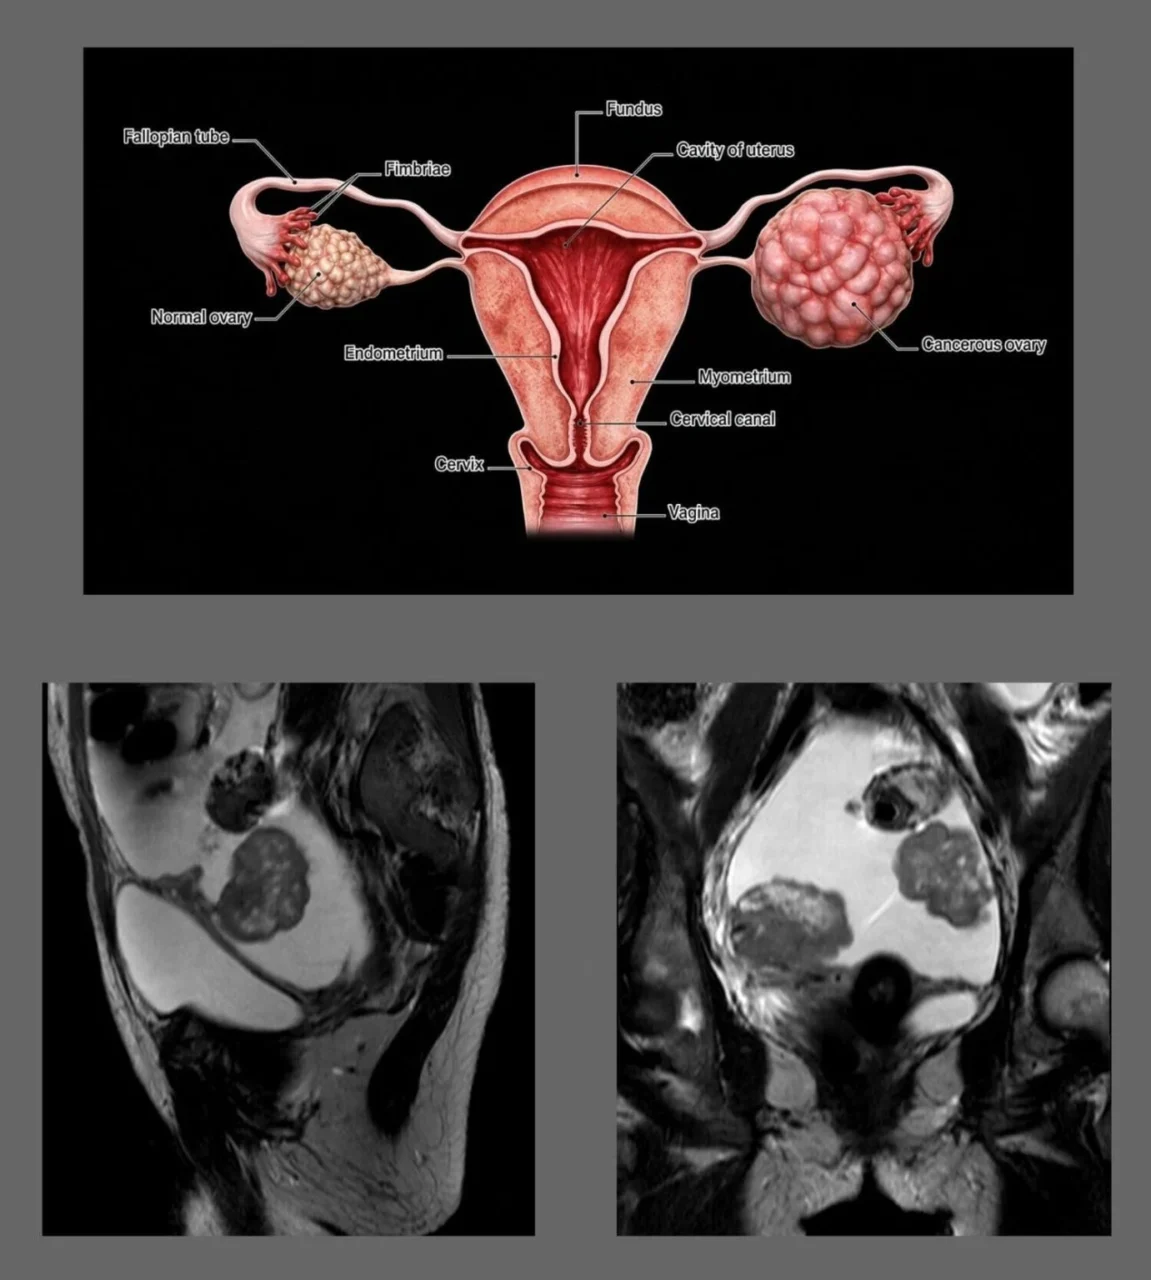
Stay updated with Hemostasis Today.
-
Nov 11, 2026, 13:01Reza Shojaei: FDA Approval Marks Milestone for Factor XIa-Targeted Therapy
-
Nov 11, 2026, 11:35Paulus Kirchhof: Oral Anticoagulation in Atrial Fibrillation After Intracranial Hemorrhage
-
Nov 11, 2026, 11:28Arturo Cesaro: Lp(a) Lowered by 78% but Cardiovascular Outcomes Remain Unchanged
-
Nov 11, 2026, 09:40Diego Martin Rabasedas: Celebrating National Voluntary Blood Donor Day in Argentina
-
Nov 11, 2026, 09:32Nathan Connell: Can a Thrombophilic Factor VIII Variant Inform Future Hemophilia A Therapies?
-
Nov 11, 2026, 09:24Amer Zeidan: Highlights from the 2026 New England Hematologic Disease Symposium
-
Nov 10, 2026, 16:28Can the VWF to ADAMTS-13 Ratio Predict Mortality in Sepsis-Induced Coagulopathy? – RPTH Journal
-
Nov 10, 2026, 16:28Ruth Willems: PhD Defence at Maastricht University on Thrombosis and Bleeding in HPB Disease
-
Nov 10, 2026, 16:09Edward Lee Carter: Factor XIa Inhibition Enters Clinical Practice