


Ifeanyichukwu Ifechidere: TTP and ADAMTS-13 – The Enzyme Deficiency That Can Kill in 24 Hours
Ifeanyichukwu Ifechidere, Specialist Biomedical Scientist at Sheffield Teaching Hospitals NHS Foundation Trust, shared a post on LinkedIn:
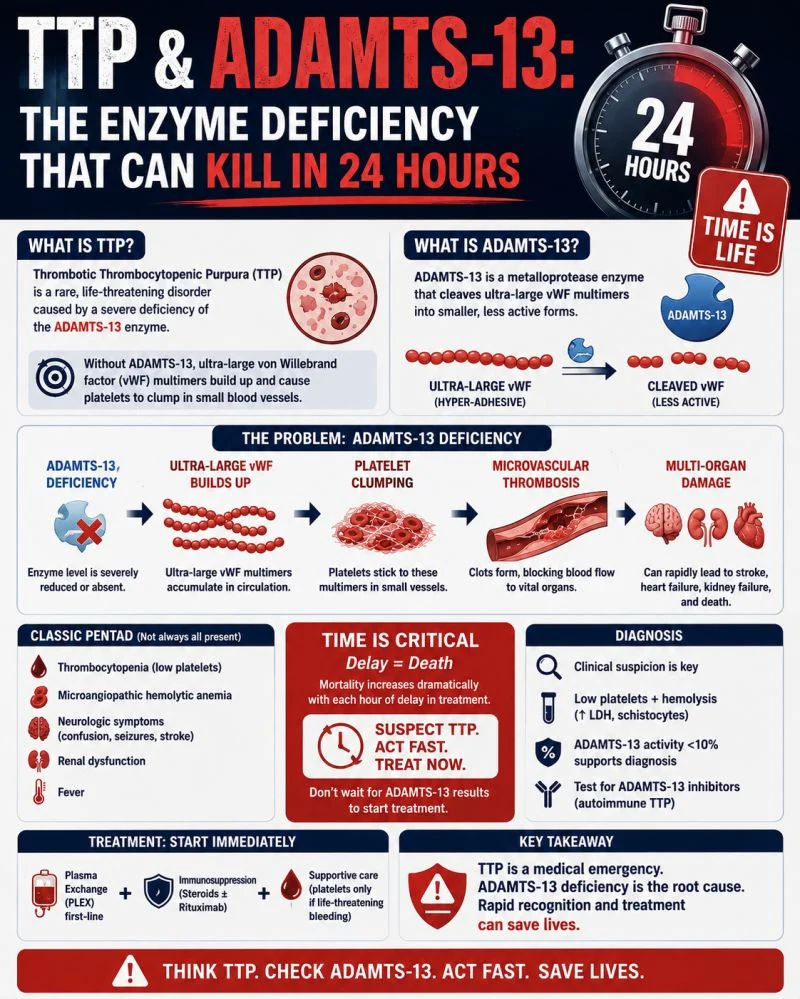
“TTP and ADAMTS-13: The Enzyme Deficiency That Can Kill in 24 Hours
If you take one haematological emergency seriously enough to recognise at 2am, make it this one.
Thrombotic Thrombocytopenic Purpura (TTP) is rare – but untreated, it’s fatal in over 90% of cases. Treated promptly, survival flips to over 80%.
That gap is entirely about recognition speed.
What’s actually happening
Normally, ultra-large von Willebrand factor (ULVWF) multimers released from endothelial cells are cleaved down to smaller, less ‘sticky’ forms by an enzyme called ADAMTS-13.
In TTP, ADAMTS-13 activity is severely deficient (typically less than 10%) – either through:
- Autoantibody inhibition (acquired/immune TTP – the majority of cases)
- Inherited mutation (congenital TTP / Upshaw-Schülman syndrome – rare)
Without ADAMTS-13 doing its job, ULVWF multimers stay huge and hyperactive.
They spontaneously bind platelets, triggering widespread microthrombi in small vessels – consuming platelets and shearing red cells as they pass through.
The clinical picture (classic pentad – rarely all present)
- Microangiopathic haemolytic anaemia (schistocytes on film )
- Thrombocytopenia
- Neurological symptoms
- Renal impairment
- Fever
In practice, you’ll usually see the first two plus organ involvement – waiting for all five delays diagnosis and costs lives.
The lab clues that should raise suspicion
- Low platelets plus anaemia plus schistocytes on blood film
- Normal PT/APTT/fibrinogen – this is what separates TTP from DIC
- Elevated LDH and bilirubin (haemolysis markers)
- Negative direct Coombs test (rules out immune haemolytic anaemia)
Confirmatory test: ADAMTS-13 activity assay — severe deficiency (less than 10%) confirms diagnosis. Anti-ADAMTS-13 antibodies confirm the acquired form.
Why this matters so much in the lab: TTP is a clinical diagnosis first.
Waiting for ADAMTS-13 results (which can take days) before starting treatment is a fatal delay.
The PLASMIC score is often used at the bedside to estimate pre-test probability while results are pending.
Management essentials
- Plasma exchange (PEX) – the cornerstone, removes autoantibodies and ULVWF, replenishes ADAMTS-13
- Corticosteroids – immunosuppression for the autoimmune process
- Caplacizumab – anti-VWF nanobody, blocks platelet binding while PEX takes effect
- Platelet transfusion is generally AVOIDED unless life-threatening bleeding — it can fuel further microthrombosis
The lab’s role: A same-day film review flagging schistocytes, alongside a normal coagulation screen, can be the trigger that gets PEX started before ADAMTS-13 results are back.
That turnaround is where biomedical scientists directly save lives.”
Other posts featuring Ifeanyichukwu Ifechidere on Hemostasis Today.
-
Sep 21, 2026, 11:03Shaurav Bhattacharyya: Honoring the 2026 Lasker Award Winners
-
Sep 21, 2026, 10:41Jamshid Ullah: Recognizing Blood Disorders Through Laboratory Findings
-
Sep 21, 2026, 10:18Mana Alshehri: A New Step Toward Hemophilia B Gene Therapy in Adolescents
-
Sep 21, 2026, 09:52Afreenish Tasadaq: Contributing to Awareness about Bleeding Disorders
-
Sep 21, 2026, 08:49Andrea Bridges: When Support Becomes a Commitment to Give Back
-
Sep 21, 2026, 08:21Managing Thrombotic Risk in Pregnancy
-
Sep 21, 2026, 04:06Allison Lewin: How Gender Shapes the Way We Receive Medical Care
-
Sep 21, 2026, 03:49Jessica Lee: Walking Together for a Stronger Bleeding Disorders Community
-
Sep 21, 2026, 03:36Syed Asif Ali Shah: From Pakistan to Australia – A Clinical Haematology Milestone