


Mili Jain: Key Causes and Diagnosis of Macrocytic Anemia
Mili Jain, Assistant Professor at Pacific Medical College and Hospital, shared a post on LinkedIn:
” ‘Macrocytic Anemia’
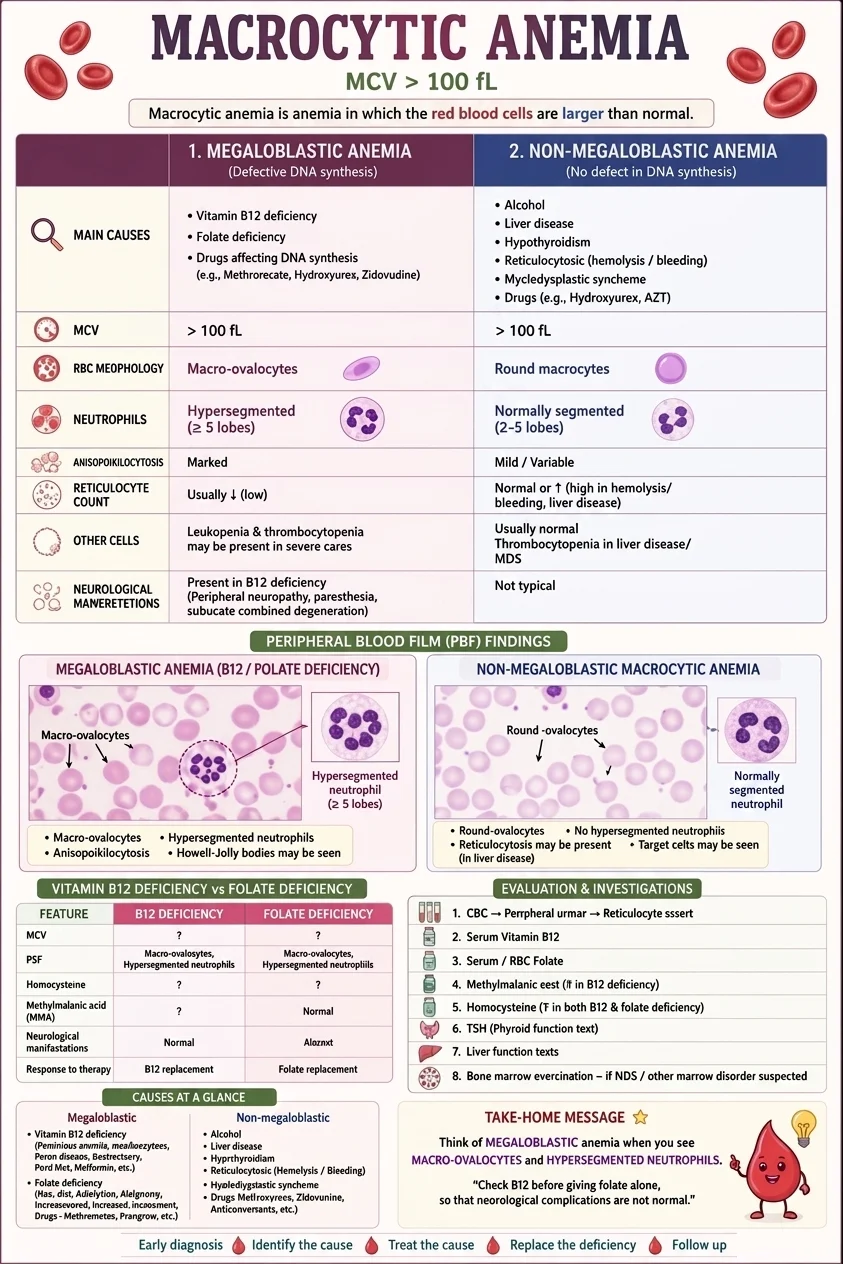
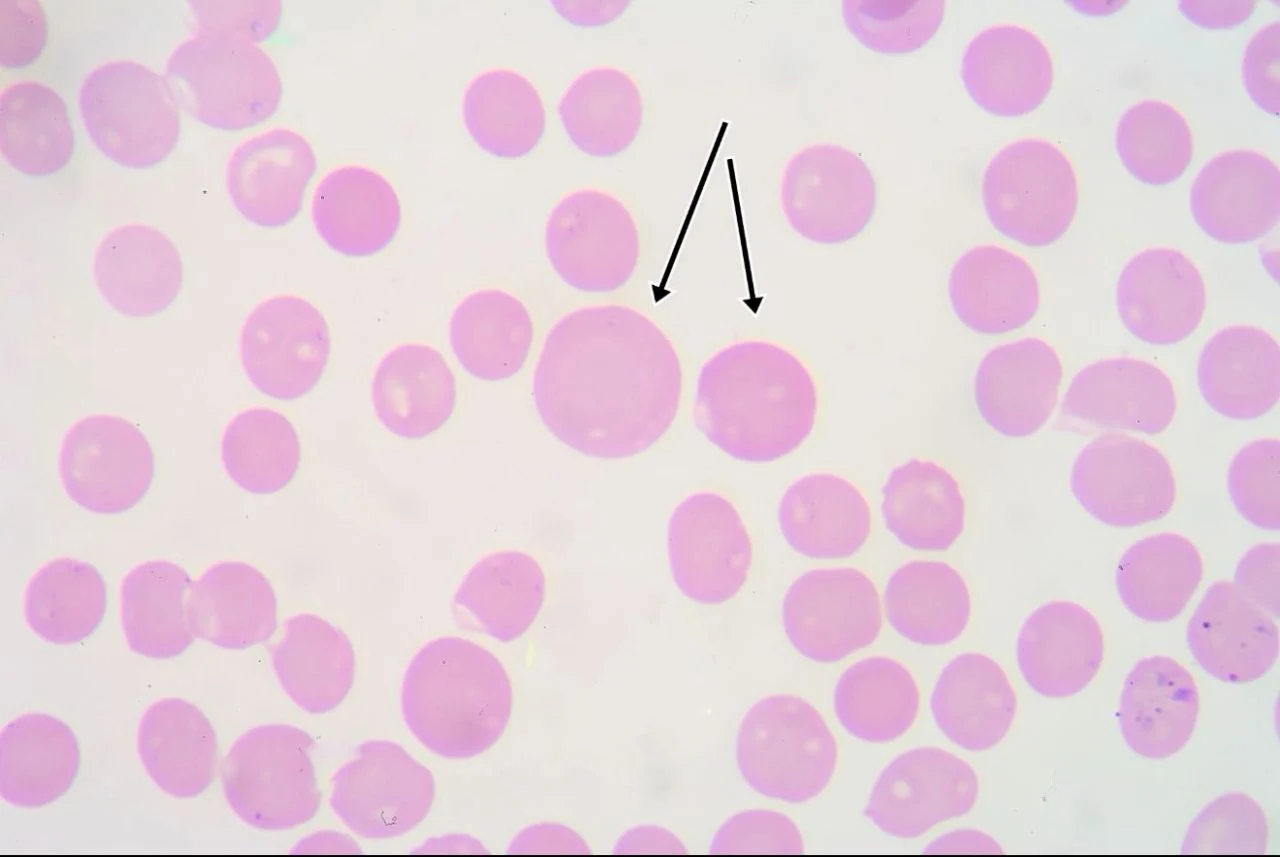
Macrocytic anemia is anemia in which the red blood cells are larger than normal, typically with MCV greater than 100 fL.
Important causes
1. Vitamin B12 deficiency:
- Pernicious anemia
- Malabsorption
- Gastrectomy/bariatric surgery
- Ileal disease
- Poor dietary intake
- Certain drugs, e.g. metformin
2. Folate deficiency:
- Poor diet/alcoholism
- Pregnancy
- Malabsorption
- Increased requirement
- Methotrexate and other antifolate drugs
3. Other causes:
- Alcohol
- Liver disease
- Hypothyroidism
- Myelodysplastic syndrome
- Reticulocytosis after hemolysis/bleeding
- Drugs such as hydroxyurea, zidovudine, and some anticonvulsants
Main Classification:
- ‘Megaloblastic’:– Vitamin B12 deficiency, folate deficiency, drugs affecting DNA synthesis
Key Clues: increased MCV
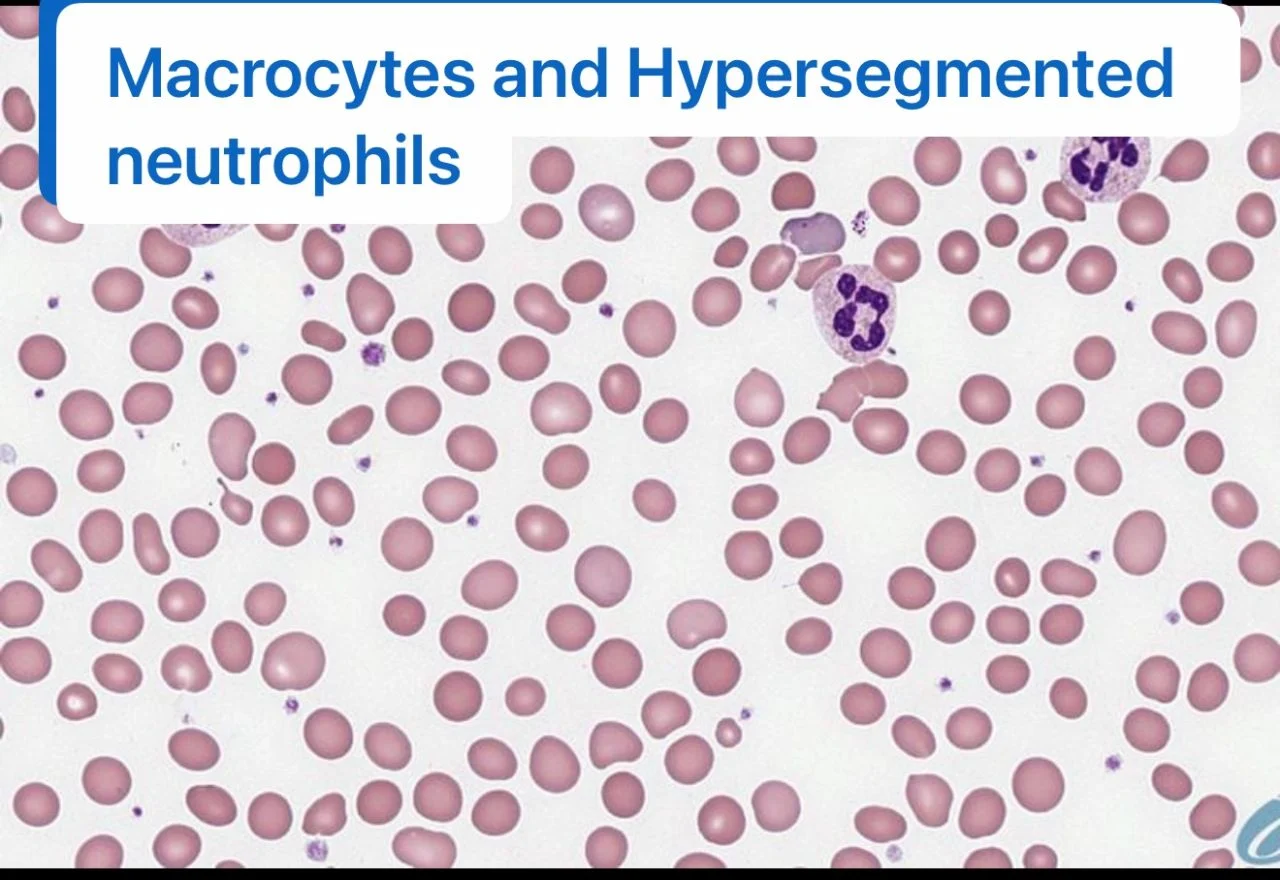
* Macro-ovalocytes
* Hypersegmented neutrophils, Sometimes leukopenia and thrombocytopenia
- ‘Non-megaloblastic’:– Alcohol, liver disease, hypothyroidism, reticulocytosis
Key Clues: No typical megaloblastic morphology.
Important PBF findings in Macrocytic Anemia
‘Megaloblastic anemia’ — classic PBF findings:
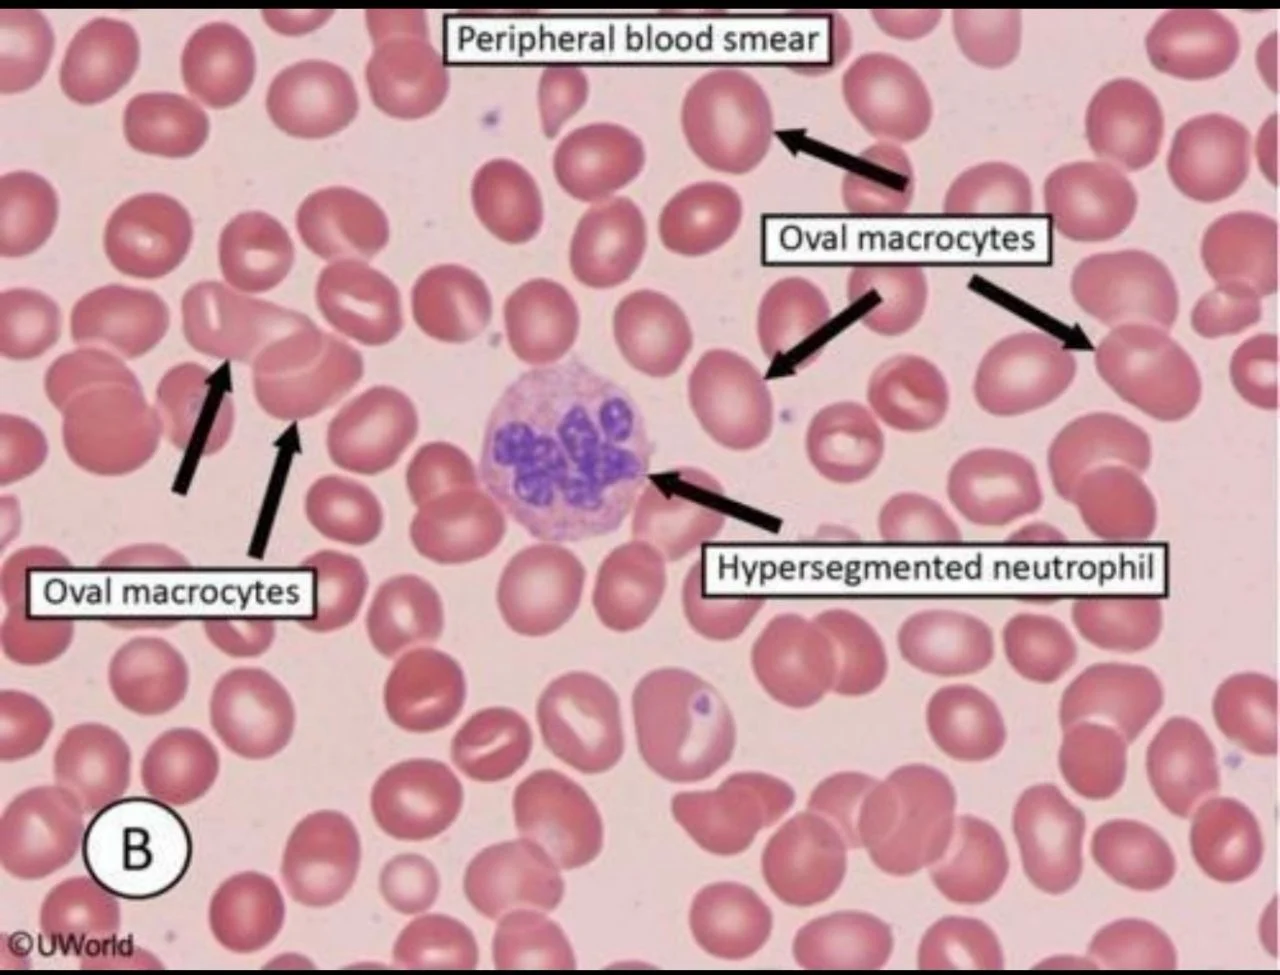
- Macro-ovalocytes — most characteristic
- Hypersegmented neutrophils — 5 or more lobes in a significant proportion of neutrophils, and 1% 6 lobes neutrphil.
- Anisocytosis and poikilocytosis
- Oval macrocytes
- Howell–Jolly bodies, basophilic stippling and may be seen
- Pancytopenia may occur in severe cases
Useful investigations
CBC, followed by a peripheral blood smear, followed by a reticulocyte count, followed by vitamin B12 and folate testing.
‘Non-megaloblastic macrocytosis’:
- Round macrocytes/macrocytic RBCs
- Reticulocytosis may be present
- Target cells may suggest liver disease
- No hypersegmented neutrophils.
Depending on the findings:
- Serum B12
- Serum/RBC folate
- Methylmalonic acid (MMA) – increased in B12 deficiency
- Homocysteine – increased in both B12 and folate deficiency
- TSH
- Liver function tests
- LDH, bilirubin, haptoglobin if hemolysis suspected
- Consider bone marrow examination if MDS or another marrow disorder is suspected.
B12 vs Folate — high-yield distinction
Finding:
B12 deficiency:
- MCV , Hypersegmented neutrophils- Present ,increased Homocysteine, increased Methylmalonic acid, Neurological manifestations- Common
Folate deficiency:
- increased MCV, Hypersegmented neutrophils – Present, increased Homocysteine , Methylmalonic acid- Normal, Neurological manifestations- Usually absent
Macro-ovalocytes and hypersegmented neutrophils: think B12/folate deficiency (megaloblastic anemia).
Important: If B12 deficiency is possible, check B12 before treating with folate alone, because folate can correct the anemia while allowing neurological damage from B12 deficiency to progress.”
Stay updated with Hemostasis Today.
-
Oct 16, 2026, 13:05Maha Othman: Queen’s Health Sciences Advances CAT Risk Models and Pediatric ISTH-BAT Cut-Offs
-
Oct 16, 2026, 13:03Thrombosis Awareness Must Lead to Timely Action – Roche
-
Oct 16, 2026, 12:49Wolfgang Miesbach: 5-Year CBDR Data Confirms Emicizumab Safety and Efficacy in Hemophilia A
-
Oct 16, 2026, 12:40Edward Lee Carter: How Factor XI Inhibition Could Transform Anticoagulation Therapy
-
Oct 16, 2026, 12:40Marc Carrier: Looking Ahead to ISTH 2027 in Vancouver
-
Oct 16, 2026, 12:30Bob Lempke: How One Blood Donation Can Save Up to Three Lives
-
Oct 16, 2026, 12:30Why VWF Therapies Belong on the EU Critical Medicines List – EHC
-
Oct 16, 2026, 12:17Exploring Endothelial Cells, Genetic Fate Mapping, and Revascularization – ISTH
-
Oct 16, 2026, 10:07Habib Bennaceur: Building a Stronger Care Pathway for Sickle Cell Disease in India