


Nicolas Federico Renna: When Biomarkers Fall but Cardiovascular Events Do Not
Nicolas Federico Renna, Fellow of the International Society of Hypertension, Adjunct Professor of Medicine at the National University of Cuyo, and Head of the Hypertension Unit at Hospital Español de Mendoza, shared a post on LinkedIn։
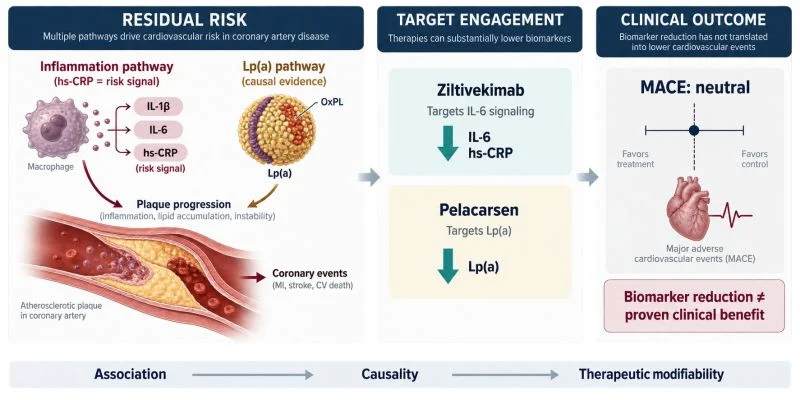
“When biomarkers fall—but cardiovascular events do not
Two major cardiovascular outcome trials have recently delivered disappointing results.
In ZEUS, ziltivekimab achieved the expected inhibition of the IL-6 pathway and reduced hs-CRP, yet it did not reduce 3-point MACE in patients with ASCVD, chronic kidney disease, and systemic inflammation (HR 0.99; 95% CI 0.88–1.11).
Now, the topline results of Lp(a)HORIZON indicate that pelacarsen substantially lowered Lp(a), but did not significantly reduce 4-point MACE in the overall population of 8,323 patients with established cardiovascular disease.
These trials evaluated different biological pathways and should not be considered equivalent.
However, together they highlight a fundamental distinction:
Risk association, causal involvement, and therapeutic modifiability are related—but not interchangeable—levels of evidence.
Observational studies such as POSEIDON have underscored the prognostic significance of inflammatory burden in heart failure.
However, hs-CRP primarily identifies an inflammatory phenotype; it does not establish that CRP itself is causal or that inhibition of one specific upstream pathway will necessarily modify that risk.
Similarly, in our GAELp(a) registry, elevated Lp(a) was highly prevalent and independently associated with a greater burden of cardiovascular disease, including among patients with treated hypertension and irrespective of blood pressure control. These findings reinforce the clinical relevance of Lp(a) as a marker of residual cardiovascular risk.
But Lp(a) requires an important distinction: unlike CRP, it is supported by strong genetic and mechanistic evidence as a causal cardiovascular risk factor.
Therefore, the negative HORIZON result should neither be dismissed as merely the failure of one drug nor prematurely interpreted as the end of the Lp(a) hypothesis.
The full data must clarify:
- Was the absolute and sustained Lp(a) reduction sufficient?
- Was treatment initiated too late in the course of established atherosclerosis?
- Were patients with the highest Lp(a) levels more likely to benefit?
- Did individual MACE components respond differently?
- Would deeper and more durable reductions with siRNA-based therapies produce another result?
A biomarker may identify patients at risk without being the direct cause of that risk. And even when it is causally involved, reducing it pharmacologically may not immediately reverse decades of accumulated vascular exposure.
Association identifies risk. Causality identifies a mechanism. Randomized trials determine whether that mechanism is therapeutically modifiable.
Negative trials do not end scientific hypotheses—but they force us to define them more precisely.”
Stay updated with Hemostasis Today.
-
Oct 17, 2026, 04:07Weihao Li: Global HEPATIC Registry Findings on Post-Transplant Arterial Thrombosis
-
Oct 17, 2026, 03:56Ghaith Abu-Zeinah: ASH Publishes 2026 Guidelines for Myelofibrosis Management in Blood Advances
-
Oct 17, 2026, 03:48Tristan Siokos: Why Vascular Occlusion Is More Than Just Clots – Breakdown of the 8 Pathways
-
Oct 17, 2026, 02:36Archil Jaliashvili: Oxygen Transport in Capillaries
-
Oct 17, 2026, 02:35Carly Newton: Understanding Access to Red Blood Cell Exchange for People Living With SCD
-
Oct 17, 2026, 02:34Raising Awareness of Blood Clots During and After Pregnancy – Thrombosis UK
-
Oct 17, 2026, 02:33Alaa Salamat: Our Research Accepted for Publication at ASH 2026
-
Oct 17, 2026, 02:32Mohammed Al Sharif: Discussing Factor XIII Testing and Its Clinical Significance
-
Oct 17, 2026, 02:31Joanna Popiolek-Kalisz: Talking about Novel Pharmacotherapy for Hypertension at CV Prevention and Intervention