


Rishdha Roshad: What Happens to the Brain During Cardiopulmonary Bypass?
Rishdha Roshad, BS Cardiac Perfusion Technology Student at Dow University of Health Sciences, shared a post on LinkedIn:
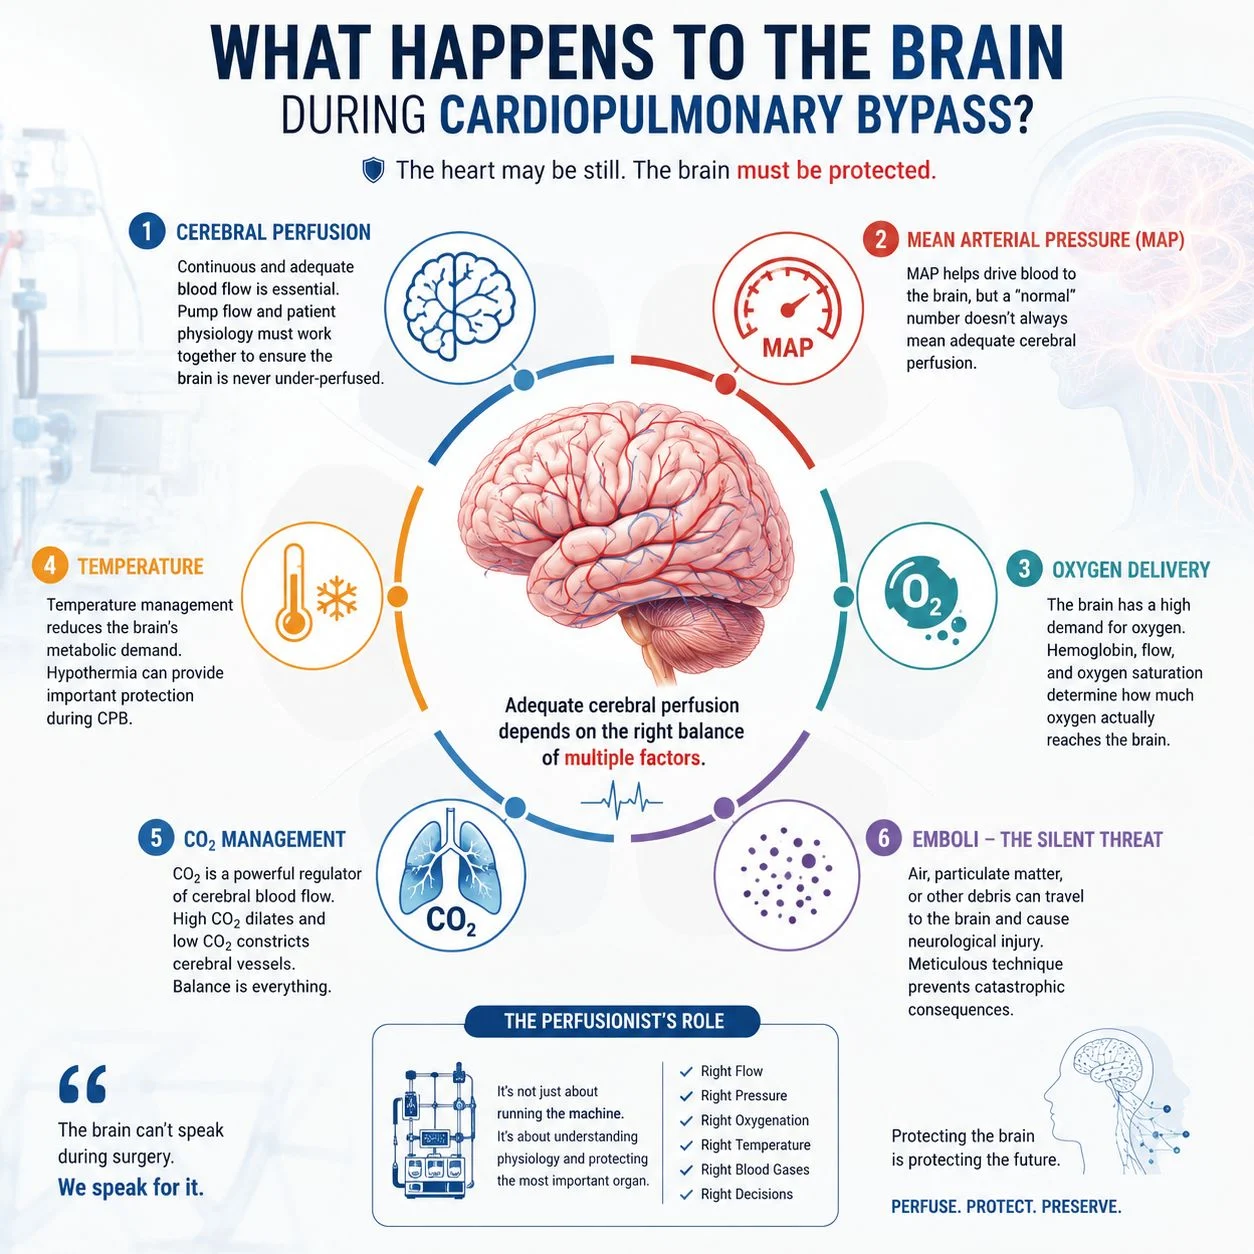
“What Happens to the Brain During Cardiopulmonary Bypass?
During cardiac surgery, the heart may be stopped — but the brain cannot afford to stop.
This is one of the reasons cerebral protection is such an important part of cardiopulmonary bypass.
While the perfusionist manages the CPB circuit, several factors can influence cerebral perfusion:
1. Cerebral Blood Flow
The brain requires continuous and adequate blood flow. Pump flow and arterial pressure must be considered in relation to the patient’s physiology — not simply as isolated numbers.
2. MAP — Pressure Matters, But So Does Perfusion
Maintaining an appropriate mean arterial pressure helps support cerebral perfusion, but a ‘normal-looking’ MAP does not automatically guarantee adequate oxygen delivery to the brain.
3. Oxygen Delivery
The brain is highly dependent on oxygen.
Hemoglobin, arterial oxygen saturation, cardiac output/pump flow and oxygen content all contribute to the oxygen available to cerebral tissue.
4. Temperature
Temperature management during CPB changes metabolic demand. Hypothermia can reduce cerebral metabolic rate and is therefore an important component of cerebral protection in appropriate surgical settings.
5. CO₂ — A Small Change, A Big Effect
CO₂ has a major influence on cerebral vascular tone. Changes in PaCO₂ can alter cerebral blood flow, making blood-gas management an important part of perfusion practice.
6. Emboli — The Silent Threat
Air, particulate matter, or other embolic material can reach the cerebral circulation and contribute to neurological injury. This is why meticulous circuit management, de-airing and blood conservation practices matter.
And this is what makes perfusion fascinating to me:
The perfusionist isn’t simply watching the pump.
They are constantly asking:
- Is the brain receiving enough blood?
- Is oxygen delivery adequate?
- Is metabolic demand being controlled?
- Are pressure, flow and blood gases appropriate for this patient?
The more I learn about CPB, the more I realize that cerebral protection is not one setting or one number.
It is the result of understanding how multiple physiological variables interact — and making thoughtful decisions throughout bypass.
The heart may be temporarily supported by a machine.
The brain still depends on a perfusionist who understands what those numbers mean.
Learning perfusion means learning to protect what cannot be seen.”
Stay updated with Hemostasis Today.
-
Nov 15, 2026, 23:44Pablo César Spada: Prevention of Venous Thromboembolism After Total Hip or Knee Replacement
-
Nov 15, 2026, 23:30Eshal Amir: Factor XI Inhibitors in AFib and Aortic Mortality Trends
-
Nov 15, 2026, 23:19Hamza Bashir: Adding Endovascular Therapy to Anticoagulation Cuts Moderate-to-Severe PTS in Half
-
Nov 15, 2026, 23:06Lanre Tunji-Ajayi: 2 Days of Deliberative Dialogue Hosted by the Network of Rare Blood Disorder Organizations
-
Nov 15, 2026, 23:00Fanny Delettre: Looking Back at Volunteer Blood Donor Friends Day
-
Nov 15, 2026, 20:56Victoria Adedoyin Adisa-Thomas: What I Learned About SCD During My Genetic Counselling Rotation
-
Nov 15, 2026, 20:55Martin Holst Lange: One Step Closer to a Potential New Treatment for Sickle Cell Disease
-
Nov 15, 2026, 20:53Bontha Babu: Health-Related Quality of Life Among Adults with Sickle Cell Disease in India
-
Nov 15, 2026, 20:52Miguel Ángel Herrera Rojas: A First-Line ITP Approach Presented at ASH in 2013 Now Reflected in the 2026 Guidelines