


What Clinicians Should Know About ITP – Insights from Samwel Mikaye
Samwel Mikaye, CEO of SaMik Medical Center, posted on LinkedIn:
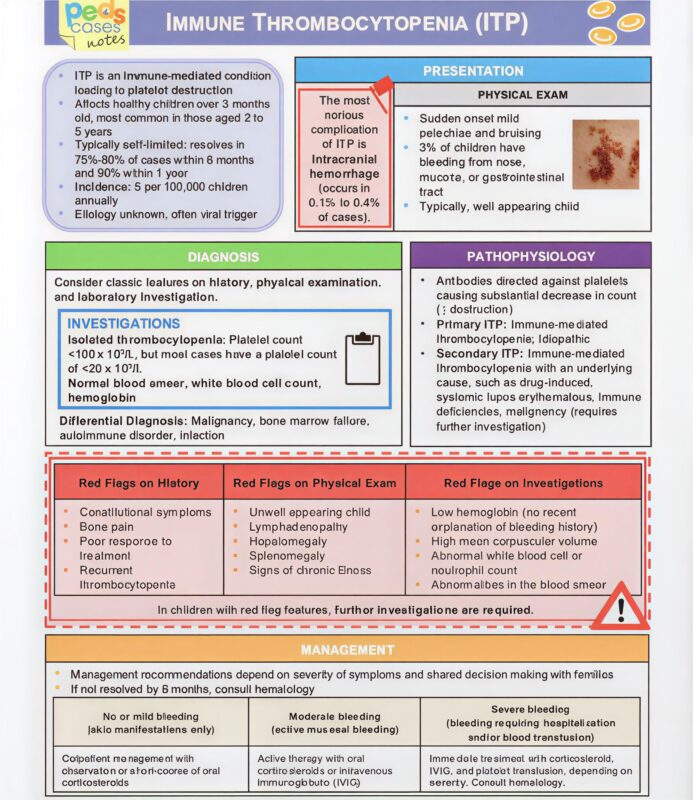
”IMMUNE THROMBOCYTOPENIC PURPURA (ITP)
Definition
Immune Thrombocytopenic Purpura (ITP) is an autoimmune disorder characterized by:
• Isolated thrombocytopenia (platelets <100,000/µL)
• Caused by autoantibodies against platelet surface antigens → accelerated destruction in the spleen and reduced platelet production in the bone marrow.
Classification
1. Primary ITP
• Idiopathic (no identifiable cause).
2. Secondary ITP
• Associated with underlying conditions:
• HIV, HCV, EBV
• Autoimmune diseases (e.g., SLE)
• Drugs (heparin, quinine, sulfa drugs)
• Vaccination (rare)
Epidemiology
• Children: usually acute, post-viral, self-limiting.
• Adults: usually chronic, more common in women <40 years.
Clinical Features
• Often asymptomatic except for bleeding.
• Mucocutaneous bleeding:
• Petechiae, purpura, ecchymoses
• Epistaxis, bleeding gums, menorrhagia
• No splenomegaly (splenic enlargement suggests another diagnosis).
Key: Patient appears well despite very low platelet count.
Diagnosis
Diagnosis of exclusion.
• CBC: isolated thrombocytopenia; other cell lines normal.
• Peripheral smear: normal red/white cells, reduced platelets.
• Coagulation profile (PT/PTT): normal
If atypical features (anemia, leukopenia, splenomegaly), consider other causes (TTP, leukemia, DIC).
Tests to rule out secondary causes:
• HIV, HCV testing
• ANA (if autoimmune disease suspected)
Management
Children (acute ITP)
• Observation if mild bleeding and platelets >30,000/µL.
• If treatment needed (significant bleeding):
• Corticosteroids (Prednisone)
• OR IVIG (for rapid platelet rise)
• Anti-D immunoglobulin (if Rh+ and not splenectomized)
Adults (chronic ITP / symptomatic)
First-line treatment:
• Corticosteroids: Prednisone or Dexamethasone pulse
• OR IVIG (if severe bleeding or need rapid rise—e.g., surgery)
Second-line options (if refractory or steroid-dependent):
• Thrombopoietin receptor agonists (TPO-RAs):
• Romiplostim, Eltrombopag
• Rituximab (anti-CD20 antibody)
• Splenectomy (curative in ~60–70% cases)
Platelet transfusion only for life-threatening bleeding; not routinely effective since autoantibodies destroy transfused platelets.
Treatment Thresholds (Adults)
• Platelets ≥ 30,000/µL + no bleeding → observe
• Platelets < 30,000/µL or active bleeding → treat
Prognosis
• Children: 80% recover spontaneously.
• Adults: chronic in ~60–70%, but manageable.”
Stay informed with Hemostasis Today.
-
Nov 20, 2026, 00:02Andres Zuleta: Evaluating the RISE UP Trial Results on Mitapivat for Sickle Cell Disease
-
Nov 19, 2026, 23:57Greta Hametner: Preventing Maternal Cardiac Complications Through Preconception Iron and Thyroid Screening
-
Nov 19, 2026, 23:49Cyrus Shariat: Why Waiting for Lab Results Can Be Fatal in HIT
-
Nov 19, 2026, 22:24Erik Nelson: Low Iron Can Raise A1c without Changing Blood Sugar
-
Nov 19, 2026, 22:23Erwin Loh: Daily Iron Supplementation Reduces Iron-Deficiency Anaemia in Children and Adolescents
-
Nov 19, 2026, 22:22Afifah Sardar: Why Can a Simple Painkiller like Aspirin Make You Bleed More?
-
Nov 19, 2026, 22:16Jonathan Penm: Perioperative Anticoagulation Management and Antithrombotic Stewardship Across 31 Countries
-
Nov 19, 2026, 22:15Salomao V.: Innovation in Hemophilia A Is Also About How Patients Receive Their Treatment
-
Nov 19, 2026, 16:27263 PolyU Students and Staff Unite to Donate Blood – Hong Kong Red Cross Blood Transfusion Service