


Nthabiseng Bapela: Interpreting INR in Patients on Warfarin – A Practical Clinical Framework
Nthabiseng Bapela, Healthcare Intelligence System Specialist at MerithRX, shared a post on LinkedIn:
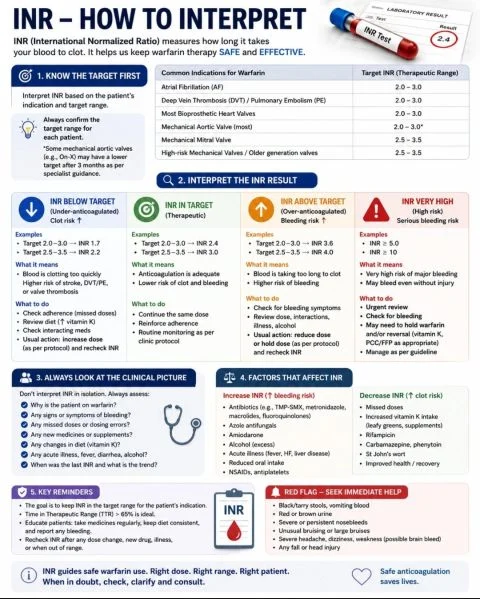
“Interpreting INR in patients on warfarin: a practical clinical framework
The International Normalized Ratio (INR) is central to monitoring warfarin therapy, but it should never be interpreted in isolation. An INR result only becomes meaningful when considered alongside the patient’s indication for anticoagulation, target range, bleeding risk, and current clinical context.
A structured approach to INR interpretation
1. Confirm the indication for warfarin
Start by identifying why the patient is anticoagulated. Common indications include:
- Atrial fibrillation
- DVT and PE
- Mechanical prosthetic heart valves
This matters because the target INR depends on the indication and, in valve patients, the type of valve.
2. Compare the result with the patient’s target INR
In broad terms:
- INR below target indicates subtherapeutic anticoagulation, with an increased thromboembolic risk
- INR within target indicates therapeutic anticoagulation
- INR above target indicates supratherapeutic anticoagulation, with an increased bleeding risk
3. Interpret the INR in clinical context
An abnormal INR should prompt review of factors that commonly affect warfarin control:
- Missed or extra doses
- Drug interactions (e.g. antibiotics, azole antifungals, amiodarone, NSAIDs, antiplatelets, herbal products)
- Dietary vitamin K changes
- Alcohol intake
- Acute illness, diarrhoea, vomiting, reduced oral intake, or liver dysfunction
- Trend in previous INR results
4. Assess the patient, not just the laboratory value
Always consider whether there is evidence of:
- Bleeding: melaena, haematuria, epistaxis, bruising, heavy menstrual bleeding, haematemesis, or unexplained anaemia
- Thromboembolism if the INR is low: stroke symptoms, chest pain, dyspnoea, or limb swelling depending on the indication
Why this matters
Warfarin remains a high-risk medicine because both under-anticoagulation and over-anticoagulation can cause harm. A low INR may leave the patient inadequately protected from stroke, recurrent VTE, or valve thrombosis, while a high INR increases the risk of major bleeding.
Pharmacist practice point
INR is not simply a number to classify as low or high. It is a marker of anticoagulation intensity that must be interpreted in relation to the patient’s indication, target range, medicines, comorbidities, and clinical presentation.
For pharmacists, reviewing INR means asking not only ‘Is this result out of range?’ but also ‘Why is it out of range, and is the patient safe right now?'”
Stay updated with Hemostasis Today.
-
Nov 21, 2026, 20:00Jeyda Star: The FAST Signs of Stroke and the Reality of Life Afterward
-
Nov 21, 2026, 19:59Daniel Lindholm: Women Showed the Largest Improvement in Stroke Risk Over Time in Heart Failure
-
Nov 21, 2026, 19:56Neil Arrowsmith: Raising Awareness of Pulmonary Embolism in Young People
-
Nov 21, 2026, 19:52Muhammad Zeeshan Jamal: Thrilled to Present Our Research on Intermediate-Risk Acute PE in Abu Dhabi
-
Nov 21, 2026, 19:50Mounisha Devireddy: Proud to Share Our Research on High-Risk PE in Pregnancy
-
Nov 21, 2026, 19:47Melissa Hollo: How Severe Anemia Increases the Odds of Acute HF During Pregnancy and Postpartum
-
Nov 21, 2026, 19:44Ashenafi Tazebew Amare: Building Sustainable Systems to Close the Anti-D Immunoglobulin Access Gap in LMICs
-
Nov 21, 2026, 19:43Sheharyar Raza: Interpreting Clotting Times Through Reptilase Time and Thrombin Time Assays
-
Nov 21, 2026, 19:42Minoo Ahmadinejad: Serving on the ISTH 2027 Scientific Theme Committee for Women’s Health