


Edward Lee Carter: Optimizing Anticoagulation in Cirrhosis Beyond the Lab Numbers
Edward Lee Carter, Clinical Pharmacist Practitioner at U.S. Department of Veterans Affairs, shared a post on LinkedIn:
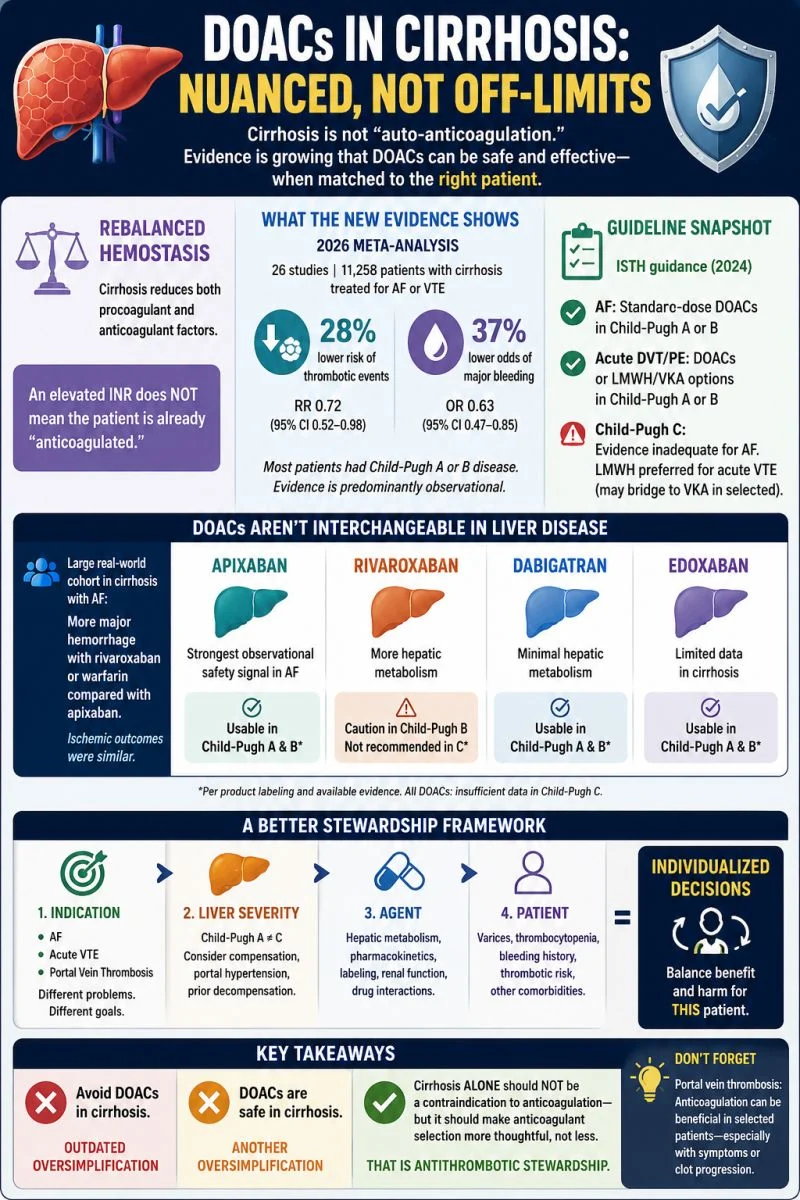
”DOACs in cirrhosis: the evidence is becoming harder to dismiss-but ‘cirrhosis’ is not one anticoagulation phenotype.
For years, anticoagulation in cirrhosis has lived in an uncomfortable gray zone.
The INR may be elevated. Platelets may be low. Portal hypertension or varices may be present. Yet cirrhosis does not protect patients from thrombosis.
We increasingly recognize cirrhosis as a state of rebalanced hemostasis-with alterations in both procoagulant and anticoagulant pathways. An elevated INR does not capture that balance and does not mean the patient is already ‘anticoagulated.’
A 2026 meta-analysis of 26 studies and 11,258 patients with cirrhosis treated for AF or VTE found DOACs were associated with:
- Fewer thrombotic events – RR 0.72
- Less major bleeding – OR 0.63
Encouraging-but most patients had Child-Pugh A or B disease, and the evidence was predominantly observational.
ISTH guidance already supports standard-dose DOACs for appropriately selected patients with AF and Child-Pugh A or or B cirrhosis. DOACs or LMWH or VKA are options for acute VTE in A or B.
Child-Pugh C is different. Evidence is much thinner, and routine extrapolation from compensated cirrhosis is difficult to justify.
Another important lesson:
DOACs aren’t necessarily interchangeable in liver disease.
A large observational cohort of patients with cirrhosis and AF found more major hemorrhage with rivaroxaban or warfarin than apixaban, with similar ischemic outcomes.
Compelling—but not randomized evidence.
For me, a better stewardship framework is:
Indication to liver severity to agent to patient.
- Indication: AF, acute VTE and portal vein thrombosis are different problems.
- Liver severity: Child-Pugh A is not Child-Pugh C. Compensation, portal hypertension and prior decompensation matter.
- Agent: Hepatic metabolism, pharmacokinetics, labeling, renal function and interactions differ among DOACs.
- Patient: Varices, thrombocytopenia, bleeding history and thrombotic risk still matter.
So perhaps we should stop asking:
‘Can a patient with cirrhosis receive a DOAC?’
and instead ask:
‘What are we treating, how advanced is the liver disease, and which anticoagulant offers this patient the best balance of benefit and harm?’
The accumulating evidence is reassuring—but we shouldn’t replace one oversimplification with another.
‘Avoid DOACs in cirrhosis.’
‘DOACs are safe in cirrhosis?.’
A better conclusion:
- Cirrhosis alone should not be considered a contraindication to anticoagulation—but it should make anticoagulant selection more thoughtful, not less.
That’s antithrombotic stewardship.”
Other posts featuring Edward Lee Carter on Hemostasis Today.
-
Sep 29, 2026, 12:02Hajra Malik: Bridging Language Gaps in Hematology With AI
-
Sep 29, 2026, 11:57Joan Montaner: Can Blood Test Identify Intracerebral Hemorrhage Within Minutes?
-
Sep 29, 2026, 11:43From Years Without Answers to Life With Hemophilia Care – WFH
-
Sep 29, 2026, 11:32Sara Al Dallal: Transforming Hemophilia Care Across the Gulf
-
Sep 29, 2026, 11:21Richard Davis: Rapid Rescue in Massive Pulmonary Embolism
-
Sep 29, 2026, 11:14Nissan Brown: Every Step Counts for the Hemophilia Community
-
Sep 29, 2026, 11:03Zain Khalpey: SINGLE AF Adds New Evidence to the Anticoagulation Debate
-
Sep 29, 2026, 10:54How Does Haemophilia Affect Motor Development in Infants? – EAHAD
-
Sep 29, 2026, 10:49Alison Davey: The Vital Role of Community Support in Bleeding Disorders