


Andreas Calatzis: Chasing Biologically Inactive Heparin?
Andreas Calatzis, Managing Director of Eonis GmbH and Dynabyte GmbH, shared a post on LinkedIn:
”Chasing biologically inactive heparin?
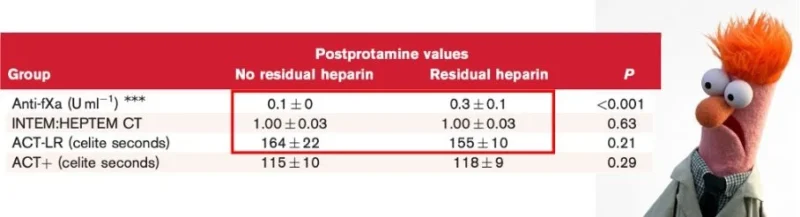
Look at this figure (fig. 3 in (1)). The authors conclude ‘Both the ACT-LR and ACT plus tests of Hemochron Signature Elite device and the INTEM:HEPTEM CT ratio of ROTEM Sigma device have poor ability to detect residual heparin shortly after protamine administration’.
My interpretation is that the ‘residual heparin’ reported in the study, is actually biologically inactive and correctly not detected by the whole blood tests and incorrectly detected by the anti-Xa.
Therefore the ‘poor ability to detect residual heparin’ claimed by the authors, is actually based on a wrong assumption that anti-Xa is a valid reference in this clinical context.
This interpretation is based on recent publications, which show that dextran sulfate used in anti-Xa assays can liberate biologically inactive heparin and thus lead to false positive results (2-3, by Michael Hardy, Francois Mullier, Jonathan Douxfils et al).
Almost all anti-Xa tests available on the market (by Werfen, Siemens and Hyphen/Sysmex) contain dextran sulfate, a chemical which is intended to make the test more robust.
However as highlighted in (2-3) this chemical can also release biologically inactive heparin, which should not be detected by a heparin assay.
Another aspect supporting my suspicion that the anti-Xa results are wrong in this study (1), is the fact that it is simply implausible that 3 heparin-sensitive assays would show zero signal at 0.3 U heparin /ml.
A more detailed discussion of this problem (assuming that anti-Xa is a validated reference for applications it was neither developed nor validated for) can be found in our recent perspective article (4).
- (1) Moilanen J, Pada M, Ohtonen P, Kaakinen T, Taskinen P, Savolainen ER, Erkinaro T. Thromboelastometry and two activated clotting tests in detecting residual heparin after protamine in cardiac surgical patients: A prospective cohort study. Eur J Anaesthesiol. 2025 May 1;42(5):398-406.
- (2) Hardy, M, Cabo, J, Deliège, A, Douxfils, J, Gouin-Thibault, I, Lecompte, T, and Mullier, F. Reassessment of dextran sulfate in anti-Xa assay for unfractionated heparin laboratory monitoring. Res Pract Thromb Haemost. (2023) 7:102257.
- (3) Lasne, D, Toussaint-Hacquard, M, Delassasseigne, C, Bauters, A, Flaujac, C, Savard, P, Mouton, C, De Maistre, E, Stepanian, A, Eschwège, V, Delrue, M, Georges, JL, Gros, A, Mansour, A, Leroy, G, Jouffroy, R, Mattei, M, Beurton, A, Pontis, A, Neuwirth, M, Nedelec-Gac, F, Lecompte, T, Curis, E, Siguret, V, and Gouin-Thibault, I. Factors influencing anti-Xa assays: a multicenter prospective study in critically ill and noncritically ill patients receiving unfractionated heparin. Thromb Haemost. (2023) 123:1105–15.
- (4) Weber CF, Zacharowski K, Calatzis A, Lindner ML. Monitoring unfractionated heparin in ECMO and cardiac surgery: the search for a valid reference standard. Front Med. 2026;13:1818646. doi:10.3389/fmed.2026.1818646. doi:10.3389/fmed.2026.1818646.”
Stay updated on all scientific advances with Hemostasis Today.
-
Nov 11, 2026, 15:42Tareq Abadl: The Clinical Impact of Kell Alloimmunization
-
Nov 11, 2026, 15:30Alejandro González Veliz: Does PCI Change The Long-Term Outcome In Stable Coronary Artery Disease?
-
Nov 11, 2026, 15:25Preparing for the SoHO Regulation – EBA Board Convenes in Vienna – European Blood Alliance
-
Nov 11, 2026, 15:20Vaidehi Prasanth: IV Iron in Heart Failure – Exploring Hospitalisation Benefits vs. Infection Risk in Open Heart
-
Nov 11, 2026, 15:18Stefan Prendić: Can Algorithms Support Antibody Identification in Immunohematology?
-
Nov 11, 2026, 15:12Perioperative Challenges in Hemophilia Patients on Rebalancing Therapies
-
Nov 11, 2026, 15:03Maria Elisa Mancuso: World-Renowned Faculty and 33 Global Participants Unite at Hemophilia Academy 2026
-
Nov 11, 2026, 15:01Hassan Raza: The JAK2 V617F Revolution
-
Nov 11, 2026, 14:57Edward Lee Carter: Factor Xla Inhibition Enters Clinical Practice – FDA Approval of Asundexian