


Dilini Christina Ranasinghe: An Exception to the ‘Universal Donor’ – Bombay (Oh)
Dilini Christina Ranasinghe, Registrar in Transfusion Medicine at National Blood Centre, shared a post on LinkedIn:
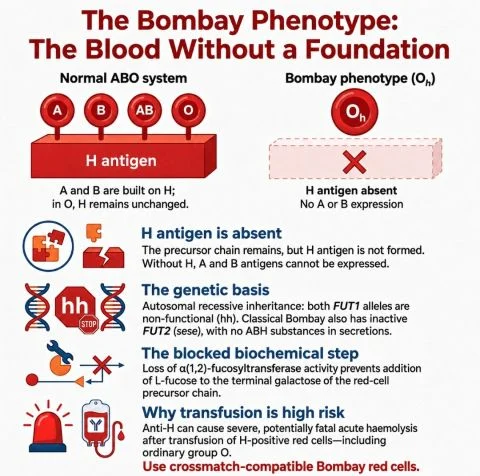
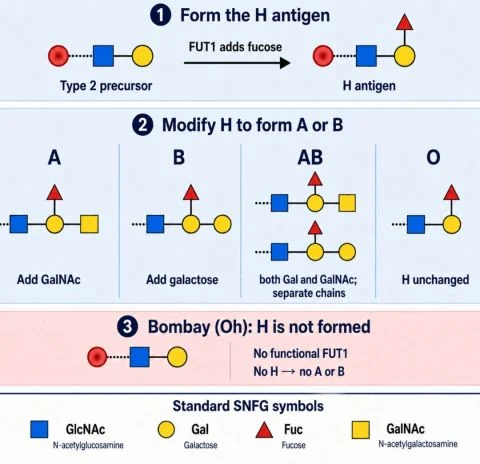
“An Exception to the ‘Universal Donor’: Bombay (Oh)
A 68-year-old woman with myocardial infarction and a haemoglobin of 5.6 g/dL was referred to the Immunohaematology Reference Laboratory following positive antibody screening and difficulty obtaining crossmatch-compatible blood.
Her forward group appeared to be O.
However:
- Reverse grouping showed strongly positive reactions with A₁, B and O cells.
- Reactivity remained strongly positive at 37 degrees Celsius.
- Antibody screening was panreactive at strongly positive.
- Her red cells did not react with anti-H lectin, while known group O cells reacted at 4+.
The findings were consistent with the Bombay (Oh) phenotype.
Anti-H is the key transfusion hazard; ordinary group O red cells are therefore unsafe.
Fortunately, a Bombay (Oh) red-cell unit, which was IAT crossmatch compatible, was available in stock.
But what if it had not been?
Sri Lanka’s centrally coordinated blood transfusion service and rare-donor registry allow islandwide donor mobilisation.
Nevertheless, identifying an eligible donor, arranging collection and testing, and transporting the unit all take time – time that an acutely ill patient may not have.
For elective procedures, early planning is essential:
- Activate the rare-donor registry.
- Screen siblings and other family members for potential compatible donors.
- Coordinate donations carefully with the blood service.
- Optimise the patient and minimise blood loss through patient blood management.
Family screening does not replace donor eligibility assessment or compatibility testing.
Cellular components donated by relatives must also be irradiated.
Rare blood saves lives – but only when recognition, planning and donor coordination come together.”
Find more posts featuring Dilini Christina Ranasinghe on Hemostasis Today.
-
Oct 17, 2026, 17:27John Strouse: Building Standards for Whole-Person Sickle Cell Care Through Collaboration
-
Oct 17, 2026, 17:20Jean-Jacques Kiladjian: Exploring the Future of Polycythemia Vera Treatment at MPN Horizons 2026
-
Oct 17, 2026, 17:10Habib Bennaceur: Strengthening Collaboration in Haemophilia, Sickle Cell Disease and Thalassaemia in India
-
Oct 17, 2026, 16:58Danny Hsu: Building Connections at the AUSNBled Collaborative Dinner in Auckland
-
Oct 17, 2026, 16:48Kalyan Roy: Enhancing Patient Experience Through Learning and Collaboration
-
Oct 17, 2026, 16:43Wilfried Dinh: Antiplatelet Therapy in 2026: Duration is Becoming a Dynamic Decision
-
Oct 17, 2026, 16:37Ian Setchfield: Dr. Evans Presents on Safe Anticoagulation Prescribing at East Kent Hospitals
-
Oct 17, 2026, 16:33Lewis Thomas: Connecting Through Shared Experiences at ASCAT 2026
-
Oct 17, 2026, 16:29Nilesh Jethwa: Yasmin Adverse Event Reports Exceed 23,000 Over Two-Year Period