

Dr Wael El Banna/LinkedIn
Oct 5, 2025, 08:30
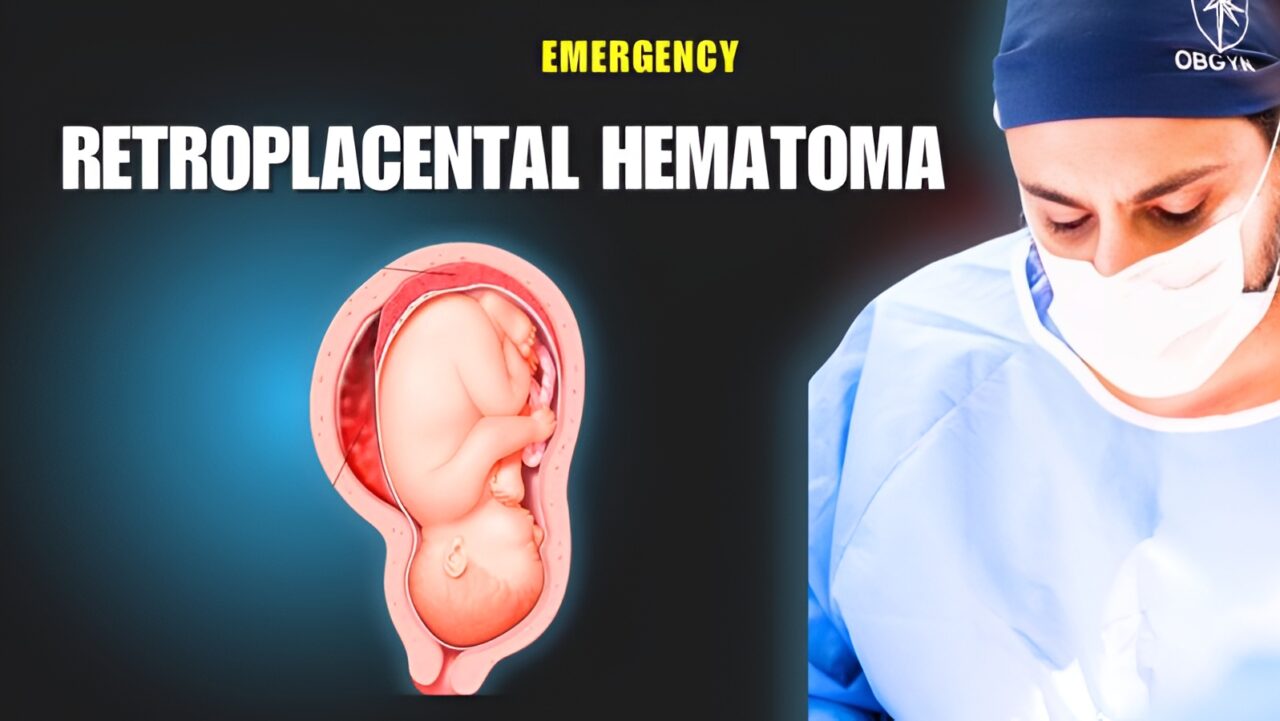
Dr Wael El Banna: How A Retroplacental Hematoma Looks Like In A Surgery Room
Dr Wael El Banna, OBGYN Consultant at FertiClinic Fertilization Group, Owner of ElBanna Group, posted on LinkedIn:
”How a retroplacental hematoma looks like in a surgery room. (watch that video )
The key management steps are :
Immediate Resuscitation and Multidisciplinary Care
- Initial focus is on maternal resuscitation following the ABC approach: airway, breathing, and circulation.
- Management should be according to locally-created massive obstetric hemorrhage protocols, led by a senior obstetrician, anesthetist, haematologist, and the midwifery team, with laboratory and portering staff alerted.
- Bloods should be immediately sent for blood grouping, crossmatch, full blood count, and coagulation screen, with 4 units of crossmatched blood prepared.
- Senior and experienced staff should be involved as early as possible in both obstetric and anaesthetic roles.
Management of Coagulopathy
- Disseminated intravascular coagulation (DIC) can develop rapidly in massive abruption; urgent clotting studies and platelet count are necessary.
- Up to 4 units of fresh frozen plasma (FFP) and 10 units of cryoprecipitate can be administered empirically if relentless bleeding persists while awaiting test results.
- Haematology input is vital for guiding further transfusions and clotting factor support.
Delivery
- If maternal or fetal compromise is evident, immediate delivery is required.
- Mode of delivery depends on fetal and maternal status:
- If fetal death has occurred and maternal condition is stable, vaginal delivery is generally recommended.
- If fetus is alive but compromised, expedite delivery by caesarean section, unless vaginal delivery is imminent.
Additional Considerations
- Continuous maternal and fetal monitoring is essential during and after the acute event.
- All RhD-negative women should receive anti-D immunoglobulin if more than 20 weeks gestation.
- Ongoing monitoring for PPH, renal dysfunction, and further coagulopathy is needed post-delivery.
- If the patient develops hypovolemia or shock, ICU-level support and ongoing multidisciplinary care are mandatory.”
Stay updated with Hemostasis Today.
-
Sep 24, 2026, 13:41Mahmoud Samir Bayomi: Raise ITP Awareness and Improve Patient Care
-
Sep 24, 2026, 12:56Maria Helena Parrinello: A New Score for Chronic GvHD Risk Assessment at the SIE Congress
-
Sep 24, 2026, 12:44Shehab Mohamed: TP53 Mutations and Outcomes in Myeloproliferative Neoplasms
-
Sep 24, 2026, 12:34Francesca Palandri: Is There Still a Place for Splenectomy in ITP in the Modern Era?
-
Sep 24, 2026, 12:15Cedric Hermans: RPTH Illustrated Review on Von Willebrand Disease
-
Sep 24, 2026, 11:48Factor XII Inhibition and the Future of Contact Pathway Targeting
-
Sep 24, 2026, 08:55Andres Gudino: Clot Characterization Through Hounsfield Units in Ischemic Stroke
-
Sep 24, 2026, 06:52Gina Sado: Screening-Detected Atrial Fibrillation Carries High Risk of Heart Failure
-
Sep 24, 2026, 06:33Benjamin Vipler: Optimal Oral Anticoagulation Choice in Atrial Fibrillation and Advanced CKD