


Abdul Mannan: Can Amyloid-β Be Transmitted via Blood Components?
Abdul Mannan, Consultant Haematologist at Betsi Cadwaladr University Health Board, shared a post on LinkedIn about a recent article by Gargi Banerjee et al., published in The Lancet, adding:
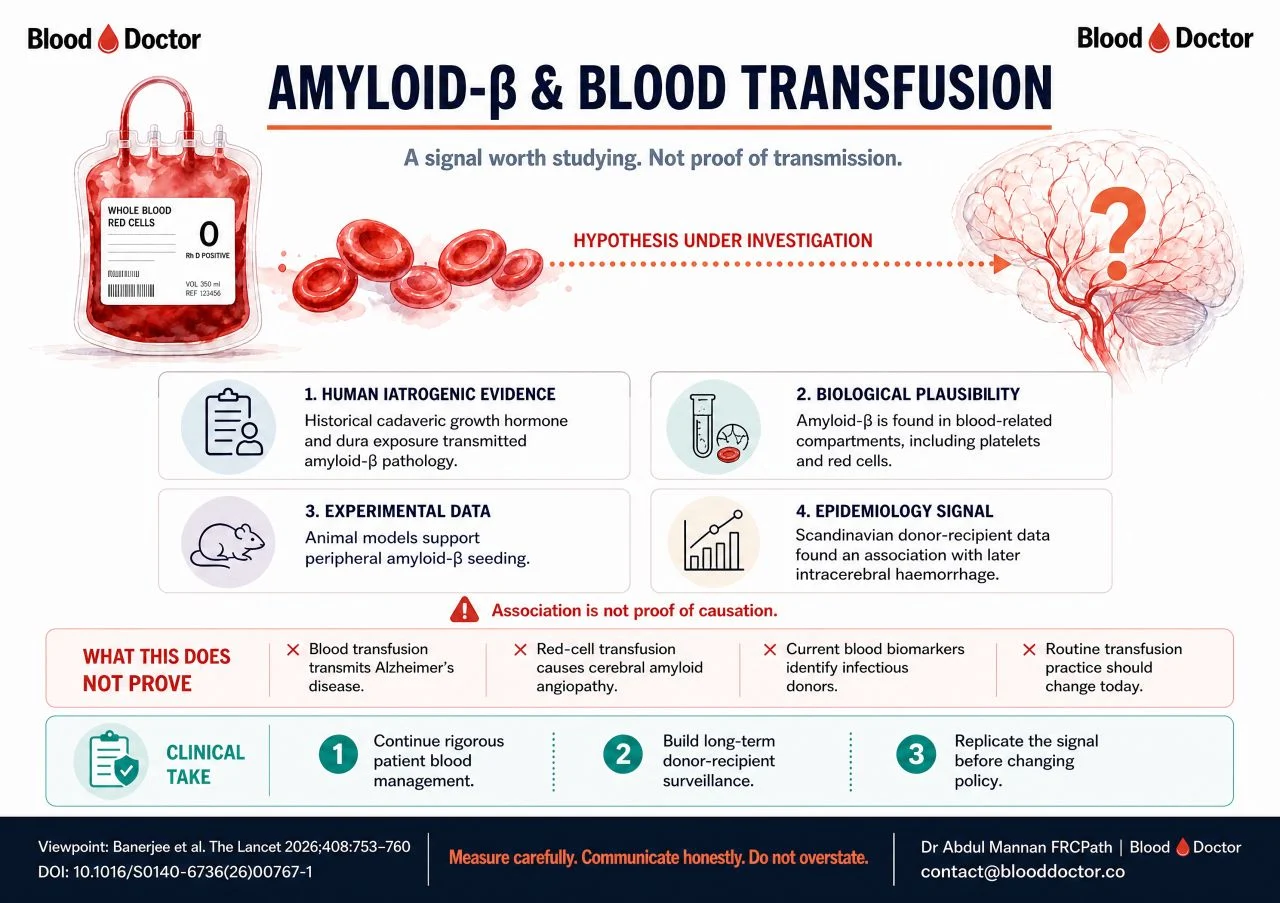
”A blood-safety question is emerging before we have a screening assay, a reliable denominator, or proof that transmission occurs:
Could amyloid-β pathology, in rare circumstances, be carried through blood components?
It is a question that demands investigation, but not premature action.
A new Lancet Viewpoint brings together an uncomfortable body of evidence.
We already know that amyloid-β pathology has been transmitted through certain historical medical exposures, particularly cadaver-derived growth hormone and dura mater. These were not ordinary transfusion settings, but they changed what we thought possible.
The blood-transfusion question rests on a convergence of findings:
- amyloid-β can behave as a proteopathic seed
- it is found in blood-related compartments, including platelets and red cells
- animal work supports peripheral seeding
- Scandinavian donor-recipient data found an association between donor haemorrhage phenotypes and later intracerebral haemorrhage in recipients
That is enough to justify serious study.
It is not enough to claim that blood transfusion transmits Alzheimer’s disease or cerebral amyloid angiopathy.
It is not enough to introduce donor screening, age matching, or changes to transfusion practice.
And it is certainly not a reason to alarm patients who have received blood.
The immediate clinical lesson is more disciplined.
Patient blood management matters because every transfusion should have a clear expected benefit. Long-term donor-recipient linkage matters because it may detect safety signals before a direct assay exists. And language matters because uncertainty can be distorted in both directions: dismissed too quickly or turned into a frightening headline.
Blood safety has been harmed by both errors.
The right response is neither dismissal nor alarm. It is replication, better surveillance, assay development, and honest communication about what we know and what we do not.”
Title: Risk of transmission of amyloid β pathology via transfused blood products
Article: Gargi Banerjee, Gustaf Edgren, Jingcheng Zhao, Prof Neil M Ferguson, Prof Heli Harvala, James Hope, Graham S Jackson, Prof Philip J Lowry, Prof Simon Mead, Silvia A Purro, Prof Jonathan M Schott, Prof Marc L Turner, Prof David J Werring, Prof Henrik Zetterberg, Prof John Collinge
 Other posts featuring Abdul Mannan with Hemostasis Today.
-
Oct 13, 2026, 02:01Nour Al-Mozain: Is It Really Anti-D? – Unraveling Auto-Anti-LW in the Transfusion Laboratory
-
Oct 13, 2026, 01:51Berenice Villegas: The Role of Morphologic Evaluation in Body Fluid Differential Analysis
-
Oct 13, 2026, 01:44Debadrita Ray: Evaluating vWF and VITRO Score for Detecting CSPH in cACLD Patients
-
Oct 13, 2026, 01:34Nagesh Ramesh: Donating Blood for International Plasma Awareness Week
-
Oct 12, 2026, 21:51Sam Botchey: Orthobiologics Are Advancing but the Evidence Must Keep Pace
-
Oct 12, 2026, 21:50Serum Vitamin D, Platelet Function, and Bleeding in Primary ITP – Platelets Journal
-
Oct 12, 2026, 21:30Nika Samadzadeh Tabrizi: Looking Forward to the PACeS Trial on Anticoagulation for POAF
-
Oct 12, 2026, 21:28Michael Megaly: Does Coronary Ectasia Affect Outcomes in Acute Coronary Syndromes?
-
Oct 12, 2026, 21:25Vitor Borin P. de Souza: Think Twice Before Anticoagulating an Isolated Subsegmental PE