


Varun Capoor: How Therapeutic Apheresis and Transfusion Medicine Can Complement Clinical Management in SCD
Varun Capoor, Senior Consultant and Incharge Transfusion Medicine Specialist at Paras Health, shared a post on LinkedIn:
“Red Cell Exchange in Sickle Cell Disease: The Role of Transfusion Medicine in Perioperative Care
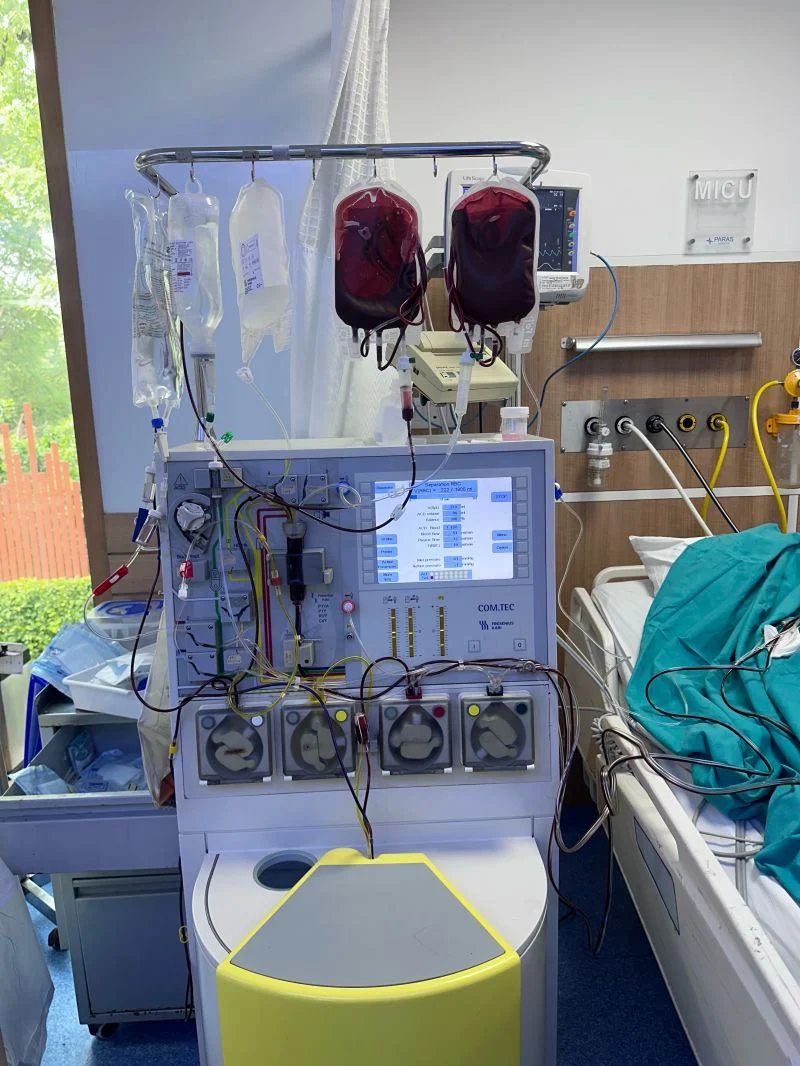
A recent case highlighted for me how Therapeutic Apheresis and Transfusion Medicine can complement clinical management in Sickle Cell Disease (SCD)—particularly when a patient is being prepared for major surgery.
A 21-year-old male with SCD, Hb 9.5 g/dL and Hct 27.2%, was planned for elective hip hemiarthroplasty.
With Hb already around 9.5 g/dL, simple transfusion could increase red-cell mass and potentially blood viscosity.
After multidisciplinary discussion, automated red cell exchange (RCE) was chosen to reduce the circulating HbS burden while maintaining the patient’s red-cell volume.
The RCE
Automated RCE was performed using a COM.TEC cell separator.
- Blood volume processed: 5,205 mL
- TBV: 4,985 mL
- Pre/post Hct: 27%
- RBC replacement volume: 1,850 mL
HPLC: Before – After
- HbS: 77% – 18.2%
- HbA: 2.4% – 76.7%
- HbF: 11.3% – 2.2%
The important observation was the substantial reduction in HbS without increasing the Hct, which illustrates one of the key principles of RCE: changing the composition of circulating RBCs rather than simply adding more RBC mass.
Where does Transfusion Medicine fit in?
The apheresis procedure is only one component of the process.
For patients with SCD, transfusion planning involves:
- Review of previous transfusions and historical antibodies
- Antibody screening and identification
- Extended RBC phenotype/genotype where appropriate
- Appropriate Rh and Kell antigen matching
- Selection of compatible, leukoreduced RBC components
- Monitoring for acute and delayed haemolytic transfusion reactions
- Appropriate pre- and post-RCE laboratory assessment
In this patient, the RBC selection was based on his ABO/Rh status, extended Rh phenotype and Kell status, with a negative antibody screen.
The bigger lesson
Preoperative transfusion in SCD should be individualized according to the patient’s Hb, HbS%, clinical phenotype, surgical risk and transfusion history.
RCE can be particularly useful when a significant reduction in HbS is desired but simply increasing haemoglobin through top-up transfusion is undesirable.
In this case:
- HbS 77% – 18.2%
- Hct 27% – 27%
A good example of how Apheresis plus Transfusion Medicine plus Haematology plus Anaesthesia plus Surgery can work together to optimize a patient before major surgery.
Better transfusion decisions.
Better apheresis practice.
Better patient care.”
Stay updated with Hemostasis Today.


-
Nov 13, 2026, 03:21Abdul Muqtadir Abbasi: Iron Deficiency Beyond Anemia and the Importance of Finding the Cause
-
Nov 13, 2026, 03:05Marc Carrier: Aspirin vs Anticoagulants for VTE Prevention After Joint Replacement
-
Nov 13, 2026, 02:28Julia Sjöberg: ROCK1 Inhibition and Red Blood Cell Recovery After Chemotherapy
-
Nov 13, 2026, 02:07Tonie Reincke: Understanding Deep Vein Thrombosis and Vascular Health
-
Nov 13, 2026, 01:52Akshita Singh: The Remarkable Process of Blood Clotting
-
Nov 12, 2026, 22:52Milka Koupenova: The Role of Platelet RIG-I in Regulating Thrombotic Responses
-
Nov 12, 2026, 22:50Arun V J: Why Has India Still Not Achieved 100% Voluntary Blood Donation?
-
Nov 12, 2026, 22:49Sickle Cell Disease Deserves to Be Prioritised in Ghana – ISCC
-
Nov 12, 2026, 22:47Samir Kumar Beura: Delighted to Serve as a Topic Editor for a Research Topic in Frontiers in Neuroscience