


Aryabhatta Sadhu: ABO and Rh Incompatibility In Stem Cell Transplantation
Aryabhatta Sadhu, Attending Consultant and Head of Transfusion Medicine at Fortis Hospital Shalimar Bagh, New Delhi, shared a post on LinkedIn:
“When ABO and Rh incompatibilities enter the transplant timeline, blood support stops being routine.
The question is no longer:
‘Which blood group should be issued?’
The real question becomes:
‘Whose red cells, whose antibodies, and whose marrow are dominant today?’
Case report decision dropdown
ABO/Rh-incompatible haploidentical HSCT is not a single transfusion decision.
It is a phase-wise Transfusion Medicine problem.
This case involved:
- haploidentical HSCT
- minor ABO mismatch
- major Rh incompatibility
- harvest and graft-risk assessment
- peri-transplant component planning
- post-transplant haemolysis surveillance
The practical challenge was not simply blood availability.
It was answering four recurring questions:
- Whose haematopoiesis is dominant?
- Whose antibodies are active?
- Which blood group should be supported today?
- Is the post-transplant problem cytopenia, haemolysis, or delayed engraftment?
Pre-transplant
Start before conditioning.
Map ABO/RhD status, antibody screen, DAT baseline, isoagglutinins, and component policy. HCT candidates require a clear plan for leukoreduced and irradiated support.
Harvest / graft
The graft is not just CD34-positive cells.
Assess plasma incompatibility, red cell contamination, donor antibody burden, and whether graft manipulation is required.
Peri-transplant
This is where routine transfusion logic becomes dangerous.
The patient’s blood group is biologically in transition. Red cells, platelets, and plasma require phase-specific selection based on donor-recipient compatibility.
Post-transplant
Do not reduce every falling haemoglobin to expected cytopenia.
In ABO-mismatched HSCT, consider delayed haemolysis, passenger lymphocyte effect, delayed erythroid engraftment, PRCA-like patterns, and chimerism context.
Why Transfusion Medicine matters
The value is not ‘issuing blood.’
The value is maintaining transplant-support continuity through:
- immunohaematology mapping
- safe component selection
- graft-risk assessment
- haemolysis surveillance
- donor-recipient compatibility transition
It is transplant immunohaematology in motion.”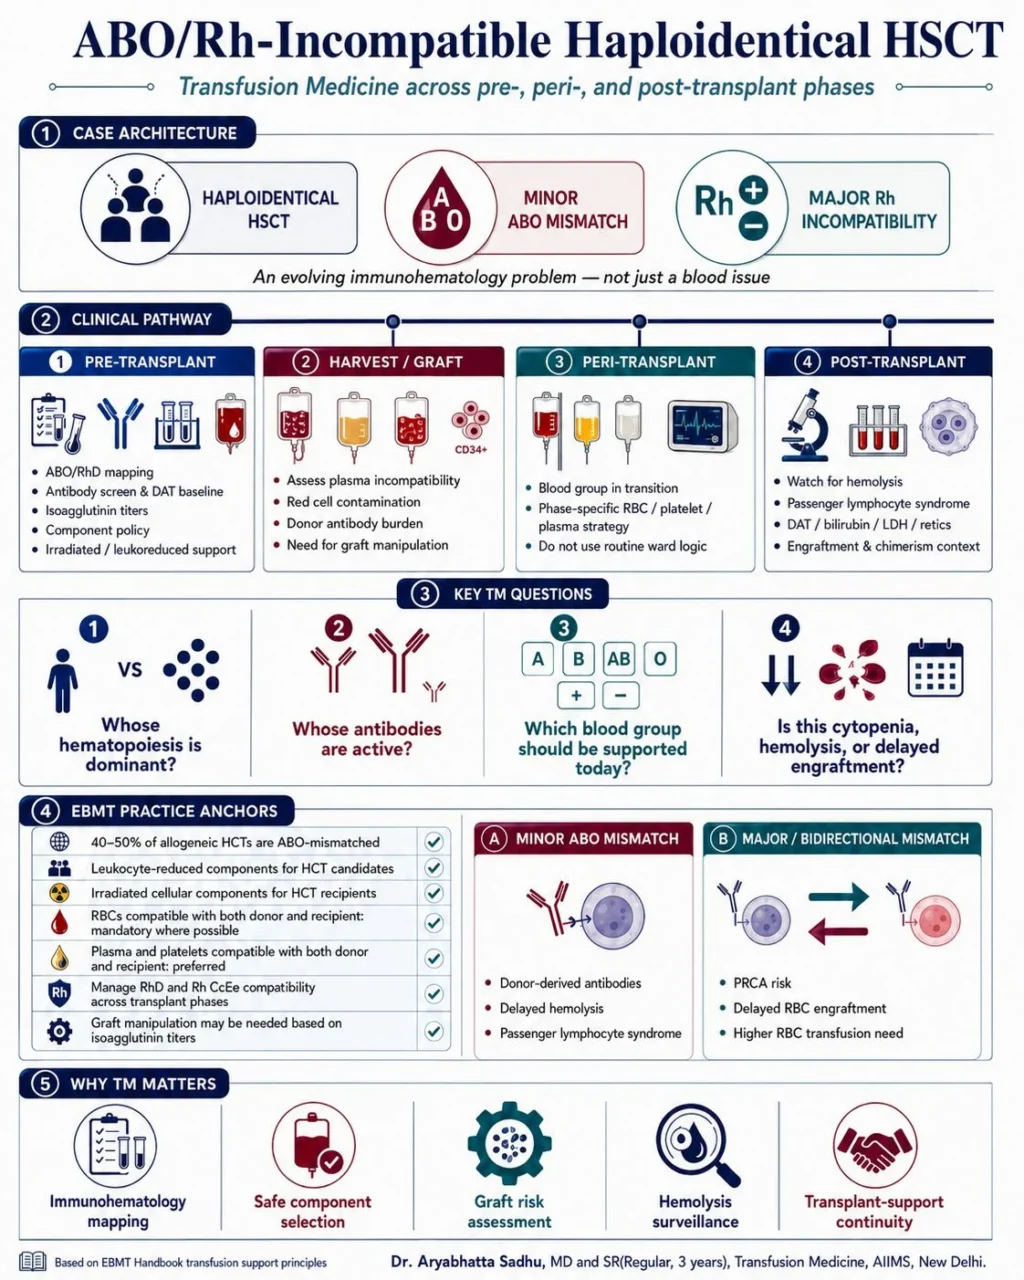
Other posts featuring Aryabhatta Sadhu with Hemostasis Today.
-
Sep 23, 2026, 04:34David Akande: When Sickle Cell Crises Have No Clear Trigger
-
Sep 23, 2026, 04:13Jean Connors: Safety of Heparin Re-Exposure in Patients with Remote HIT
-
Sep 23, 2026, 04:09Beth Psaila: Applications Now Open for the Gordon Research Conference on Megakaryocytes and Platelets
-
Sep 23, 2026, 03:27Abbie Newton: How Better Data Can Reduce Platelet Wastage
-
Sep 23, 2026, 03:01Suvro Sankha Datta: Rapid Blood Group Genotyping Using Gold Oligo Nanonet Assembly
-
Sep 23, 2026, 02:55Asghar Muhammad: Exploring New Ways to Expand Blood Transfusion Compatibility
-
Sep 23, 2026, 02:49Bianca Rocca: Personalized Cardiovascular Pharmacotherapy in the September 2026 EHJ Issue
-
Sep 23, 2026, 02:35Udaya RajBhandari: A Hidden Risk of Repeated Transfusions in β Thalassemia
-
Sep 23, 2026, 00:08Janar Sathananthan: The Importance of Durable Drug Delivery in DCB Therapy