


Mohd Ashhad: How Much Does Hemoglobin Increase After 1 Unit of PRBC?
Mohd Ashhad, Medical Laboratory Technologist at Blood Bank, shared a post on LinkedIn։
“How Much Does Hemoglobin Increase After 1 Unit of PRBC?
A common question in blood transfusion practice is:
‘After transfusing one unit of packed red blood cells (PRBC), how much should the patient’s Hb increase?’
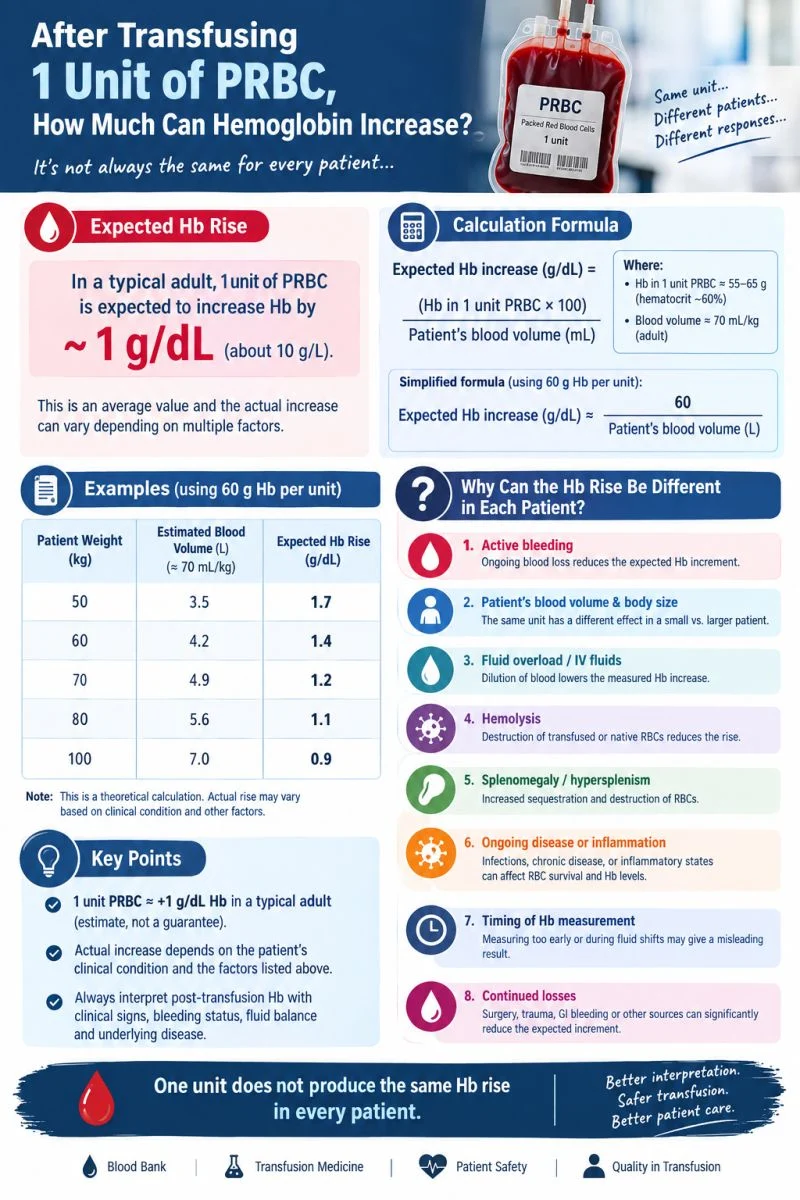
In an average adult patient, transfusion of 1 unit of PRBC is generally expected to increase Hb by approximately 1 g/dL (about 10 g/L), although the actual response can vary.
Why can the Hb rise be different from patient to patient?
1. Active bleeding
If the patient is still bleeding, the transfused RBCs are being lost, so the Hb may increase less than expected.
2. Patient’s blood volume and body size
The same unit has a different effect in a small patient compared with a larger patient.
3. Fluid overload or IV fluids
Large amounts of IV fluids can dilute the blood and produce a smaller measured Hb increase.
4. Hemolysis
Destruction of RBCs—whether immune-mediated or due to another cause—can reduce the expected Hb increment.
5. Splenomegaly or hypersplenism
An enlarged or overactive spleen may increase RBC sequestration and destruction.
6. Ongoing disease or inflammation
Conditions such as severe infection, inflammation, or chronic disease can affect RBC survival and Hb levels.
7. Timing of the Hb measurement
Hb should be assessed at an appropriate interval after transfusion. Measuring too early or during major fluid shifts may give a misleading impression.
8. Transfusion of a patient with significant ongoing losses
Bleeding from surgery, trauma, gastrointestinal bleeding, or other sources can significantly reduce the expected increment.
Key point:
1 unit PRBC increases Hb by approximately1 g/dL in a typical adult, but this is an estimate—not a guaranteed increase.
As laboratory and transfusion professionals, we should always interpret the post-transfusion Hb together with the patient’s clinical condition, bleeding status, fluid balance, and underlying disease.
One unit does not produce the same Hb rise in every patient.”
Other posts featuring Mohd Ashhad on Hemostasis Today.
-
Oct 18, 2026, 07:05Behnood Bikdeli: Vasculearn Network Highlights Expert Perspectives on PE Risk Stratification and Advanced Therapies
-
Oct 18, 2026, 06:27Gregory Makris: NEJM Study Supports Earlier Catheter-Directed Intervention in Intermediate-High–Risk PE
-
Oct 18, 2026, 06:26Danny Hsu: BLOOD 2026 Return to Aotearoa
-
Oct 18, 2026, 02:43Priya Sriskandarajah: Diagnosis and Management of PV and JAK2-Unmutated Erythrocytosis
-
Oct 18, 2026, 02:41C. Michael Gibson: A Meta-Analysis of DOACs and DAPT After Left Atrial Appendage Closure
-
Oct 18, 2026, 02:27What Hematologists Should Remember About the Person Behind the Platelet Count – ASH
-
Oct 18, 2026, 01:44Marta Velia Antonini: How to Deliver CRRT during ECMO?
-
Oct 18, 2026, 01:19Aamir Saeed: Anticoagulation, Cirrhosis, and Other Risk Factors for Post-ERCP Bleeding
-
Oct 18, 2026, 00:33Elad Asher: Does Opening the Clot Change How a Patient Feels Three Months Later?