


Muhammad Usman Tariq/LinkedIn
Apr 28, 2026, 06:29
Muhammad Usman Tariq: A Practical Overview of Central Venous Access
Muhammad Usman Tariq, Senior House Officer at Lincolnshire Community and Hospitals NHS Group, shared a post on LinkedIn:
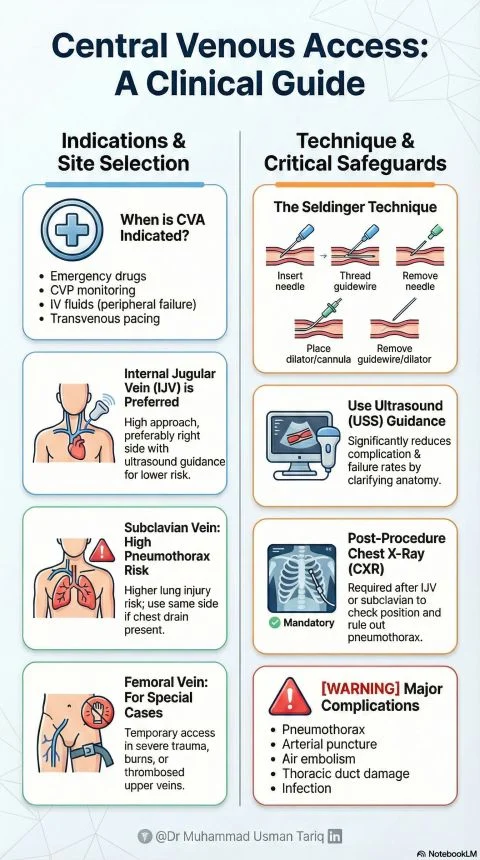
“Central venous access (CVA) is a core skill in acute and critical care.
Safe insertion depends on clear indications, appropriate site selection, and good technique.
Indications for central venous access
- Difficult or failed peripheral access
- Administration of vasoactive drugs (e.g. noradrenaline)
- Rapid fluid resuscitation
- Parenteral nutrition
- Central venous pressure (CVP) monitoring
- Haemodialysis or plasmapheresis
- Frequent blood sampling
Site selection
Internal jugular vein (IJV):
- Preferred in many settings with ultrasound guidance
- Lower risk of pneumothorax compared to subclavian
- Easy compressibility – safer in coagulopathy
Subclavian vein:
- More comfortable for patients
- Lower infection risk
- Higher risk of pneumothorax and difficult to compress
Femoral vein:
- Quick and easy access, especially in emergencies
- No risk of pneumothorax
- Higher infection and thrombosis risk
- Useful during cardiac arrest
Technique (overview)
- Full aseptic precautions (cap, mask, sterile gown, gloves, drapes)
- Patient positioning (e.g. Trendelenburg for IJV)
- Identify landmarks with/without ultrasound
- Local anaesthetic
- Venepuncture – confirm venous blood
- Guidewire insertion
- Dilatation
- Catheter placement and fixation
The Seldinger technique
A standard method used for line insertion:
- Insert needle into vein
- Pass guidewire through needle
- Remove needle
- Pass dilator over guidewire
- Insert catheter over guidewire
- Remove guidewire, flush and secure line
Role of ultrasound
- Improves success rate
- Reduces complications (arterial puncture, pneumothorax)
- Recommended as standard for IJV access
- Real-time guidance is preferred
Post-procedure checks
- Confirm position (CXR for IJV/subclavian)
- Exclude complications (e.g. pneumothorax)
- Aspirate and flush all lumens
- Secure line and apply sterile dressing
- Document procedure
Major complications
Immediate:
- Arterial puncture
- Pneumothorax / haemothorax
- Arrhythmias (guidewire irritation)
- Air embolism
Early / late:
- Infection (line sepsis)
- Thrombosis
- Catheter malposition
- Vessel or nerve injury
Key points
- Use ultrasound whenever possible
- Choose site based on patient factors and indication
- Maintain strict asepsis
- Always confirm position and monitor for complications.”
Stay updated with Hemostasis Today.
-
Sep 30, 2026, 01:52Javed Anees: DADA2 – When a Young Stroke Is More Than a Stroke
-
Sep 30, 2026, 01:51How a Venous Thrombus Becomes Revascularized – ISTH
-
Sep 29, 2026, 22:45Victor Agunyego: Paracetamol – The Most Common Drug We Underestimate
-
Sep 29, 2026, 22:42Nova Sinclair: Advancing the Future of Hematology – Meet Our 2027 Organizing Committee
-
Sep 29, 2026, 22:41Lorenz Räber: Intracoronary Imaging in PCI – Why, When, How, and Which Modality?
-
Sep 29, 2026, 22:31Selma Turkovic: Pleased to Deliver the Opening Presentation at Kingston Hospital
-
Sep 29, 2026, 22:31Miguel Teran: Ultrasound and Simulation in Arterial Blood Sampling
-
Sep 29, 2026, 22:28Mohammad Refaei: Navigating Your Career in Hematology From Training to Practice
-
Sep 29, 2026, 22:27Matteo Foschi: 10 Clinical Pearls for Antithrombotic Therapy in Secondary Stroke Prevention