


W. Alberto Sifuentes Giraldo: Urticarial Vasculitis Clinical Features, Systemic Involvement, and Treatment
W. Alberto Sifuentes Giraldo, Rheumatologist at Hospital Nuestra Señora de Sonsoles (Sacyl), shared a post on LinkedIn about a recent article by Angelo Valerio Marzano et al., published in The Journal of Allergy and Clinical Immunology (JACI), adding:
”Urticarial vasculitis (UV) is an uncommon clinicopathologic entity characterized by painful, often burning, urticaria-like lesions that typically persist for more than 24 hours.
A classic clinical clue is the resolution of these lesions with ecchymotic postinflammatory hyperpigmentation.
Histopathologically, UV is defined by leukocytoclastic vasculitis involving the small dermal blood vessels.
Direct immunofluorescence studies often reveal granular or continuous deposition of immunoglobulins (mostly IgM), complement components (C3 or C4), or fibrin along vessel walls and, in some cases, the dermal-epidermal junction.
Angioedema can occur in approximately 40 percent of patients.
Systemic involvement and subtypes:
While UV may remain limited to the skin, it is frequently a systemic disease. Cutaneous findings can be accompanied by fever, fatigue, and severe arthralgias.
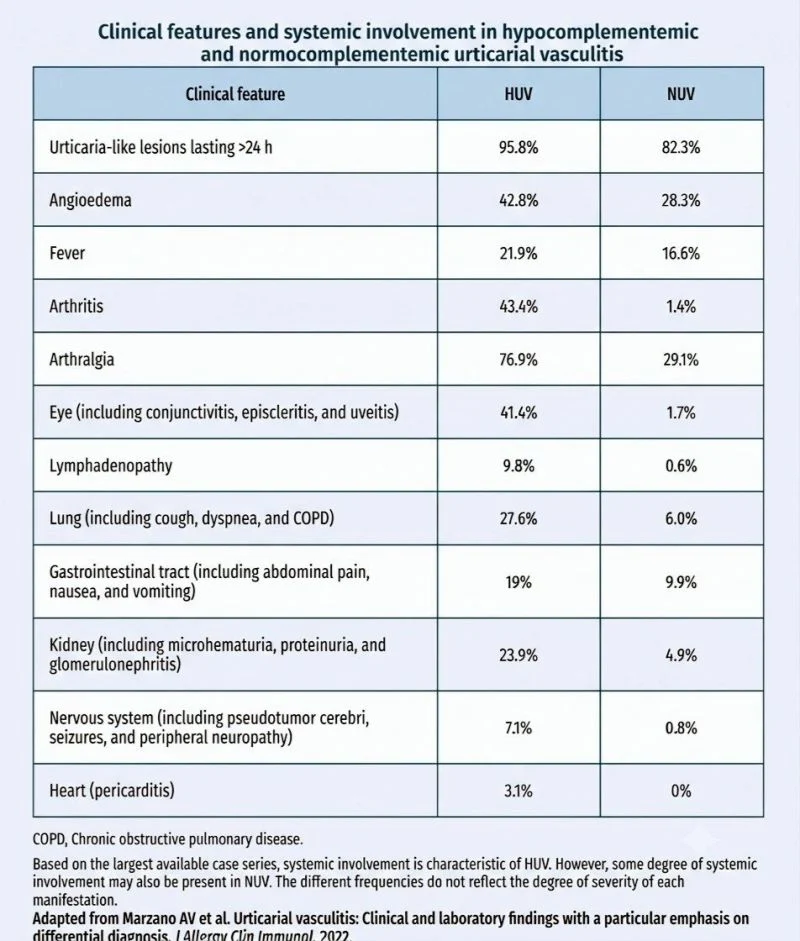
Systemic disease is most notable in the hypocomplementemic variant (HUV), with multiple organs potentially affected, including the kidneys (glomerulonephritis), lungs (cough, dyspnea, increased COPD risk), GI tract (abdominal pain, nausea, vomiting), eyes (episcleritis, uveitis), and less commonly CNS and heart.
HUV can be serious, with higher risk of complications, including potentially fatal multi-organ failure.
Classification into two major subtypes is clinically critical and based on serum complement levels:
- Normocomplementemic Urticarial Vasculitis (NUV): generally lower frequency of systemic involvement; labs show normal serum C1q, C3, and C4.
- Hypocomplementemic Urticarial Vasculitis (HUV): a more severe, immune-complex-mediated small-vessel vasculitis. Defining features are low serum C1q, C3, and C4. Up to 100 percent of HUV patients may have anti-C1q autoantibodies, an important diagnostic marker. Prognosis is generally worse, with 10-year mortality up to 17 percent, primarily from severe renal or pulmonary disease.
Treatment paradigms
Management of UV is tailored to the severity and extent of systemic organ involvement.
- For mild or skin-limited disease: antihistamines (often poorly effective alone), dapsone, omalizumab, and NSAIDs.
- For moderate or systemic disease: systemic glucocorticoids are the mainstay, with dapsone and omalizumab as steroid-sparing agents.
- For severe or multi-systemic disease: high-dose glucocorticoids plus immunosuppressive agents, including mycophenolate mofetil, cyclophosphamide, rituximab, or IL-1 inhibitors, more effective at achieving disease control.”
Title: Urticarial vasculitis: Clinical and laboratory findings with a particular emphasis on differential diagnosis
Authors: Angelo Valerio Marzano, Carlo Alberto Maronese, Giovanni Genovese, Silvia Ferrucci, Chiara Moltrasio, Riccardo Asero, Massimo Cugno
Other posts featuring W. Alberto Sifuentes Giraldo on Hemostasis Today.
-
Oct 16, 2026, 13:10Emanuel Sueldo: CAHT 2026 Celebrates Scientific Progress and Team Achievements
-
Oct 16, 2026, 13:05Maha Othman: Queen’s Health Sciences Advances CAT Risk Models and Pediatric ISTH-BAT Cut-Offs
-
Oct 16, 2026, 13:03Thrombosis Awareness Must Lead to Timely Action – Roche
-
Oct 16, 2026, 12:49Wolfgang Miesbach: 5-Year CBDR Data Confirms Emicizumab Safety and Efficacy in Hemophilia A
-
Oct 16, 2026, 12:40Edward Lee Carter: How Factor XI Inhibition Could Transform Anticoagulation Therapy
-
Oct 16, 2026, 12:40Marc Carrier: Looking Ahead to ISTH 2027 in Vancouver
-
Oct 16, 2026, 12:30Bob Lempke: How One Blood Donation Can Save Up to Three Lives
-
Oct 16, 2026, 12:30Why VWF Therapies Belong on the EU Critical Medicines List – EHC
-
Oct 16, 2026, 12:17Exploring Endothelial Cells, Genetic Fate Mapping, and Revascularization – ISTH