


Pernicious Anemia: What Is It, and How to Distinguish It From True Autoimmune Hemolytic Anemia – Explained by Tareq Abadl
Tareq Abadl, Medical Laboratory Specialist and Director of the Blood Bank at Dr. Abdelkader Al-Mutawakkil Hospital, shared a post on LinkedIn:
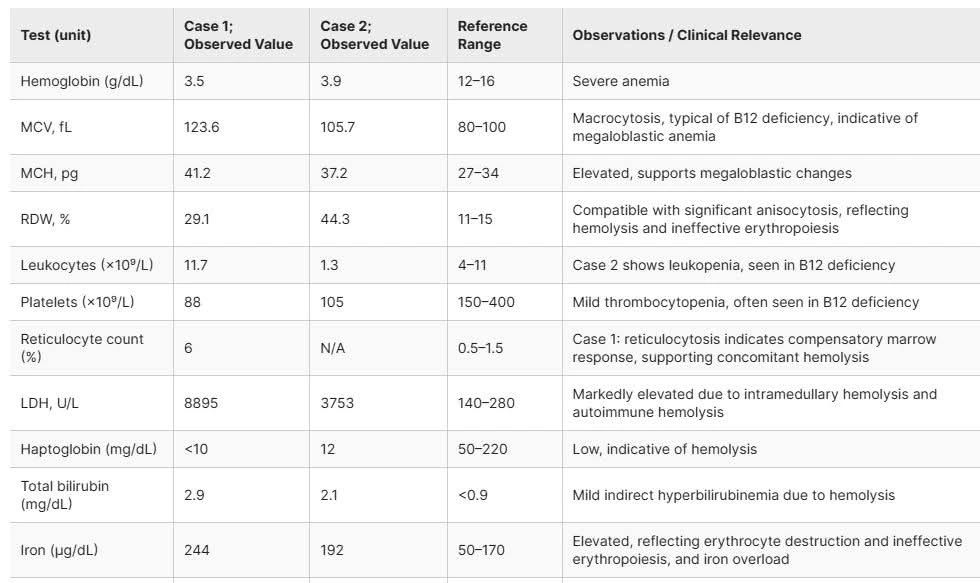
“A Rare Autoimmune Hemolytic Overlap: Coombs-Positive Pernicious Anemia.
Pernicious anemia is an autoimmune disorder characterized by the presence of anti–parietal cell antibodies and/or anti–intrinsic factor antibodies, leading to impaired vitamin B12 absorption in the terminal ileum.
Vitamin B12 deficiency results in ineffective erythropoiesis, which causes intramedullary hemolysis. This process is typically associated with elevated lactate dehydrogenase (LDH), reduced haptoglobin levels, and occasional indirect hyperbilirubinemia, even in the absence of immune-mediated red blood cell destruction. In such cases, the direct antiglobulin (Coombs) test is usually negative.
In contrast, true autoimmune hemolytic anemia (AIHA) is characterized by extravascular hemolysis mediated by autoantibodies—most commonly IgG with or without complement (C3)—directed against red blood cell surface antigens. These antibodies lead to opsonization and subsequent phagocytosis of erythrocytes by the reticuloendothelial system, resulting in a positive direct Coombs test.
The coexistence of pernicious anemia and Coombs-positive AIHA is rare but has been described in a limited number of case reports. This overlap likely reflects a broader immune dysregulation, in which the autoimmune process extends beyond gastric parietal cells to involve erythrocyte antigens.
Laboratory evaluation can help distinguish between hemolysis due to cobalamin deficiency and concomitant AIHA. In isolated vitamin B12 deficiency, the reticulocyte count is typically low or inappropriately normal due to ineffective erythropoiesis, and the peripheral blood smear shows macro-ovalocytes and hypersegmented neutrophils. In contrast, AIHA is associated with an elevated reticulocyte count and may demonstrate spherocytes on the peripheral smear.
Therapeutic response also provides important diagnostic insight. Correction of anemia and hemolysis with vitamin B12 replacement alone supports intramedullary hemolysis secondary to cobalamin deficiency. However, persistent hemolysis or the need for immunosuppressive therapy, such as corticosteroids, suggests the presence of true AIHA.
Pernicious anemia is frequently associated with other autoimmune conditions, including autoimmune thyroid disease, type 1 diabetes mellitus, vitiligo, and Addison disease. The presence of AIHA in this setting is consistent with this pattern of autoimmune clustering and underscores the importance of considering concurrent immune-mediated disorders in affected patients.”
Explore hematology with Tareq Abadl on Hemostasis Today.
-
Oct 12, 2026, 13:58Francisco Chacón-Lozsán: Catastrophic Antiphospholipid Syndrome A Rapidly Progressive Multiorgan Thrombotic Emergency
-
Oct 12, 2026, 12:50Nawsherwan Mohammad: Study Examines Thrombotic Events in Patients with Polycythemia Vera in Iraq
-
Oct 12, 2026, 12:30Chanakya Nayudu: Looking Beyond Blood Clots – Patient-Reported Outcomes in Antiphospholipid Syndrome
-
Oct 12, 2026, 12:12Jean-Jacques Kiladjian: Improving Treatment Strategies with JAK Inhibitors in Myelofibrosis
-
Oct 12, 2026, 12:04Chloe Homich: AABB Annual Meetings – Building Connections and Advancing Transfusion Medicine
-
Oct 12, 2026, 11:51Daniel Sop: Sickle Cell Research Takes Center Stage at ASCAT 2026
-
Oct 12, 2026, 10:36PAI-1 Inhibition as a New Strategy for Enhancing Fibrinolysis and Clot Resolution
-
Oct 12, 2026, 07:39Emmanuel J Favaloro: 100 Years of von Willebrand Disease and the Importance of Local Diagnosis and Management
-
Oct 12, 2026, 07:39Post-Stroke Fatigue Trajectories – 38% Recovered at 12 Months, While 16% Developed New Fatigue – International Journal of Stroke