


Heghine Khachatryan: Reversible Causes of Dementia from a Hematologic Perspective
Heghine Khachatryan, Editor-in-Chief of Hemostasis Today, Head of Hemophilia and Thrombosis Center at Yeolyan Hematology and Oncology Center, shared a post on LinkedIn:
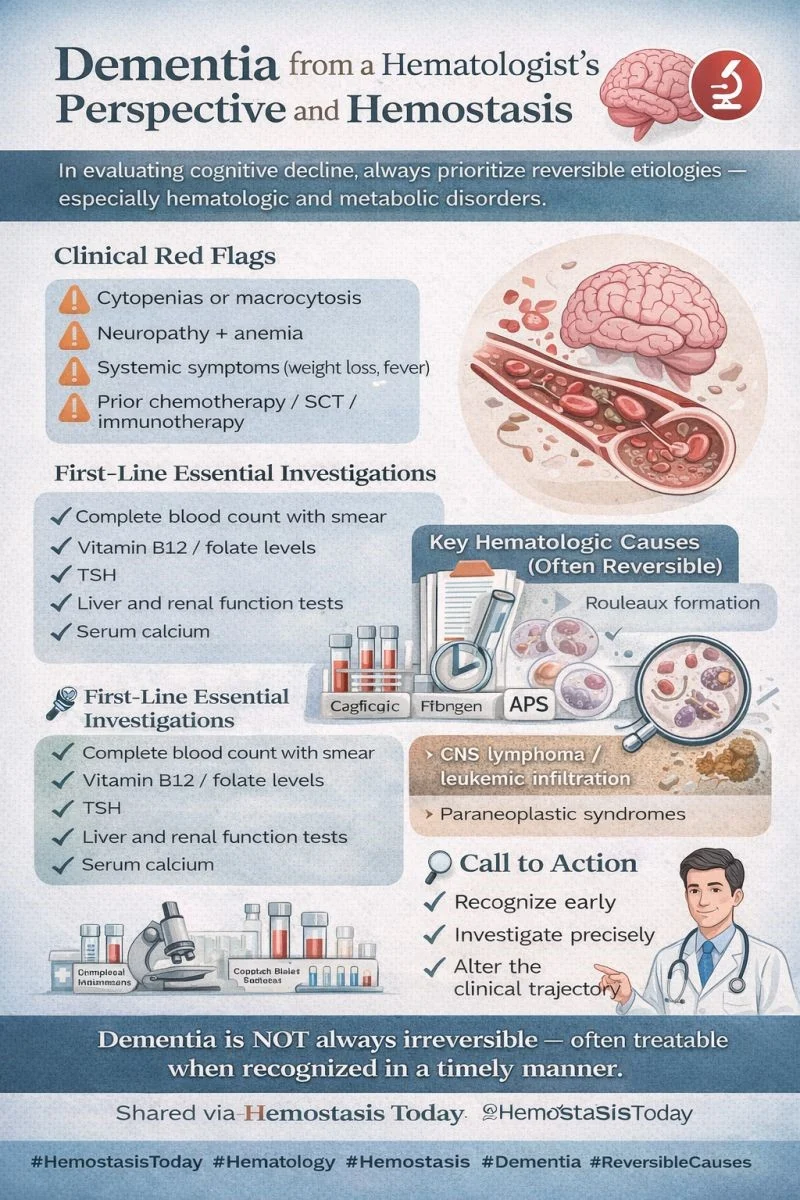
“Dementia from a Hematologist’s Perspective: The Critical Importance of Identifying Reversible Causes
In contemporary clinical practice, it is increasingly evident that the evaluation of cognitive impairment must systematically prioritize the exclusion of reversible etiologies, particularly those related to hematologic and metabolic disorders.
A hematology-informed approach is essential not only for accurate differential diagnosis, but also for meaningful improvement in patient outcomes and quality of life.
Clinical red flags suggesting hematologic etiology
- Cytopenias or macrocytosis
- Neuropathy in combination with anemia
- Systemic symptoms (weight loss, fever)
- History of chemotherapy, stem cell transplantation, or immunotherapy
First-line essential investigations
- Complete blood count with peripheral smear
- Vitamin B12 and folate levels
- Thyroid-stimulating hormone (TSH)
- Liver and renal function tests
- Serum calcium
Key hematologic causes (often reversible)
- Vitamin B12 deficiency – cognitive impairment plus neuropathy ± pancytopenia
- Folate deficiency – cognitive decline plus macrocytosis
- Iron deficiency – fatigue and impaired cognition
- Copper deficiency – myeloneuropathy plus cytopenias
- Zinc excess – secondary copper deficiency
- Hyperviscosity syndromes (Waldenström macroglobulinemia, multiple myeloma) – confusion, visual disturbances
- CNS lymphoma / leukemic infiltration
- Paraneoplastic syndromes
Peripheral smear as a diagnostic clue
- Macro-ovalocytes plus hypersegmented neutrophils – B12/folate deficiency
- Rouleaux formation – myeloma / hyperviscosity
- Blasts – leukemia
Targeted workup (when indicated)
- Serum protein electrophoresis with or without free light chains
- Vitamin B12 with or without methylmalonic acid / homocysteine
- Copper levels (in unexplained cytopenia or neuropathy)
Clinical take-home message
Dementia is not invariably irreversible.
In a substantial proportion of cases, it may represent a manifestation of underlying hematologic or metabolic disorders, which are partially or fully reversible when identified in a timely manner.
The role of the hematologist
Our responsibility extends beyond diagnosis — it is to recognize early, investigate precisely, and alter the clinical trajectory of our patients.”
Other posts featuring Heghine Khachatryan on Hemostasis Today.
-
Oct 6, 2026, 10:15Zeeshan Ali Baig: AI-Designed Peptide for Rare Bleeding Disorder
-
Oct 6, 2026, 10:12Srivatsan Rangachari: Stem Cell Transplant for 12-Year-Old with Fanconi Anaemia
-
Oct 6, 2026, 09:56Anitha Narayanamurthy: A Possible Missing Link in Unexplained Blood Test Abnormalities
-
Oct 6, 2026, 09:46Francois Roubille: Biomarkers and Long-Term Prognosis After Revascularised STEMI
-
Oct 6, 2026, 09:20EAS Rare Lipid Disorder Course – Advancing Lipid Disorder Education – European Atherosclerosis Society
-
Oct 6, 2026, 09:12Fionnuala Ní Áinle: Lisa Ryan’s First Thrombocalc VTE Research Report
-
Oct 6, 2026, 09:02David McIntosh: Preventable Maternal and Newborn Deaths – The Urgent Need for Action
-
Oct 6, 2026, 08:55Konstantin Yenkoyan: CAR-T, GLP-1 or Orexin – Who Will Take the 2026 Nobel?
-
Oct 6, 2026, 08:39Emily Bury: Putting Patients at the Centre of VTE Care