


Edward Lee Carter: NOTION-4 – HALT and Clinical Outcomes
Edward Lee Carter, Clinical Pharmacist Practitioner at U.S. Department of Veterans Affairs, shared on LinkedIn:
“A valve can look better on CT without a patient feeling better.
That question is at the center of NOTION-4, a randomized trial of antithrombotic therapy after TAVR in patients without another indication for oral anticoagulation.
Researchers compared single antiplatelet therapy (SAPT) with a DOAC for 3 months, followed by SAPT.
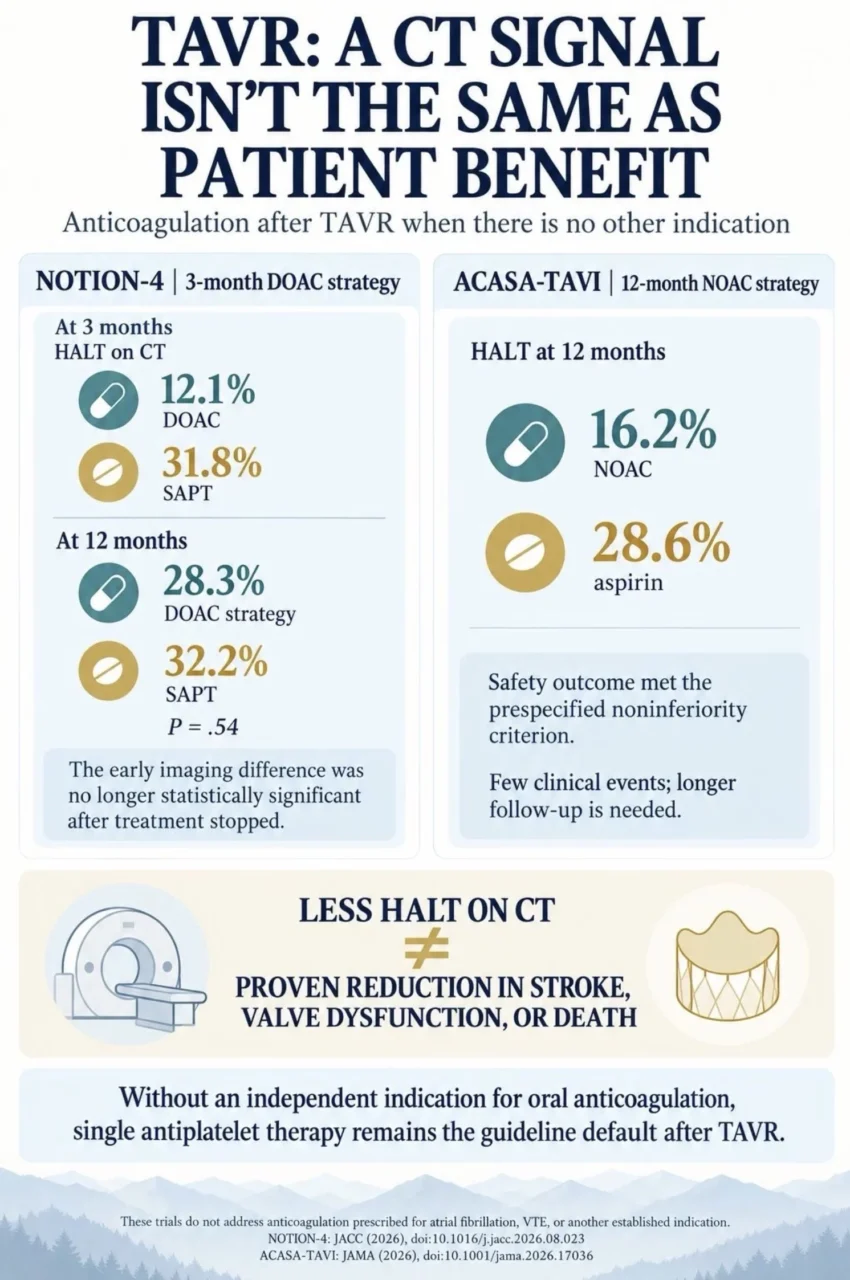
At 3 months, hypoattenuated leaflet thickening (HALT)—a CT finding associated with subclinical leaflet thrombosis-was seen in 12.1% of the DOAC group versus 31.8% with SAPT.
The primary endpoint was HALT at 12 months. By then, 9 months after the DOAC had stopped, rates were 28.3% versus 32.2% (P equal to .54).
The early imaging difference was no longer statistically significant.
The trial did not establish that reducing HALT improves stroke risk, valve function, or survival.
At 12 months, the composite of death, stroke, or major/life-threatening bleeding occurred in 8.2% with the DOAC strategy versus 2.3% with SAPT.
This difference favored SAPT, but the trial was small and event numbers were limited.
It is a safety signal to consider-not a precise estimate of harm or proof about any individual outcome.
A separate trial, ACASA-TAVI, tested 12 months of DOAC monotherapy and also found less HALT at one year (16.2% vs 28.6%).
Its composite safety outcome met the prespecified noninferiority criterion.
These were separate trials with different designs and treatment durations, so we cannot conclude that duration explains their different results.
Neither trial shows that less HALT leads to better long-term outcomes for patients.
The clinical question is specific: should anticoagulation be added solely to prevent a CT finding in someone with no other indication?
Current guidelines favor single antiplatelet therapy after TAVR in that setting.
This does not challenge anticoagulation for atrial fibrillation when indicated by stroke risk, VTE, or another established reason.
Those decisions rest on the independent indication-not CT appearance alone.
A useful medication-stewardship reminder: a surrogate can respond to treatment without proving that the patient benefits.
How should future TAVR studies connect imaging findings with outcomes that matter to patients-stroke, bleeding, valve function, and survival?
The views expressed are my own and do not represent the Department of Veterans Affairs.”
Stay updated with Hemostasis Today.
-
Oct 5, 2026, 15:31Irma Bagdoniene: Multidisciplinary Management of High-Risk Familial Hypercholesterolaemia and CAD
-
Oct 5, 2026, 15:00Serena Williams and Pulmonary Embolism: From Personal Crisis to Lessons in Venous Thromboembolism
-
Oct 5, 2026, 14:55Marco Moscarelli: 3D Reconstruction Enhances Volumetric Assessment of Post-TAVI Thrombosis
-
Oct 5, 2026, 13:24Abdul Muqtadir Abbasi: Diagnostic Pearls for Evaluating Isolated Thrombocytopenia in Residents
-
Oct 5, 2026, 13:16Katerina Pavenski: Rethinking What ‘Normal’ Means for Iron Deficiency
-
Oct 5, 2026, 13:09Rick Matthews: Balancing Established VTE Partnerships with Innovative Interventional Technologies
-
Oct 5, 2026, 13:01Nawsherwan Mohammad: Recognizing TTP Before the ADAMTS13 Result Arrives
-
Oct 5, 2026, 12:51Bruno Pougault: The Hidden Challenges Behind Anti Xa Testing
-
Oct 5, 2026, 12:41Syed Huzaifa Khan: Rethinking CTRP12 as a Biomarker for In Stent Restenosis