


Kristopher Jonas: The Ethical Case for Compensated Plasma Donation
Kristopher Jonas, Chief Executive Officer/President at Proesis Biologics, shared a post on LinkedIn:
“The U.S. pays plasma donors.
Is that ethical?
I’ve spent my career in source plasma, and I hear this question constantly; as recently as yesterday.
The honest answer is that the strongest case for compensation isn’t about industry economics.
It’s about two groups of people: donors and patients.
Start with patients.
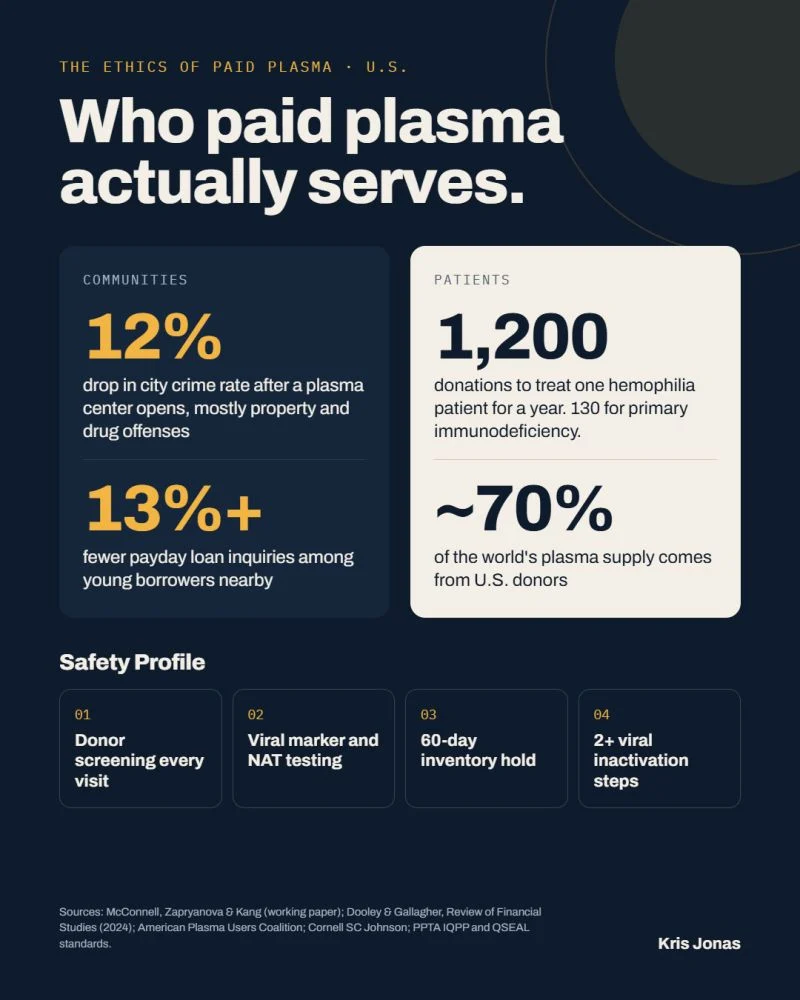
One patient with primary immunodeficiency needs about 130 donations a year.
Alpha-1 needs about 900. Severe hemophilia needs about 1,200. The U.S. supplies roughly 70% of the world’s plasma for these therapies, and no unpaid model anywhere has come close to meeting demand.
Remove compensation, and you don’t get a more ethical system.
You get rationing.
Now look at donors.
The usual objection is exploitation: compensation targets people under financial pressure.
That’s a fair concern, so look at what those donors would do otherwise.
A payday loan typically costs about 15% per two-week term.
CFPB data shows four out of five payday borrowers either roll over or default within a year, and most loans go to borrowers who end up paying more in fees than they borrowed.
That’s a debt trap.
Research in the Review of Financial Studies (Dooley and Gallagher, 2024) found that when a plasma center opens nearby, payday loan demand among young borrowers falls by more than 13%, and local store traffic rises.
A separate study (McConnell, Zapryanova and Kang) found that a plasma center opening is associated with a 12% drop in a city’s crime rate, mostly property and drug offenses, with the effect strongest in lower-income areas.
Compensated donation doesn’t create financial hardship. It gives people facing it an option that doesn’t compound.
Safety is not an afterthought.
It’s layered.
Donors receive health screenings and vital checks at every visit, protein and hematocrit testing, periodic physicals, limits on donation frequency, and donor deferral registries that keep ineligible donors from participating.
For patients: every donation is tested for viral markers via nucleic acid testing.
Units then sit in a 60-day inventory hold so any donation from a donor who later tests positive can be pulled and destroyed.
Manufacturing then adds at least two dedicated viral inactivation or removal steps.
Industry standards (IQPP for collectors, QSEAL for manufacturers) sit on top of FDA requirements.
Where the ethics really live.
Compensation itself isn’t the ethical question.
How we treat donors is.
Fair pay, honest communication, respect in the center, and rigorous health monitoring are what separate a responsible system from an extractive one.
The research on long-term health of frequent donors is still thinner than it should be, and our industry should fund more of it.
Paid plasma, done right, keeps patients alive and gives donors a dignified alternative to predatory debt.
That’s worth defending and worth holding to a high standard.”
Stay updated with Hemostasis Today.
-
Oct 28, 2026, 03:19Arwa Z. Al-Riyami: Key Takeaways from the Blood Conference in Auckland
-
Oct 28, 2026, 03:09Amber Paratore Sanchez: Therapeutic Plasma Exchange in PTE Patients with Cold Agglutinins
-
Oct 28, 2026, 03:04Fonkou Steve: Overcoming Fear to Build a Lifelong Blood Donor
-
Oct 28, 2026, 03:00Joanne Marlor: NHS Blood and Transplant Opens Country’s Largest Donor Centre in Reading
-
Oct 27, 2026, 23:04Stefano Navarro: Hypertension Reprogrammes Megakaryocytes and Increases Platelet Responsiveness to Thrombin
-
Oct 27, 2026, 23:03Enrique M. San Norberto García: What Is the Best Treatment for Femoropopliteal in-Stent Restenosis
-
Oct 27, 2026, 23:01Mandy-Lyn Crispim: One Donation Can Help Save More Than One Life
-
Oct 27, 2026, 23:00Teresa Buzzoni: AABB 2026 Through the Eyes of a Newcomer to the Blood Industry
-
Oct 27, 2026, 22:59Josephine Cantu: The Incredible Science Behind Blood Clotting – A Life-Saving Process