

George Touma: ApoB Should Be Central to All Lipid Guidlines
George Touma, Interventional Cardiologist at St George Private Cardiology, shared a post on LinkedIn:
“ApoB Should Be Central to All Lipid Guidlines.
We have spent decades asking: ‘What is the LDL-C?’
The more important question is: ‘How many atherogenic particles are actually circulating?’
I learnt approximately 12 years from Dr Allan Snidermans pioneering paper that:
- LDL-C measures the amount of cholesterol carried within LDL particles.
- ApoB reflects the number of circulating atherogenic particles.
And there is essentially one ApoB molecule per atherogenic particle — LDL, IDL, VLDL remnants and Lp(a).
This is important because atherosclerosis is driven by the retention of atherogenic lipoprotein particles within the arterial wall, not by cholesterol existing in isolation.
Two patients can have exactly the same LDL-C and very different ApoB concentrations. Their cholesterol concentration may look identical. Their atherogenic particle burden is not.
This becomes particularly important in:
- metabolic syndrome and diabetes
- hypertriglyceridaemia
- obesity
- low HDL-C states
- patients with LDL-C or non-HDL-C discordance
- patients who have achieved an apparently ‘optimal’ LDL-C but retain substantial residual risk
We have confused what is convenient to measure with what is biologically most relevant to our patients. Unfortunately, guidelines continue to conflate these measures relying on LDL cholesterol targets
The future of lipid guidelines and management should be ApoB as the central underlying particle-based measure of atherogenic burden.
If our objective is to prevent atherosclerosis, particle number must be at the centre of the conversation.
So its perplexing to me why the 2026 ACC/AHA guideline did not specifically recognises that apoB must be central.
Because apoB is commonly reported in g/L in my country of Australia:
- 100 mg/dL is 1.00 g/L
- 80 mg/dL is 0.80 g/L
- 70 mg/dL is 0.70 g/L
- 65 mg/dL is 0.65 g/L
- 55 mg/dL is 0.55 g/L
The important point for secondary prevention in my patients, I target ApoB less than 0.65 g/L as my minimum target for very-high-risk ASCVD and ApoB less than 0.55 g/L as an aggressive target when residual risk is substantial.
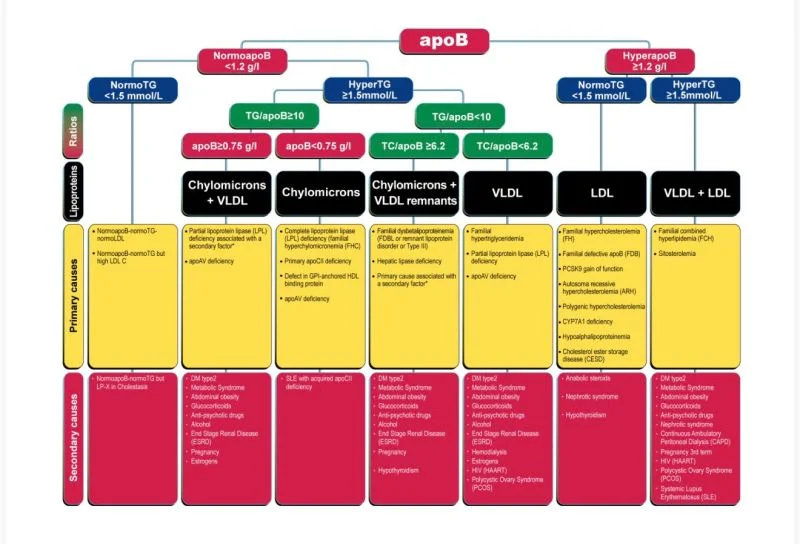
The following alogorithm from Dr Sniderman et al is all you need to diagnose and treat most clinically relevant hyperlipidemia.
Hope you find it useful. Please share it around.”
Stay updated with Hemostasis Today.
-
Sep 21, 2026, 20:55Christopher Robinson: Obstetric Risks Are Seen at the Extremes of Birthweight
-
Sep 21, 2026, 20:54Emicizumab for Refractory GI Bleeding in Myeloma-Associated Acquired VWD – JTH
-
Sep 21, 2026, 20:52Ross Baker: ASH 2026 Guidelines on Iron Deficiency in HMB and Bleeding Disorders
-
Sep 21, 2026, 20:50Rainer Kaiser: Genes and Signalling Pathways Implicated in Procoagulant Platelet Generation
-
Sep 21, 2026, 20:49Natalia Dovlatova: Celebrating Stan Heptinstall and His Legacy in Platelet Science
-
Sep 21, 2026, 20:48Norm Roulet: The Interaction of Pb and SARS-CoV-2 and Its Impact on the Cardiovascular System
-
Sep 21, 2026, 20:45Felix Scholkmann: The Spleen Plays a Key Role in Regulating Platelet Activity
-
Sep 21, 2026, 20:43Claire Pomeroy: Celebrating the 2026 Lasker Awards and Why Medical Research Matters
-
Sep 21, 2026, 20:42Fiona Robinson: Practical Information for People With Hemophilia and Inhibitors