


Alen Emmanuel Joshy/LinkedIn
Dec 20, 2025, 23:44
Alen Emmanuel Joshy: CT Brain in Intracranial Hemorrhage
Alen Emmanuel Joshy, MRI Technician at AKG Memorial Cooperative Hospital, shared on LinkedIn:
”CT Brain in Intracranial Hemorrhage
Technical and Protocol Points:
- Non-contrast CT (NCCT) is mandatory initially — contrast can obscure acute blood.
- Thin slices (≤5 mm, preferably 1–2 mm) improve detection of small bleeds.
- Bone window helps identify associated skull fractures.
- Repeat CT is crucial in deteriorating patients to assess bleed progression.
Density and Physics Insight:
- Acute blood appears hyperdense (60–80 HU) due to high protein and iron content.
- Density reduces over time due to clot lysis and dilution by CSF.
- Hematocrit level influences bleed conspicuity on CT.
Evolution of Hemorrhage on CT:
- Hyperacute (<6 hrs): May appear heterogeneous due to active bleeding (“swirl sign”)
- Acute (6 hrs–3 days): Homogeneously hyperdense
- Early chronic: Peripheral membrane formation may be seen
Signs Suggesting Active or Severe Bleed:
- Swirl sign: Hypodense area within hyperdense clot → ongoing bleeding
- Spot sign (on CTA): Predictor of hematoma expansion
- Mass effect disproportionate to bleed size
Important Secondary Effects:
- Raised intracranial pressure (ICP)
- Herniation (subfalcine, transtentorial, tonsillar)
- Acute obstructive hydrocephalus (especially with IVH or SAH)
Etiology Clues Based on Location:
- Basal ganglia bleed: Hypertension
- Lobar hemorrhage: Amyloid angiopathy, tumor, anticoagulation
- Cerebellar bleed: Life-threatening due to brainstem compression
- Temporal lobe bleed: Consider trauma or aneurysmal SAH extension
When to Add CT Angiography?
- Suspected aneurysm or AVM
- Young patient with no hypertension
- Lobar hemorrhage without trauma
- SAH with negative NCCT after 6 hours
Pitfalls and Mimics on CT:
- Calcifications vs acute bleed
- Beam-hardening artifacts
- Contrast staining post-procedure
- Dense venous sinuses mimicking SAH
Clinical Correlation Matters:
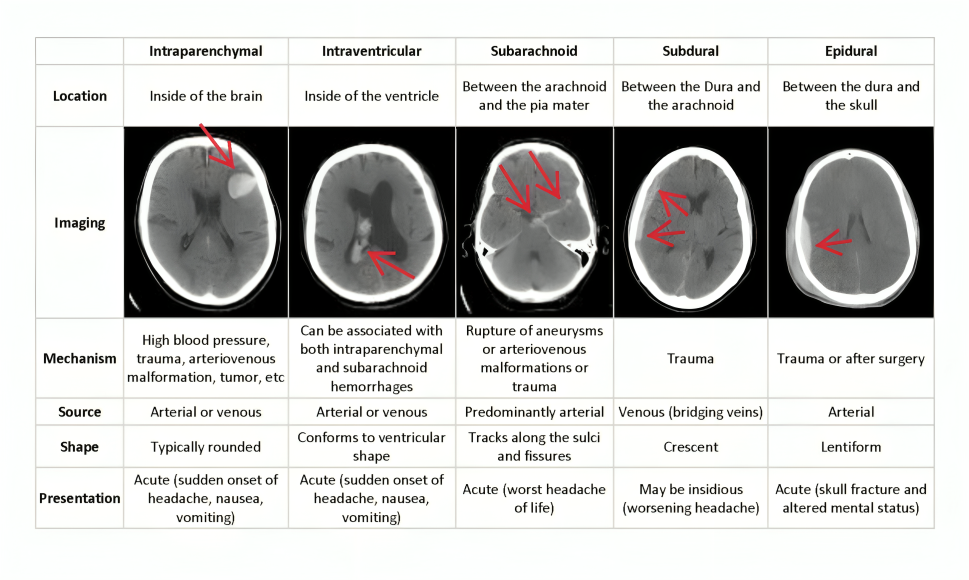
- Sudden severe headache → rule out SAH
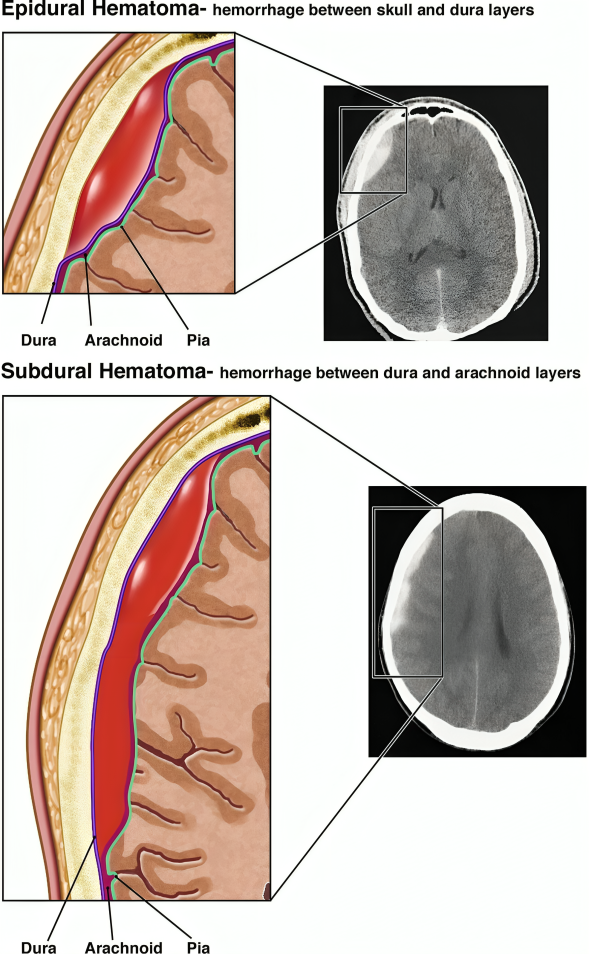
- Trauma with lucid interval → EDH
- Elderly with minor trauma → SDH
- Anticoagulated patients → high risk of expansion
Take-Home Message:
- CT brain not only detects hemorrhage but also predicts severity, guides management, and helps identify the cause. Early recognition saves lives.”

Stay informed with Hemostasis Today.
-
Oct 7, 2026, 16:44Amor Salah: 2026 NCS/SCCM Guidelines for Managing Antithrombotic-Associated ICH
-
Oct 7, 2026, 16:04NETs in Thrombosis: From Mechanism to Therapeutic Target
-
Oct 7, 2026, 15:28Amir Samimi: Prognostic Value of Platelet Count in Resected HNSCC
-
Oct 7, 2026, 15:21Eloïse Laouenan: Bridging Immunity and Thrombosis in MVTE
-
Oct 7, 2026, 15:10Uthra Sundaram: Honouring Donors During International Plasma Awareness Week
-
Oct 7, 2026, 15:04Daniel Victor Ortigoza: Should Frail Older Patients With AF Switch From VKA to DOACs?
-
Oct 7, 2026, 14:53Susan Noone: Donor Turned Recipient Shares Lifesaving Transfusion Story
-
Oct 7, 2026, 14:49Aimee Burtenshaw: The Impact of the Infected Blood Inquiry on Hospital Transfusion Laboratories
-
Oct 7, 2026, 14:41Vikash Jaiswal: Does Timing Matter for Calcium in Pre-Eclampsia Prevention?