


Heparin and Warfarin in Pregnancy
Samwel Mikaye, CEO of SaMik Medical Center, posted on LinkedIn:
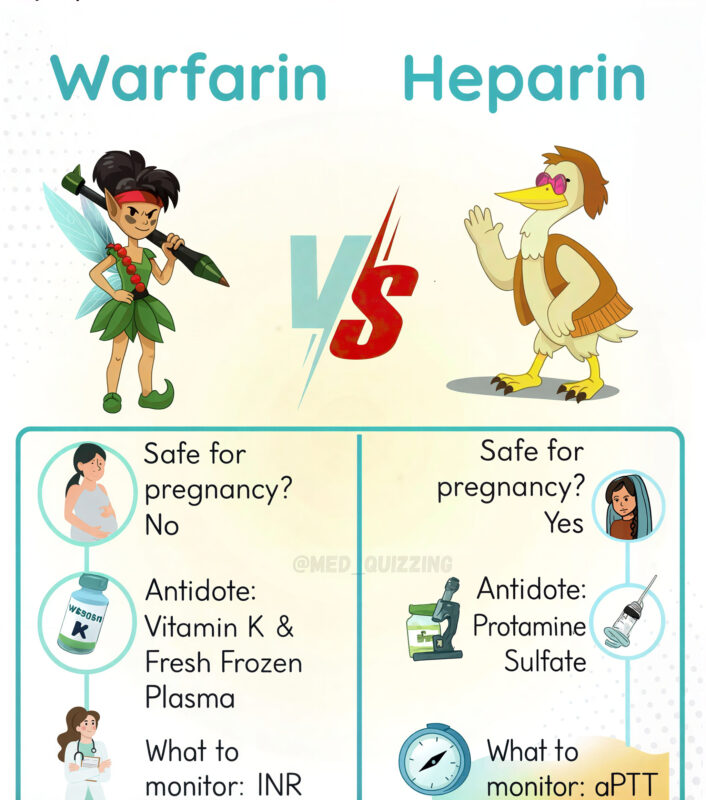
”HEPARIN AND WARFARIN IN PREGNANCY
Anticoagulation may be necessary in pregnancy for conditions like mechanical heart valves, thrombophilia, or previous thromboembolism.
Key principle: Choose an anticoagulant that protects the mother without harming the fetus.
1. HEPARIN
Types
• Unfractionated heparin (UFH)
• Low molecular weight heparin (LMWH) – e.g., Enoxaparin, Dalteparin
Safety
• Does NOT cross the placenta → safe for the fetus
• Preferred anticoagulant in pregnancy, especially in the first trimester
Administration
• UFH: Subcutaneous or IV, frequent monitoring (aPTT)
• LMWH: Subcutaneous, fixed or weight-based dosing, less monitoring needed
Adverse Effects
• Maternal bleeding
• Heparin-induced thrombocytopenia (HIT) – rare with LMWH
• Osteoporosis (with prolonged UFH use)
2. WARFARIN
Safety
• Crosses the placenta → teratogenic
• Avoid in the first trimester due to risk of warfarin embryopathy (nasal hypoplasia, limb defects)
• Risk of fetal bleeding and CNS abnormalities in later trimesters
When Warfarin May Be Used
• In selected high-risk women with mechanical heart valves, after the first trimester, if benefits outweigh risks
• Usually switched to heparin during weeks 6–12, then back to warfarin until near delivery
Monitoring
• Maternal INR target: 2.0–3.0 (varies with valve type)
• Close fetal monitoring recommended
3. MANAGEMENT PRINCIPLES
• First trimester: Prefer LMWH or UFH
• Second trimester: Warfarin may be considered if necessary
• Near term: Switch back to heparin to reduce the risk of fetal bleeding at delivery
• Always coordinate with obstetrics and hematology
KEY POINTS
• Heparin (UFH or LMWH) is safe in all trimesters; does not cross placenta
• Warfarin is teratogenic, especially in the first trimester, and causes fetal bleeding
• Careful switching strategy is required for women with mechanical heart valves
• Close maternal and fetal monitoring is essential”
Stay updated with Hemostasis Today.
-
Sep 1, 2026, 09:16Nicolas Gendron: Real-World Data on Danaparoid in Patients with Suspected HIT
-
Sep 1, 2026, 08:24Cristina Chang: The Importance of The New ET Treatments
-
Sep 1, 2026, 07:22Abdul Mannan: ASH 2026 Guidelines – New Treatment Approach for Adult ITP
-
Sep 1, 2026, 07:20Alejandro González Veliz: Silent Atherosclerosis Starts Earlier Than We Think
-
Sep 1, 2026, 07:18Alan Nurden: A New Mechanism Behind Immune Thrombocytopenia
-
Sep 1, 2026, 07:18Susan Shea: New NHLBI Fellowship Supports Thrombinflammation Research
-
Sep 1, 2026, 07:12Sriraman Punniakoti: Pediatric ALL Therapy and Cerebrovascular Thrombosis
-
Sep 1, 2026, 07:04Piotr Czempik: ROTEM in Sepsis-Related Coagulopathy
-
Sep 1, 2026, 07:02Amin Omar Khlifat: Reading the Laboratory Clues to Differentiate Types of Anemia