


Robin Young: Complex PCI and the Challenge of Balancing Ischemic and Bleeding Risk
Robin Young, Chief Executive Officer at PearlDiver, Founder, Editor and Former Publisher at Orthopedics This Week, shared a post on LinkedIn:
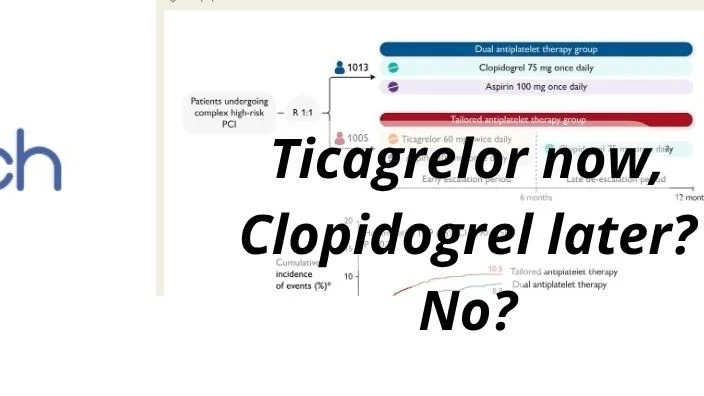
“A recent European Heart Journal randomized study examined the strategy of ‘early escalation, late de-escalation’ in an attempt to thread that needle in some of the highest-risk PCI patients cardiologists treat daily.
The result? Probably not what the authors hoped for.
Complex PCI patients live in two dangerous worlds simultaneously.
Anatomically, they harbor long lesions, bifurcations, left main disease, diffuse multivessel atherosclerosis, and, naturally and too often, diabetes.
Clinically, they are precisely the patients in whom both ischemic and bleeding events carry devastating consequences.
The intuitive solution has long been: deliver potent platelet inhibition when thrombotic risk is highest early after PCI, then ease off later once endothelial healing progresses and bleeding risk accumulates.
This study tested exactly that concept.
Investigators randomized 2,018 high-risk patients undergoing complex PCI to one of two strategies:
Tailored strategy:
- Early escalation with low-dose ticagrelor (60 mg twice daily) plus aspirin for less than 6 months, followed by late de-escalation to clopidogrel monotherapy after 6 months.
Conventional strategy:
- Standard dual antiplatelet therapy with clopidogrel plus aspirin for 12 months.
The primary endpoint was ambitious and clinically meaningful: a net adverse clinical event composite incorporating mortality, MI, stroke, stent thrombosis, urgent revascularization, and clinically relevant bleeding.
These patients were genuinely high risk:
- 22.6% underwent left main PCI
- 19.5% had complex bifurcation interventions
- 84.1% had diffuse long lesions
- 93.7% underwent multivessel PCI
- 36.7% had medically treated diabetes
The Results: elegant theory, unimpressive outcome
At 12 months, the tailored strategy failed to demonstrate superiority.
The primary endpoint occurred in:
- 10.5% of patients receiving tailored therapy
- 8.8% of patients receiving conventional DAPT
- Hazard ratio: 1.19
- 95% CI: 0.90–1.58
- P = 0.21
No signal of benefit, no statistical win, and certainly no practice-changing triumph.
To read the full review and analysis of this important trial, please go to The Research Coop‘s cardiology Substack page.
While you are there please do subscribe.
To Learn More about The Research COOP.
To Join The Research COOP.”
Stay updated with Hemsotasis Today.
-
Oct 5, 2026, 22:55Steve Humphreys: A Big Thank You to BSHT for Providing Me With a Recent Skills Exchange Award
-
Oct 5, 2026, 22:52William McKeown: Great to Be in Istanbul for the Opening of the EHC 2026
-
Oct 5, 2026, 22:48Laura Quintas Lorenzo: A New Approach to Healthcare for von Willebrand Disease at EHC 2026
-
Oct 5, 2026, 22:46Anas Zayad: Pleased to Share Our New Review on Thrombosis in SCD and Beta Thalassemia
-
Oct 5, 2026, 22:44Cihan Ay: Honouring Eric Kandel and Eugene Braunwald at the Medical University of Vienna
-
Oct 5, 2026, 22:42Heather L. Gornik: Testing for Aortic and Arterial Thrombosis at VSS 2026
-
Oct 5, 2026, 22:34Hasan Abbas Zaheer: Honoured to Have Co-Authored One of the Four Reviews in The Lancet Thalassemia Series
-
Oct 5, 2026, 22:34Kamyar Shameli: Understanding the Coagulation Cascade – How Anticoagulants Prevent Blood Clots
-
Oct 5, 2026, 22:31Risika Samanta: Pediatric ITP in a 12-year-old – An Atypical Presentation without a Viral Prodrome