


Alisha Tuck: Ultrasound and Anticoagulation Management in Pregnancy – Why Anticoagulation Matters?
Alisha Tuck, Obstetrics and Gynecology Sonographer at Sonopartners, LLC, shared a post on LinkedIn:
“Navigating the First Trimester: Ultrasound and Anticoagulation Management
The Physiological Context: Why Anticoagulation Matters
Pregnancy increases the risk of Venous Thromboembolism (VTE) by 4-5x .
For patients with conditions like Factor V Leiden, Protein C or S deficiency, or Antiphospholipid Syndrome (APS), the risk of pregnancy loss, placental abruption, and preeclampsia is significantly elevated.
Commonly prescribed anticoagulants in the first trimester include:
- Low-Molecular-Weight Heparin (LMWH): The gold standard (e.g., Enoxaparin) because it does not cross the placenta.
- Low-Dose Aspirin (LDA):Often used in conjunction with LMWH for APS.
- Warfarin: Generally avoided due to ‘Warfarin Embryopathy,’ though occasionally managed in patients with mechanical heart valves under strict supervision.
Key Sonographic Objectives in the First Trimester
When scanning a patient on anticoagulation, our focus shifts toward identifying early signs of pregnancy failure or maternal complications.
1. Confirming Viability and Dating
Accurate dating is paramount.
In patients with clotting disorders, placental insufficiency can manifest later; having a rock – solid CRL from the first trimester ensures that later growth restrictions are identified promptly.
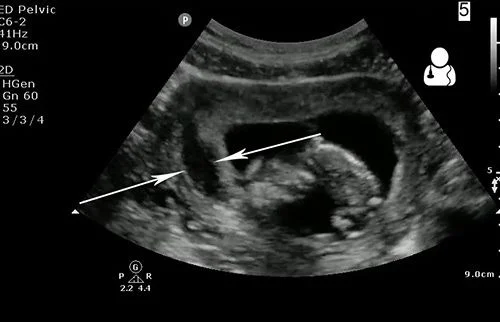
2. Identifying Subchorionic Hemorrhages (SCH)
Anticoagulation therapy can increase the incidence or size of subchorionic bleeds.
- Documentation: Measure the hematoma in three planes.
- Assessment: Note the volume relative to the gestational sac. A hematoma surrounding more than 50% of the sac carries a higher risk of pregnancy loss.
- Clinical Impact: Your report may lead the physician to ‘hold’ or adjust the dosage of anticoagulants.
3. Corpus Luteum and Adnexal Evaluation
Check for large corpus luteum cysts or evidence of internal hemorrhage.
While common, anticoagulated patients are at a slightly higher risk for hemorrhagic cysts, which can mimic ectopic pregnancy symptoms (pelvic pain).
Summary Checklist for the Sonographer
- Gestational Sac – Location, Shape, Mean Sac Diameter. Rule out ectopic; assess for ‘low implantation’
- Yolk Sac – Presence and Diameter. Early indicator of pregnancy health
- CRL – Best measurement of 3 | Critical for future growth monitoring
- Hematoma – Size (cm), Location, % of sac perimeter. Guides anticoagulant dosing adjustments
- Adnexa – Ovaries, free fluid, or masses. Rule out hemorrhage or secondary complications
Conclusion
Sonographers play a pivotal role in the multidisciplinary care of the high – risk obstetric patient.
By providing meticulous documentation of the early pregnancy and any associated perigestational bleeding, we allow the clinical team to tailor anticoagulation therapy – optimizing the safety of both the mother and the developing embryo.”
Stay updated with Hemostasis Today.
-
Oct 19, 2026, 16:36Christopher Pittman: Blood Clot Prevention Cannot End at Hospital Discharge
-
Oct 19, 2026, 16:13Javier M. Floren: When Immune Cells Move With Their Environment
-
Oct 19, 2026, 16:04Hussnain Javaid: New EHA Guidelines for HbSC Disease Management
-
Oct 19, 2026, 15:50Deep Madkaiker: A New Academic Opportunity in Transfusion Medicine at ACTREC
-
Oct 19, 2026, 15:19Why Hematologists Should Care About Diminished Ovarian Reserve in SCD – ASH Education
-
Oct 19, 2026, 14:16Hyperfibrinolysis as an Underrecognized Cause of Bleeding
-
Oct 19, 2026, 13:36Shobhna Ladva: Aspen Pharma EME Raises Awareness of Blood Clot Risks During Hormonal Transitions
-
Oct 19, 2026, 13:11Giulia Furnari: Connecting With Global Hematology Experts at IACH 2026
-
Oct 19, 2026, 12:46Andrew Choong: Recognizing Thrombosis Before It Becomes Life-Threatening