


Pooja Choradia: 2026 Acute Pulmonary Embolism Clinical Guidelines
Pooja Choradia, Critical Care Associate at P.D. Hinduja Hospital Khar, shared a post on LinkedIn:
“2026 AHA/ACC Pulmonary Embolism (PE) Clinical Categories
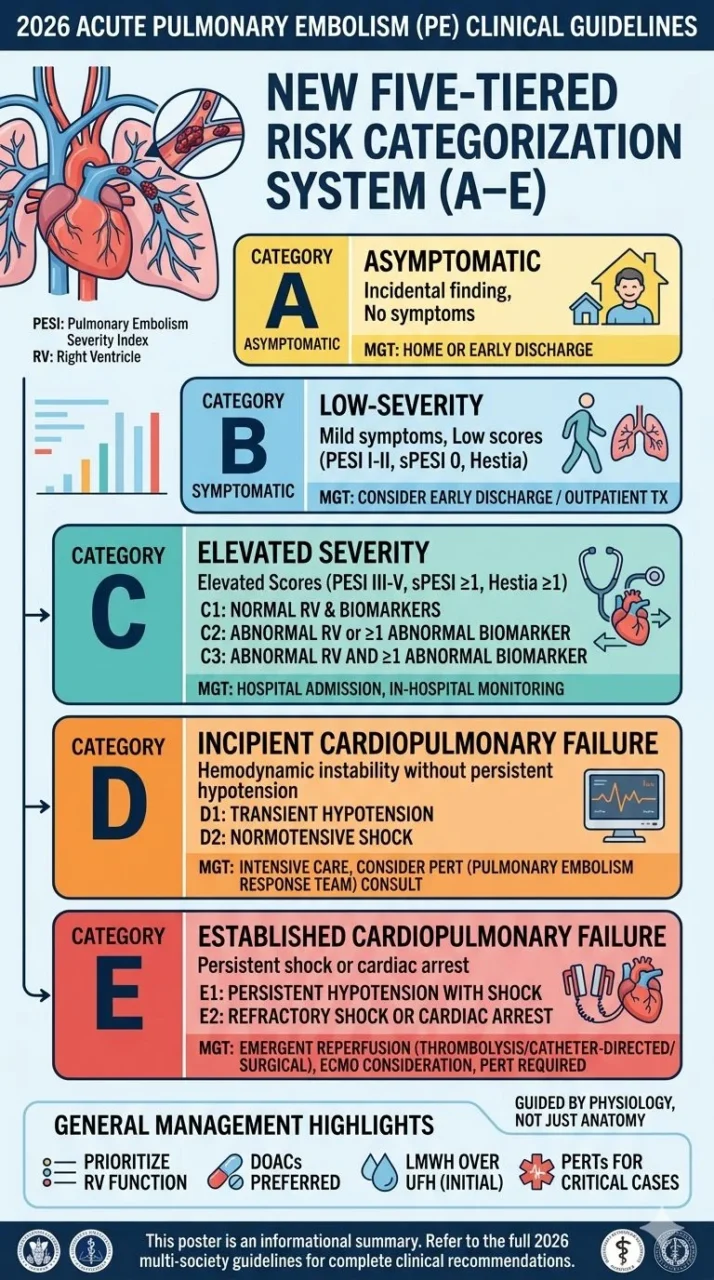
The 2026 guidelines transition from a binary risk model to a nuanced five-tiered (A–E) classification system, focusing on hemodynamic stability and physiological markers to guide patient management.
Category A: Asymptomatic PE
- Defined as an incidental finding.
- The patient is entirely asymptomatic.
- Typically safe for emergency department discharge.
Category B: Symptomatic, Low-Severity
- The patient is symptomatic but exhibits low clinical severity.
- Based on low-risk clinical assessment tools (e.g., PESI/sPESI or Hestia criteria).
- Early hospital discharge is generally recommended.
Category C: Elevated Severity
Characterized by an elevated clinical severity score (PESI III–V, sPESI ≥1, or Hestia ≥1).
- C1: Normal right ventricular (RV) function and normal biomarkers.
- C2: Abnormal RV function or ≥1 abnormal biomarker.
- C3: Abnormal RV function AND ≥1 abnormal biomarker.
Category D: Incipient Cardiopulmonary Failure
The patient is showing signs of hemodynamic deterioration.
- D1: Transient hypotension.
- D2: Normotensive shock.
Category E: Established Cardiopulmonary Failure
Representing severe, persistent physiological failure.
- E1: Persistent hypotension accompanied by cardiogenic shock.
- E2: Refractory cardiogenic shock or cardiac arrest.
Management Highlights:
Physiological Focus: Management is driven by RV function and physiological stability rather than the anatomical clot burden.
Anticoagulation:
Direct Oral Anticoagulants (DOACs) are strongly prioritized for eligible patients.
Low-Molecular-Weight Heparin (LMWH) is preferred over Unfractionated Heparin (UFH) for initial therapy.
Extended treatment is recommended for patients with unprovoked PE or persistent risk factors.
Advanced Interventions: Therapies such as systemic thrombolysis, catheter-directed thrombolysis, mechanical thrombectomy, and surgical embolectomy are considered reasonable for Category E1 and selected Category D patients.
Systemic Care: Multidisciplinary Pulmonary Embolism Response Teams (PERTs) are recommended to streamline coordinated care.
Post-PE Surveillance: Formal screening for chronic thromboembolic pulmonary disease (CTEPD) and functional limitations is recommended for at least one year following the event.”
Stay updated with Hemostasis Today.
-
Oct 20, 2026, 16:51Suzan Nakasendwa: A Growing Stroke Challenge in Uganda
-
Oct 20, 2026, 16:38Steve Moon: How Does Smoking Cessation Duration Affect Ischemic Stroke Risk
-
Oct 20, 2026, 16:25Cedrice Mentor: Reducing Platelet Wastage Through Cold Storage
-
Oct 20, 2026, 16:09Thirunavukkarasu Angappan: Can a Purified Fibrinogen Concentrate Replace Cryoprecipitate
-
Oct 20, 2026, 16:01Kalyan Roy: Platelet Conservation Through Evidence-Based Transfusion Practice
-
Oct 20, 2026, 15:28Stacy E. Croteau: 33 Countries, One Mission – Better Bleeding Disorder Care
-
Oct 20, 2026, 15:19Teresa Barnes: What Does a Pulmonary Embolism Mean for Jalen Hurts?
-
Oct 20, 2026, 15:04Laura S.: Could Speaking Up Prevent Maternal Deaths from Thrombosis?
-
Oct 20, 2026, 14:44Pete Stibbs: VTE in Professional Athletes – When Fitness Is Not Enough