


Pall T Onundarson: Improving Warfarin Outcomes Through Better Monitoring Strategies
Pall T Onundarson, Professor Emeritus of Hematology at University of Iceland, shared a post on LinkedIn:
“What does ‘As good as or better than Warfarin’ mean?
I’m heading to the ISTH 2026 meeting in Paris and wonder whether warfarin and its monitoring will be mentioned at all – or dismissed.
The medical community has largely accepted that DOACs are as good as – or better than ‘warfarin’ for most patients with non-valvular atrial fibrillation (NVAF), particularly because of lower rates of intracranial bleeding and greater convenience.
Consequently, most NVAF (and VTE) patients in the West now receive DOACs rather than warfarin.
But DOACs are inferior to warfarin in patients with MHV, RHD, APLS and frail elderly with AF.
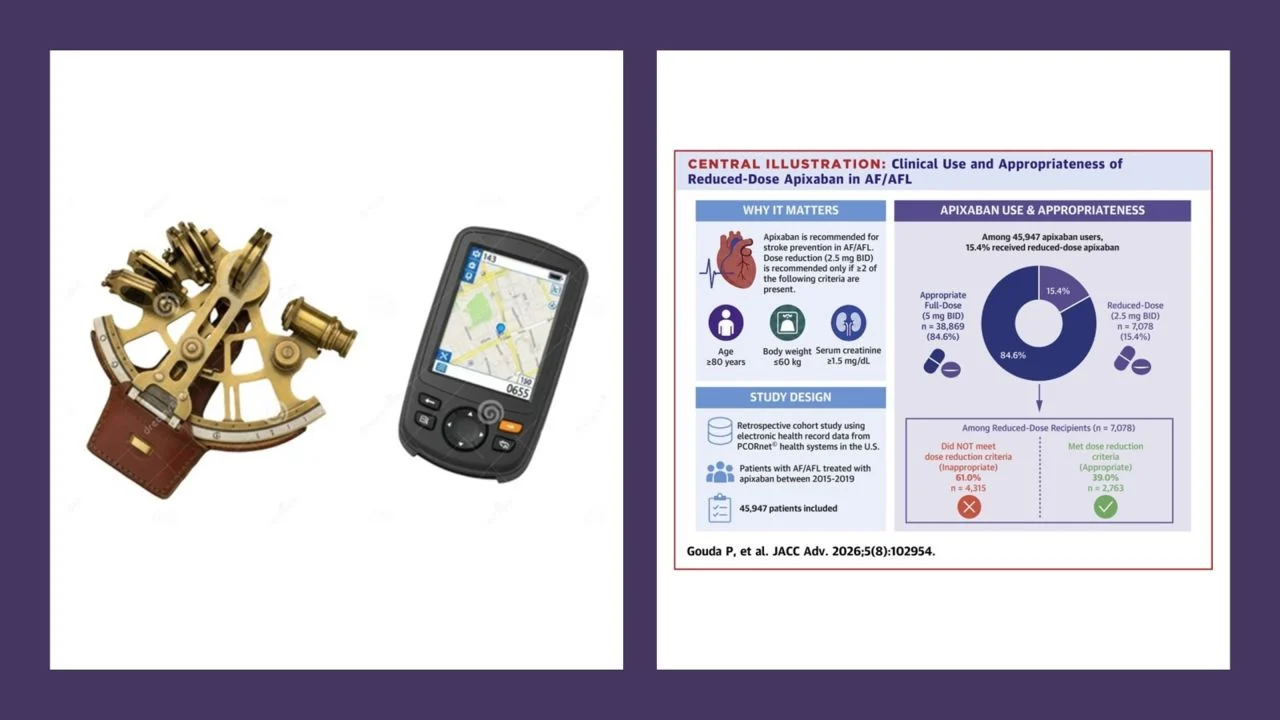
At the same time, studies suggest that DOACs are often dosed inappropriately in routine practice (see figure), potentially reducing the benefits seen in the pivotal trials.
So why is the same question not asked of warfarin?
What exactly is ‘warfarin’ in these trials?
In reality, it is almost always warfarin monitored with the prothrombin time (PT/INR) – a suboptimal test for the purpose that contributes to anticoagulation instability by reacting to common substantial fluctuations in factor VII, which has a short half-life.
This can lead to unnecessary dose adjustments and poorer outcomes.
A better monitoring approach exists, yet it attracts little interest from the key opinion leaders who shape anticoagulation practice.
Shouldn’t that concern patients?
To me, ‘better than warfarin’ really means better than PT-monitored warfarin or PT-warfarin.
The blinded Fiix randomized trial, published in The Lancet Haematology in 2015, showed that eliminating the influence of factor VII and monitoring only factors II and X using the Fiix-test (Fiix-NR, not INR) reduced total thromboembolism by about 50 percent compared with PT-monitored warfarin during long-term warfarin management.
The benefit was seen both in the overall study population and in the NVAF subgroup, which comprised about 70 percent of participants.
Two subsequent real-world studies have supported these findings.
In other words: Warfarin can be improved.
PT-warfarin is different from Fiix-warfarin.
The monitoring reagent matters.
Just as DOACs require appropriate dosing to achieve their full benefit, so does warfarin.
Before dismissing warfarin, we should first ensure it is monitored with the best available test rather than relying on a 90-year-old assay that was not designed for monitoring.
Modern anticoagulation practice deserves modern navigation – and clinical studies that reflect that.”
Stay updated with Hemostasis Today.
-
Oct 12, 2026, 21:51Sam Botchey: Orthobiologics Are Advancing but the Evidence Must Keep Pace
-
Oct 12, 2026, 21:50Serum Vitamin D, Platelet Function, and Bleeding in Primary ITP – Platelets Journal
-
Oct 12, 2026, 21:30Nika Samadzadeh Tabrizi: Looking Forward to the PACeS Trial on Anticoagulation for POAF
-
Oct 12, 2026, 21:28Michael Megaly: Does Coronary Ectasia Affect Outcomes in Acute Coronary Syndromes?
-
Oct 12, 2026, 21:25Vitor Borin P. de Souza: Think Twice Before Anticoagulating an Isolated Subsegmental PE
-
Oct 12, 2026, 20:43Jazlyn A Selvasingh: Excited to Share Our Research at AAO-HNSF 2026 in Los Angeles
-
Oct 12, 2026, 20:31Natalia Kovtun: Higher Ferritin Cutoffs Now Define Iron Deficiency
-
Oct 12, 2026, 19:39Edward Loftus: Using Low-Dose Aspirin in Pregnant Women With IBD
-
Oct 12, 2026, 19:32Shruti Sachdeva: Strengthening the Fight against Anemia