


Mostafa Elshazly: ERS Has just Relesed 2026 Update on the Treatment of PAH
Mostafa Elshazly, Presidant of Arabic Association for Non Invasive Ventiltion at International Association Of Non-Invasive Ventilation and Professor at Kasr AlAiny School of Medicine, Cairo University, shared a post on LinkedIn:
“ERS has just relesed 2026 update on the treatment of PAH.
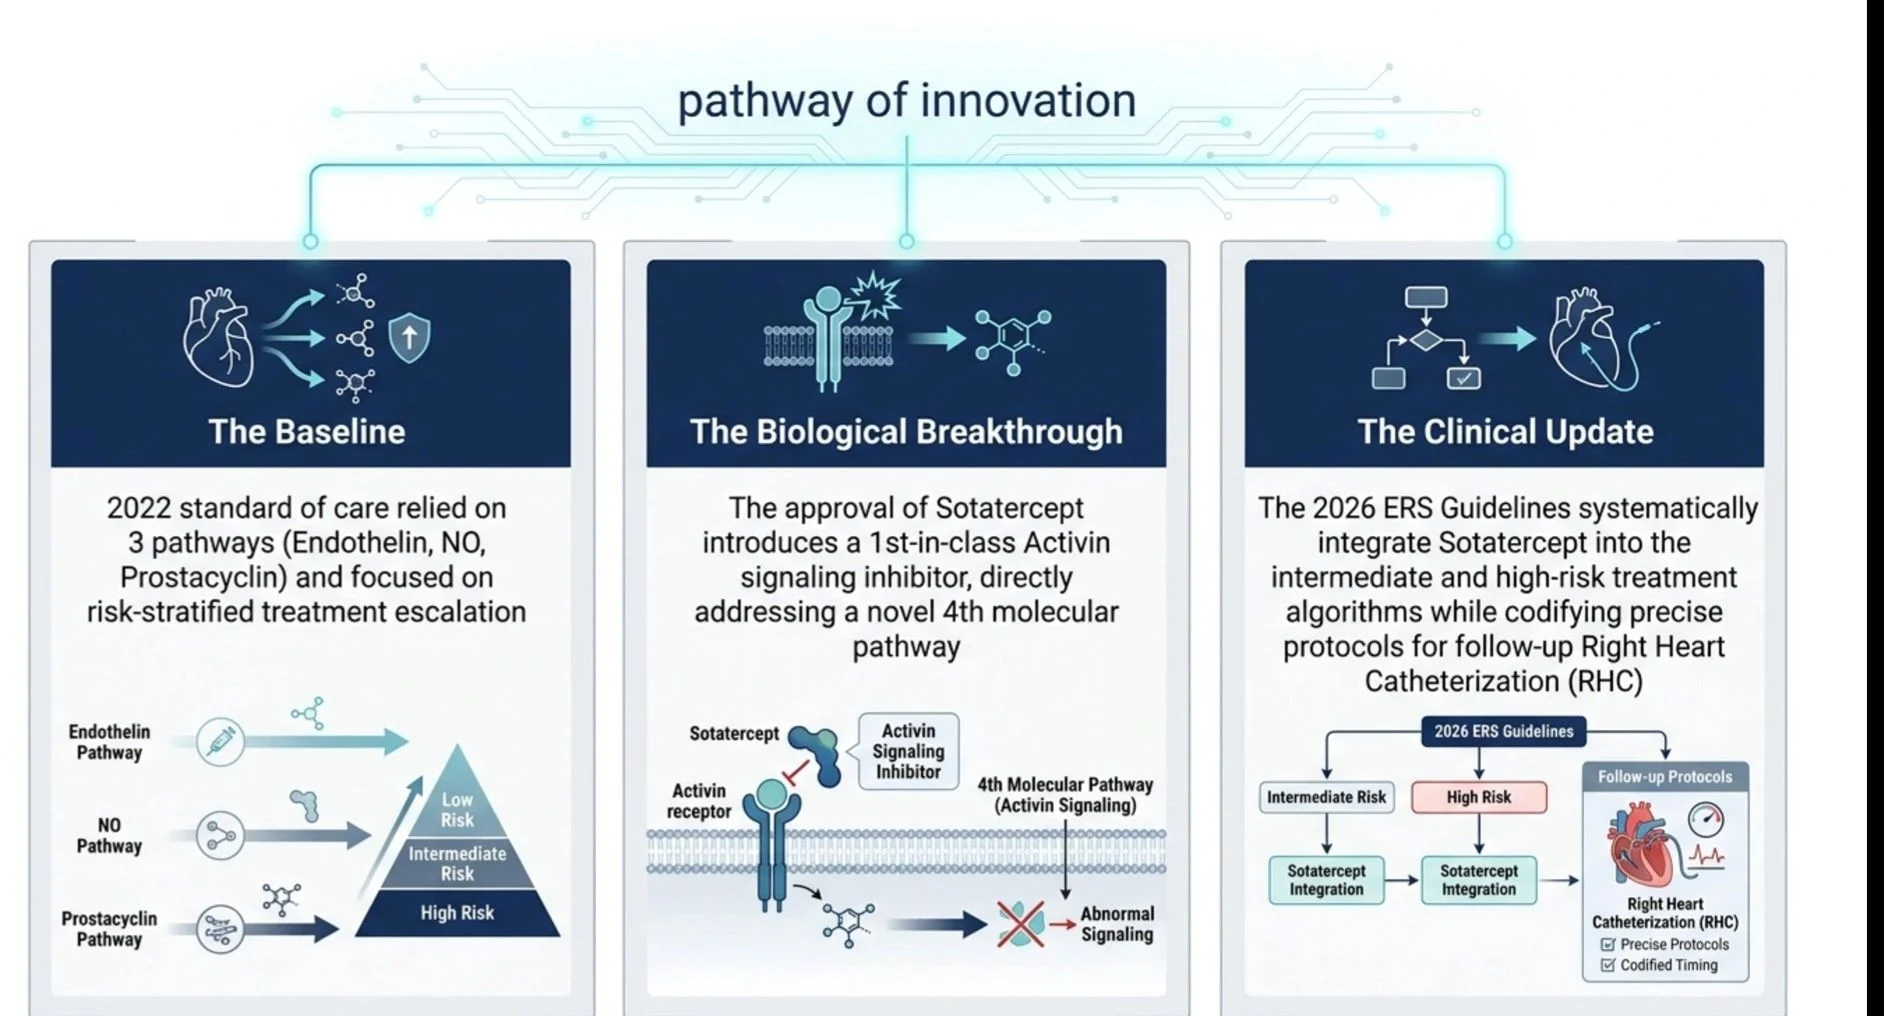
It is not a replacement for the 2022 ESC/ERS pulmonary hypertension guideline; rather, it complements the earlier guideline by addressing developments that were still emerging in 2022.
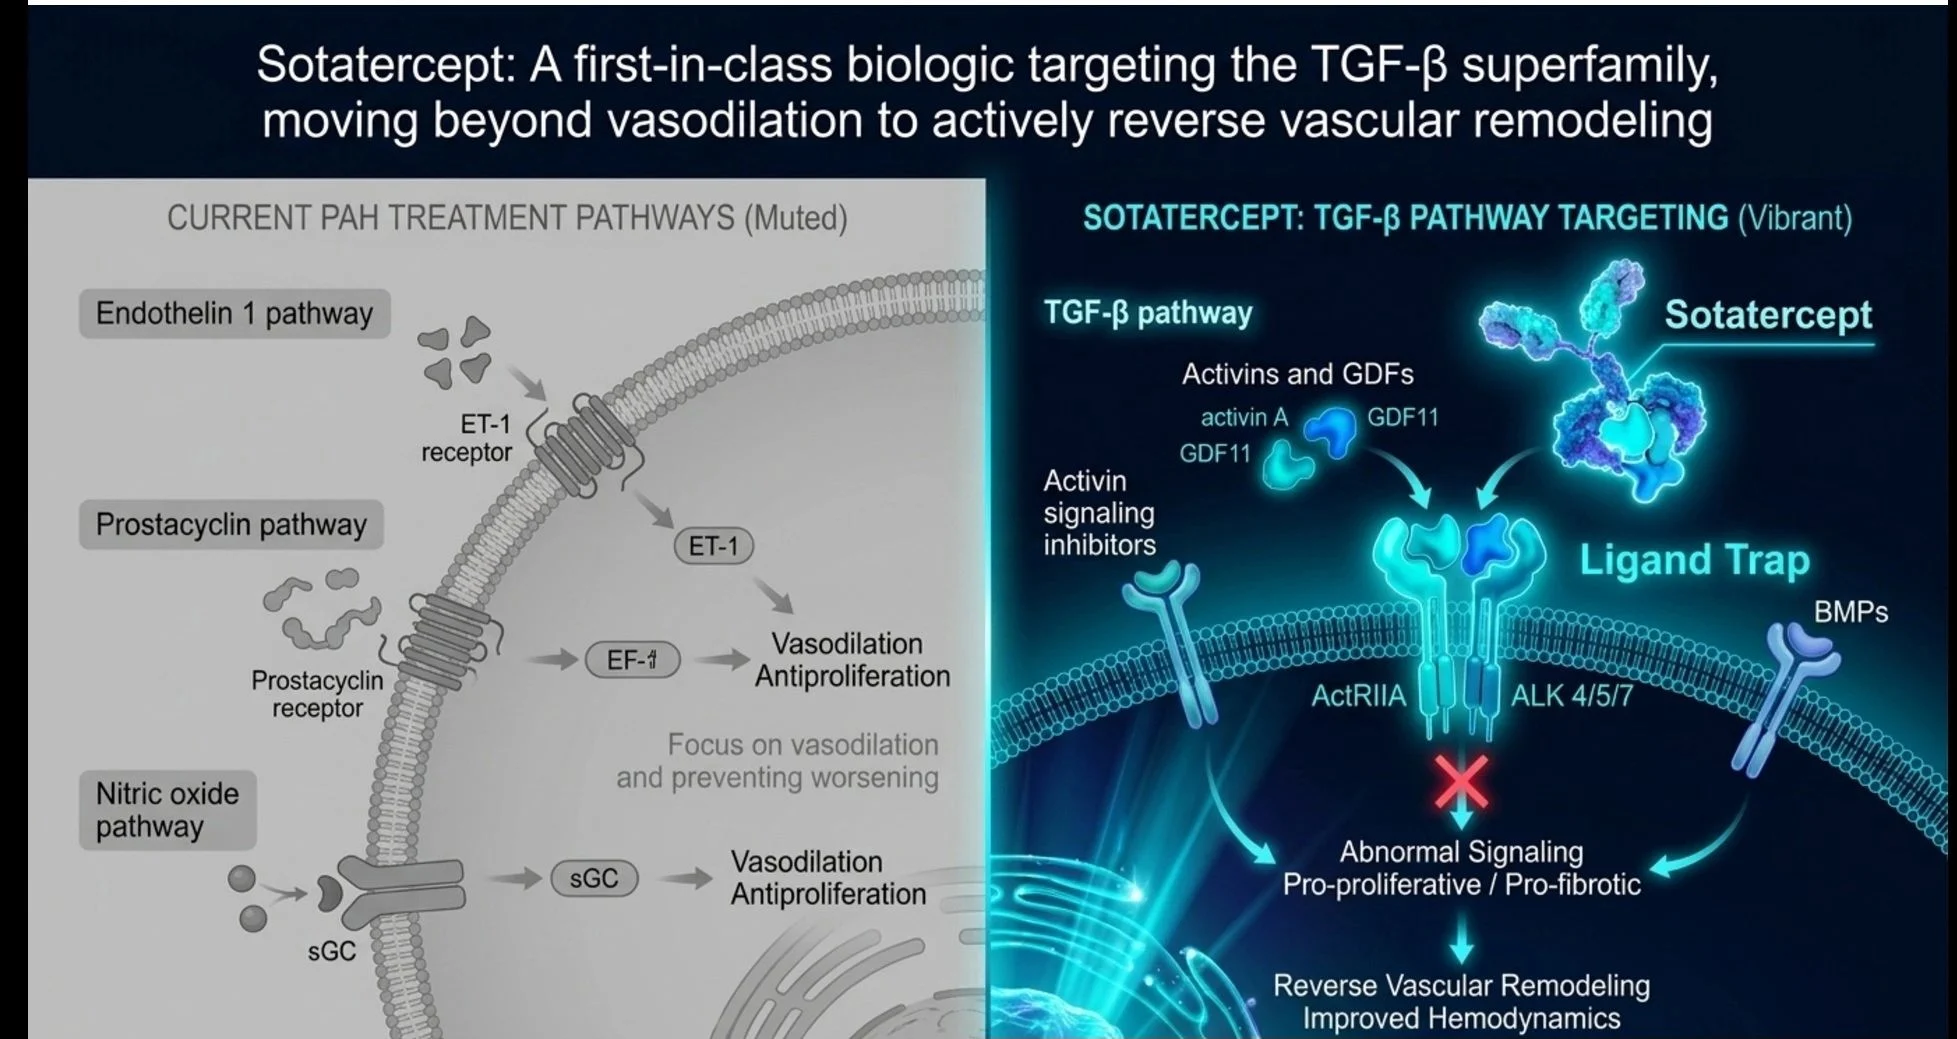
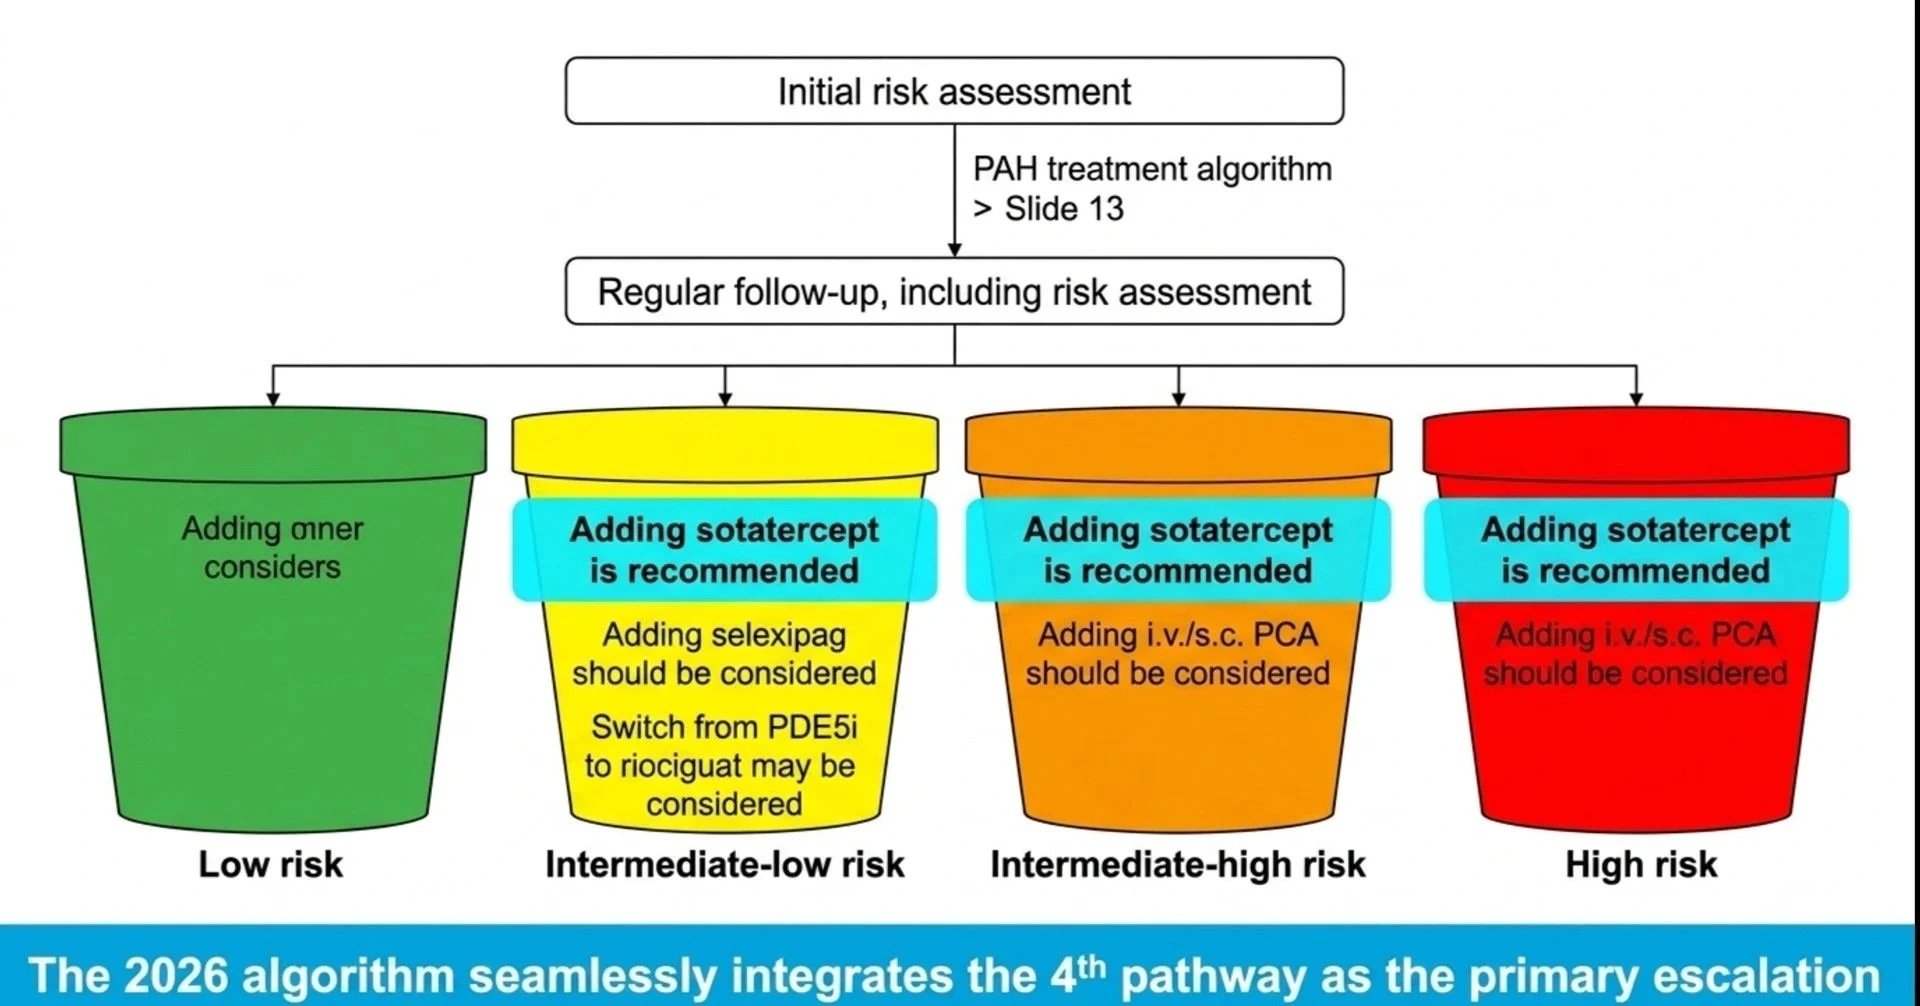
The most important change is the introduction of sotatercept, a new treatment targeting the activin-signalling pathway.
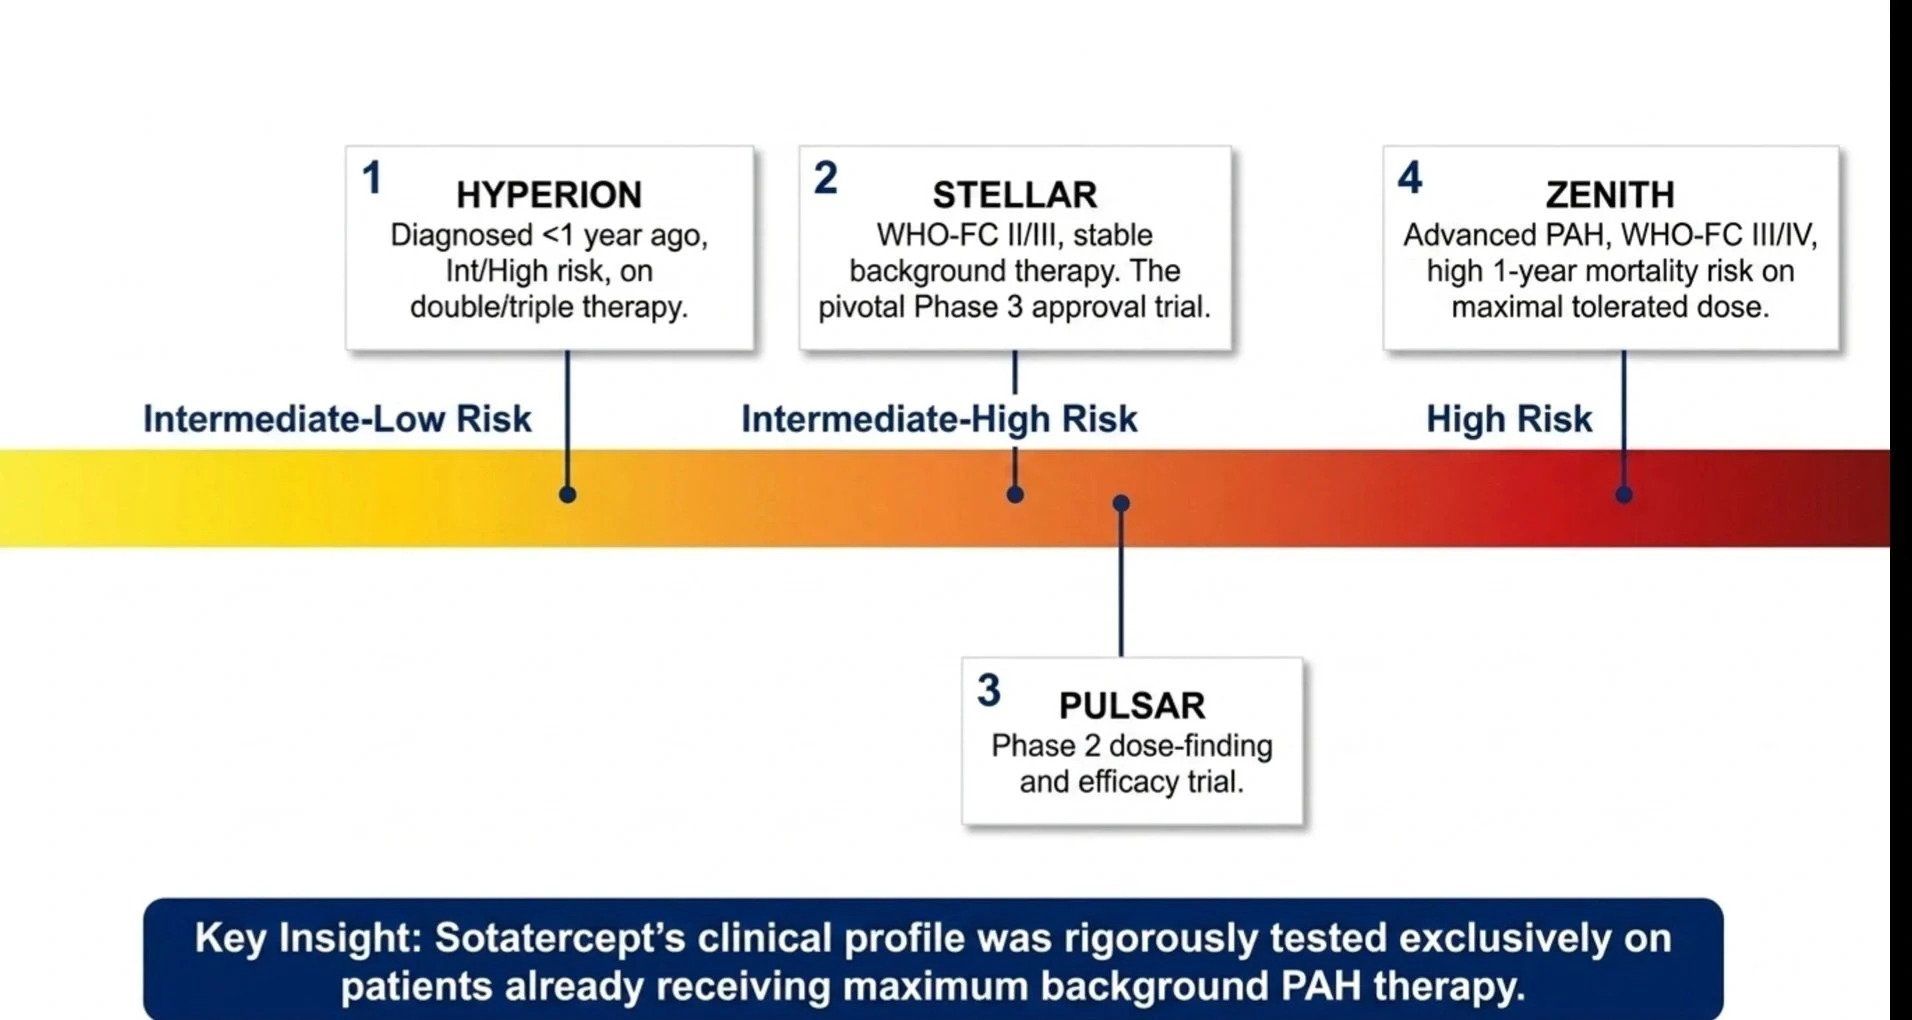
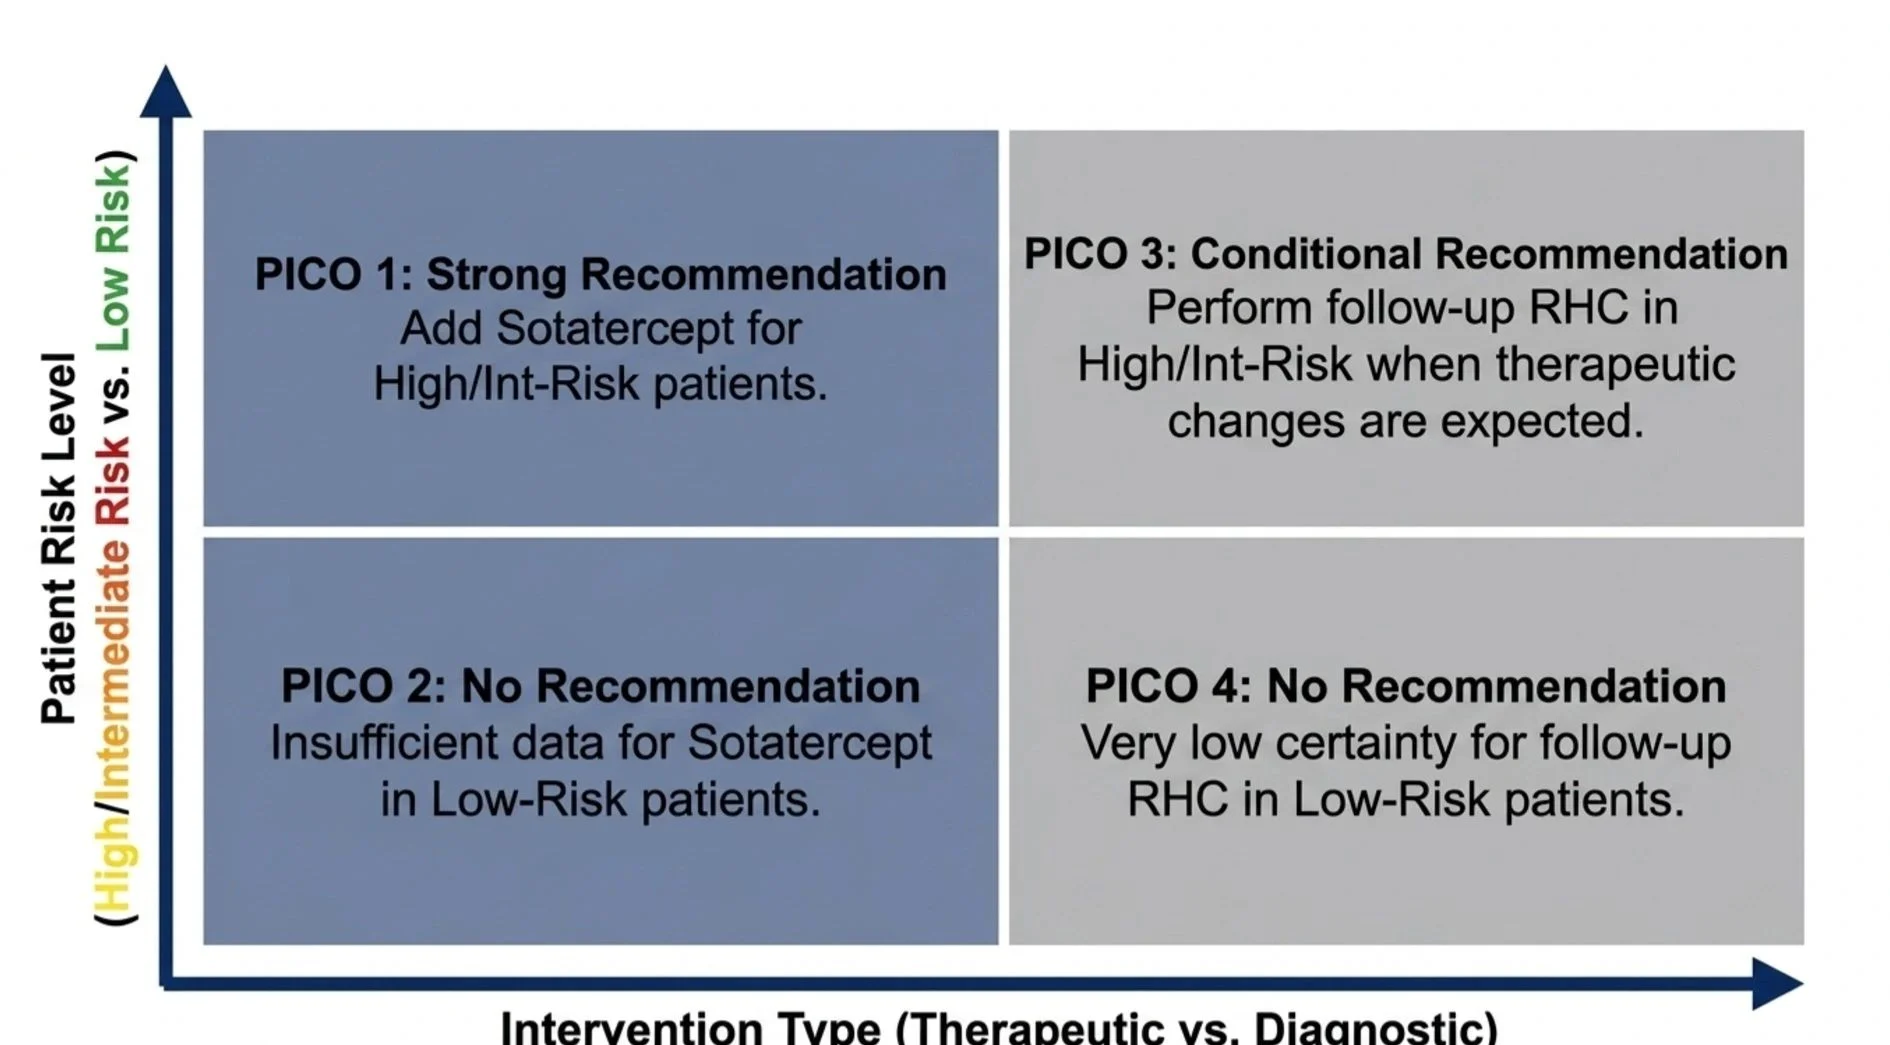
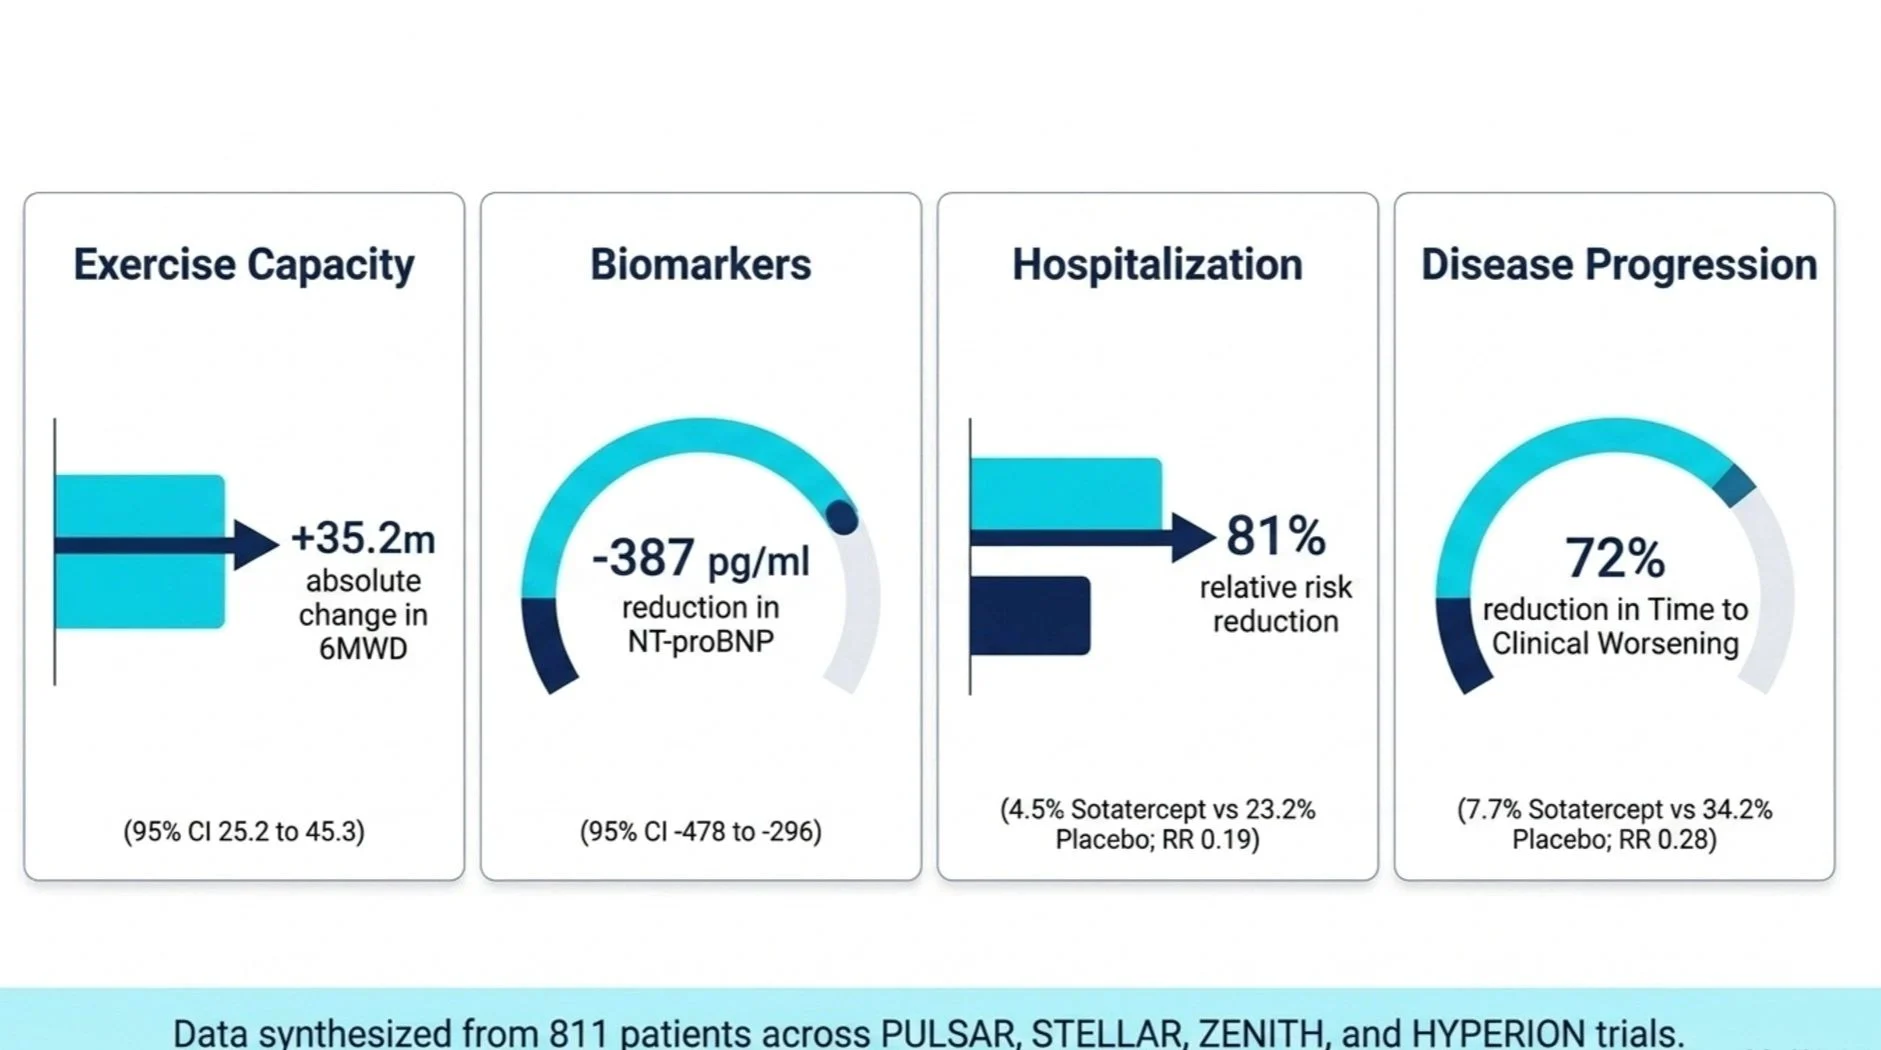
The 2026 ERS Task Force strongly recommends adding sotatercept to existing PAH therapy in patients who remain at intermediate-low, intermediate-high, or high risk during follow-up.
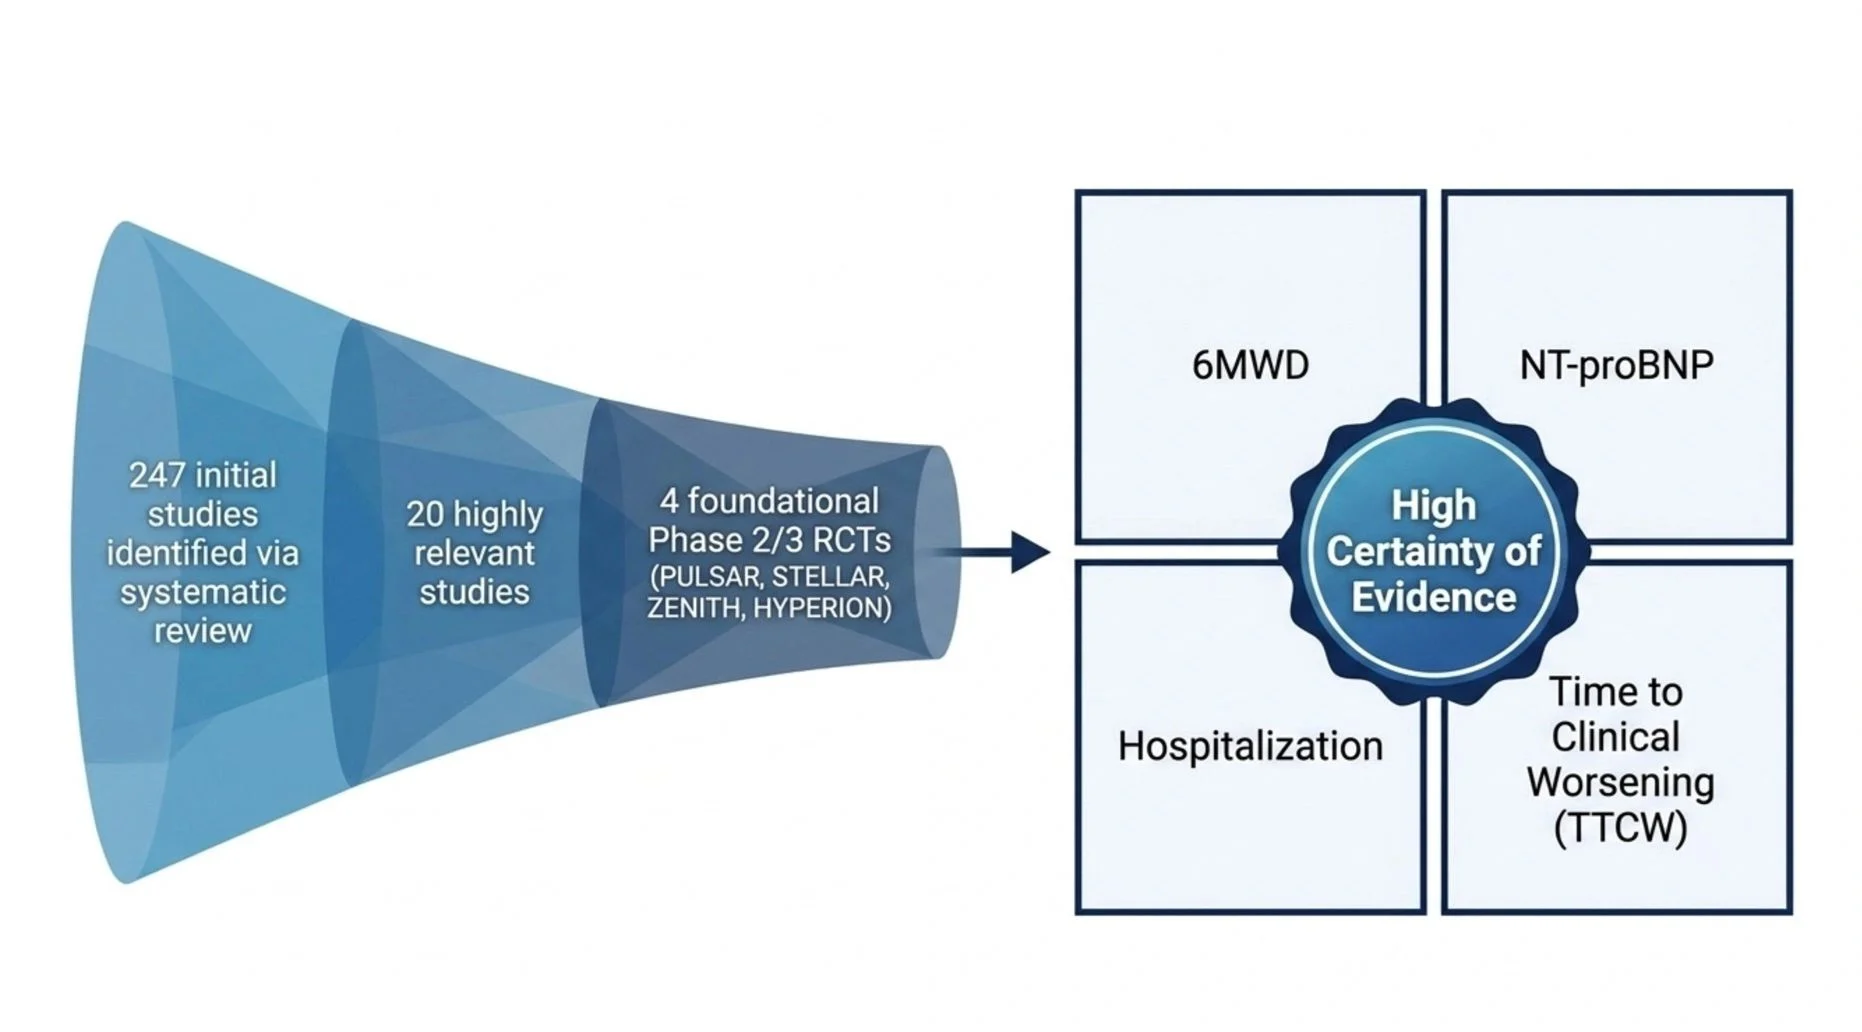
This recommendation is supported by high-certainty evidence from randomized trials.
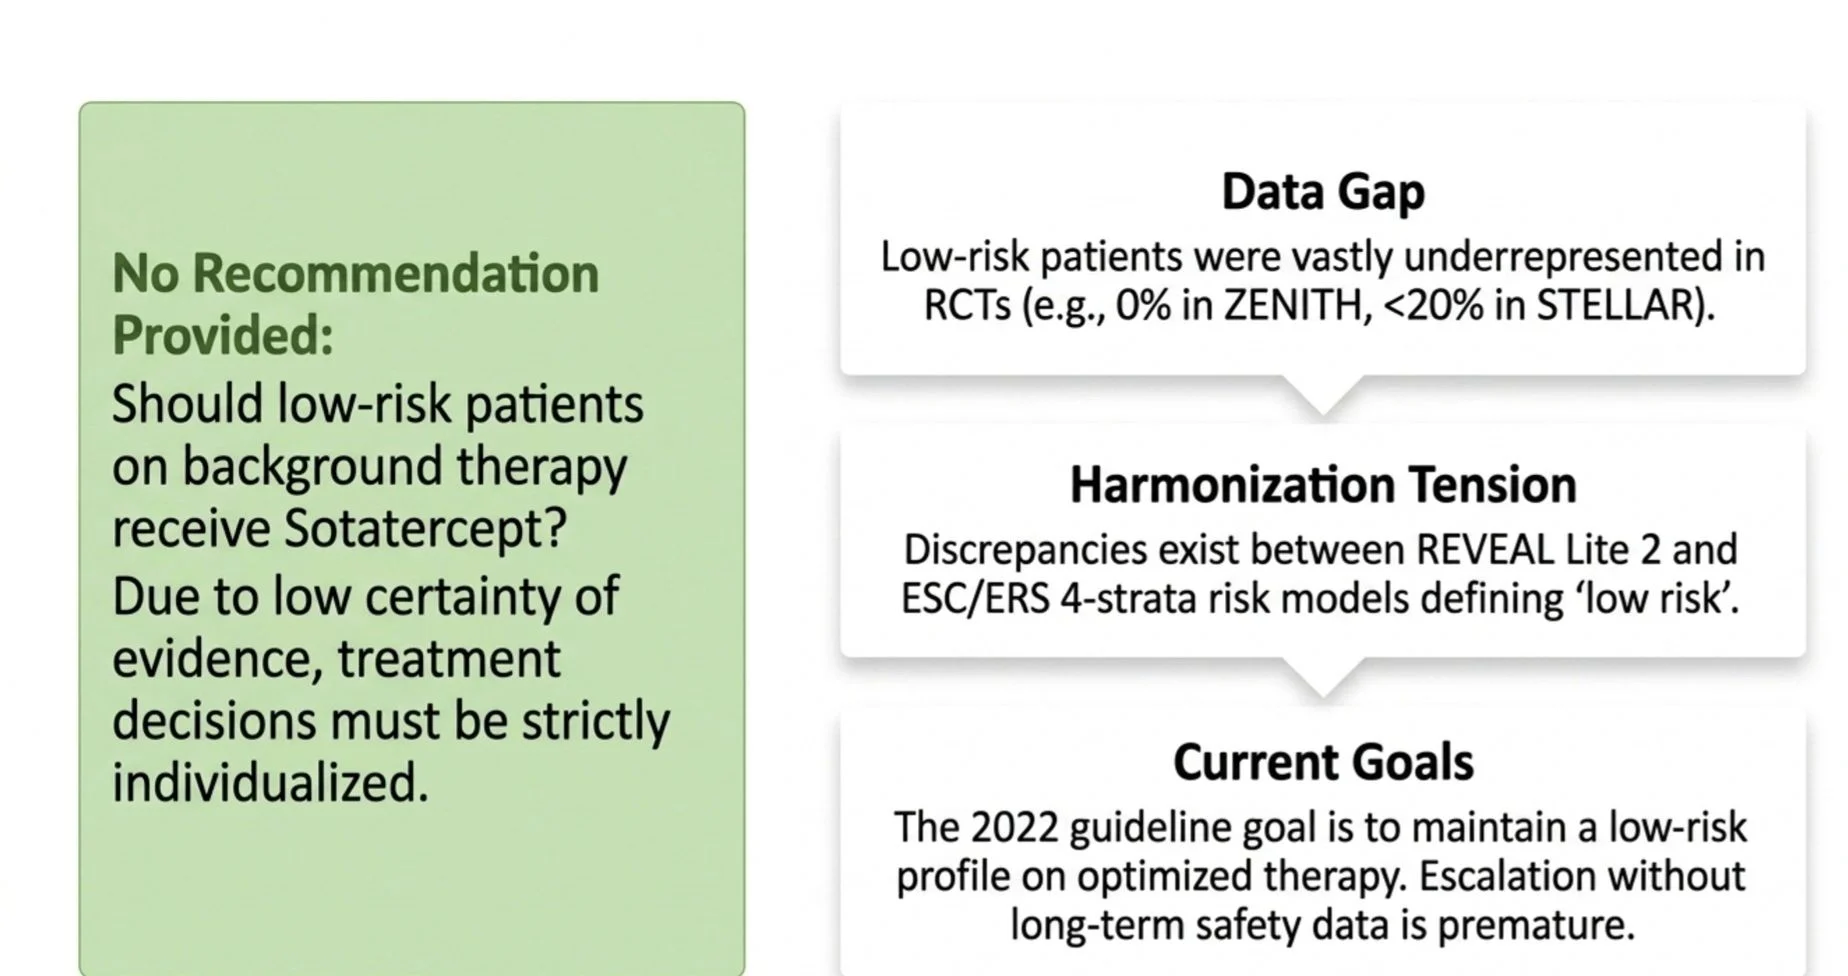
However, the paper does not recommend routine sotatercept for patients who are already at low risk because these patients were underrepresented in clinical trials.
It also does not recommend sotatercept as initial treatment in newly diagnosed, treatment-naive patients because sufficient evidence is not yet available.
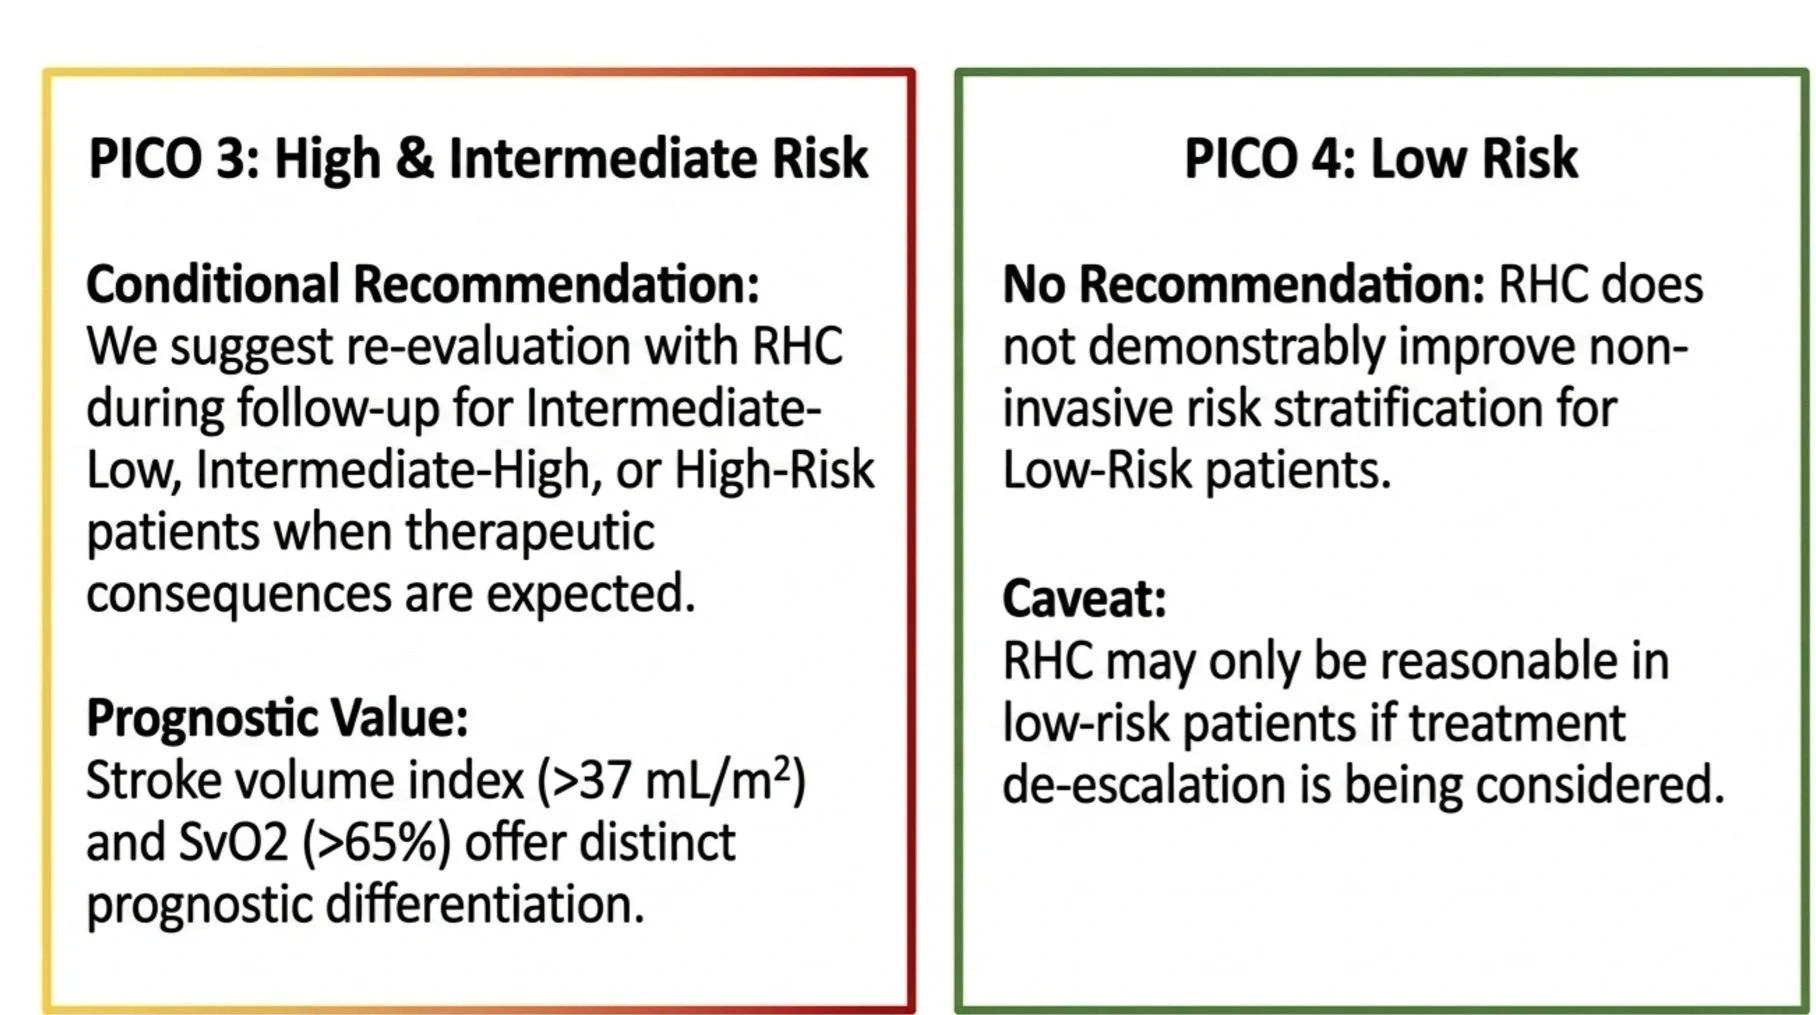
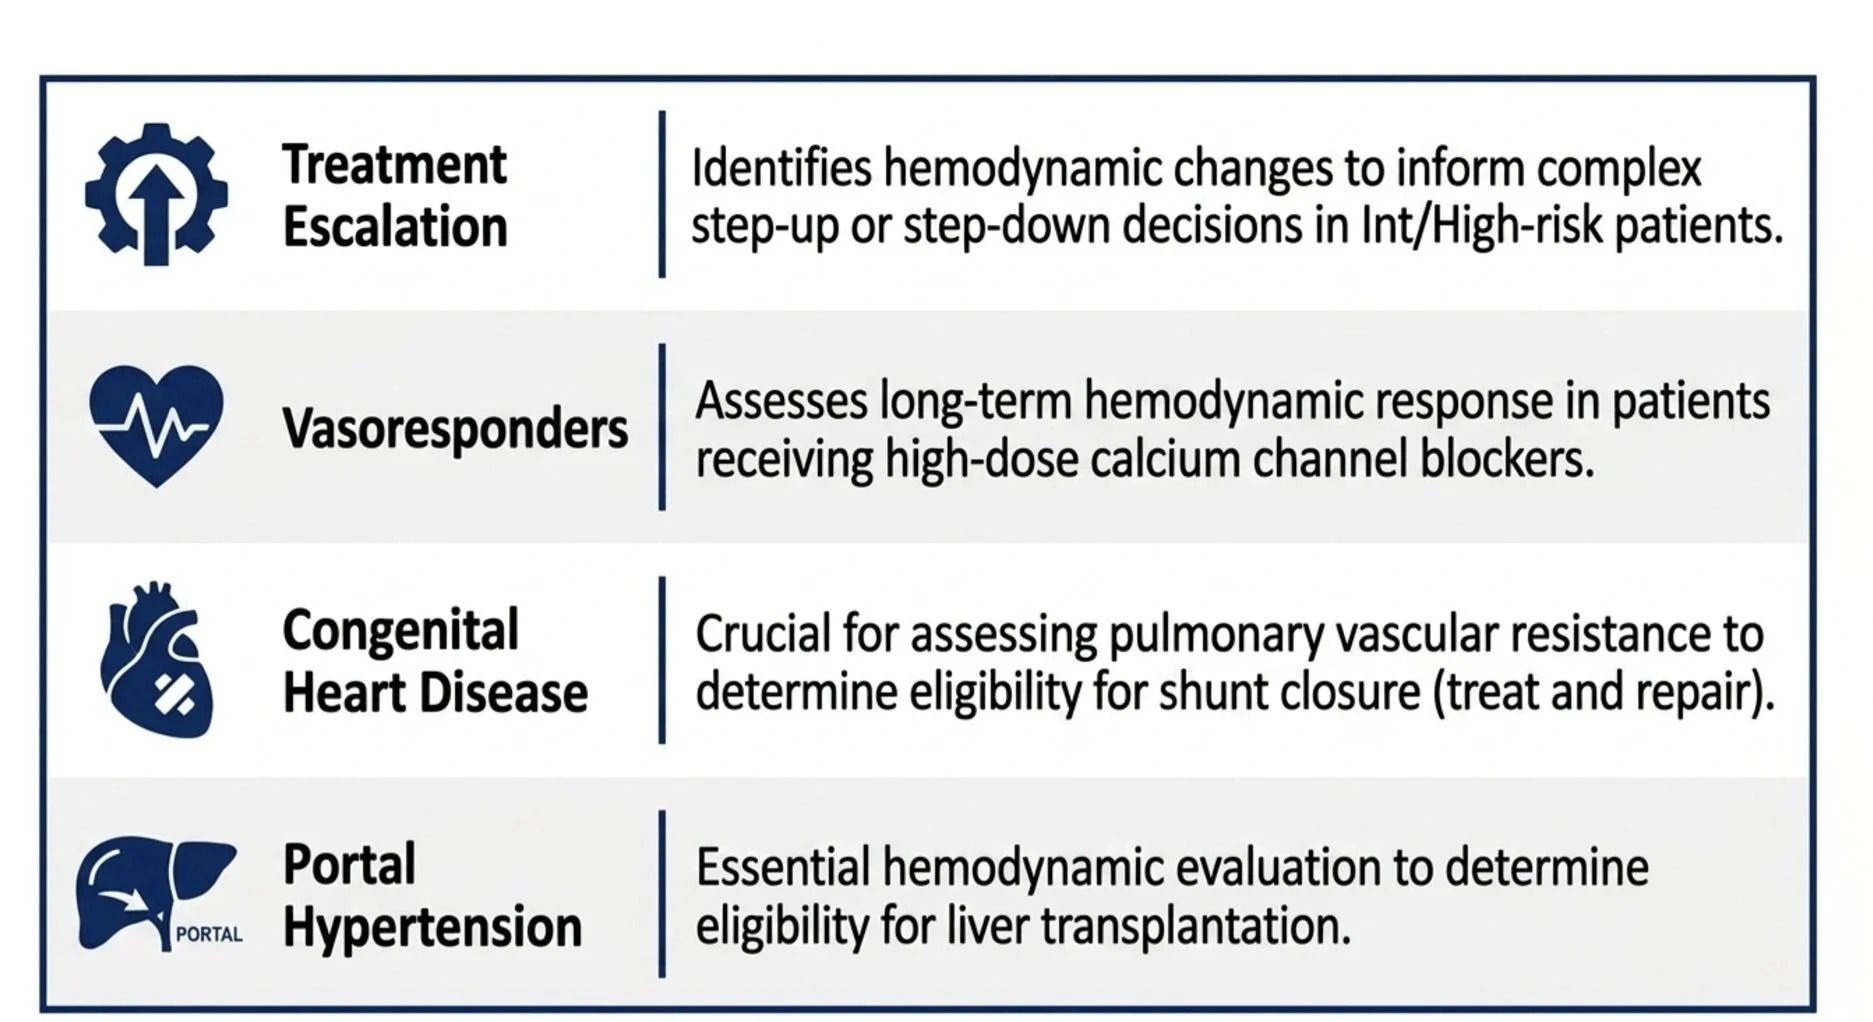
The paper also provides more specific guidance about follow-up right-heart catheterization (RHC) .
The 2022 guideline acknowledged the prognostic value of RHC but did not establish when it should routinely be performed.
The 2026 update suggests RHC in intermediate-low, intermediate-high, or high-risk patients when the results are expected to influence treatment decisions.
This recommendation is conditional and based on very-low-certainty evidence.
Routine RHC is not recommended for every low-risk patient.
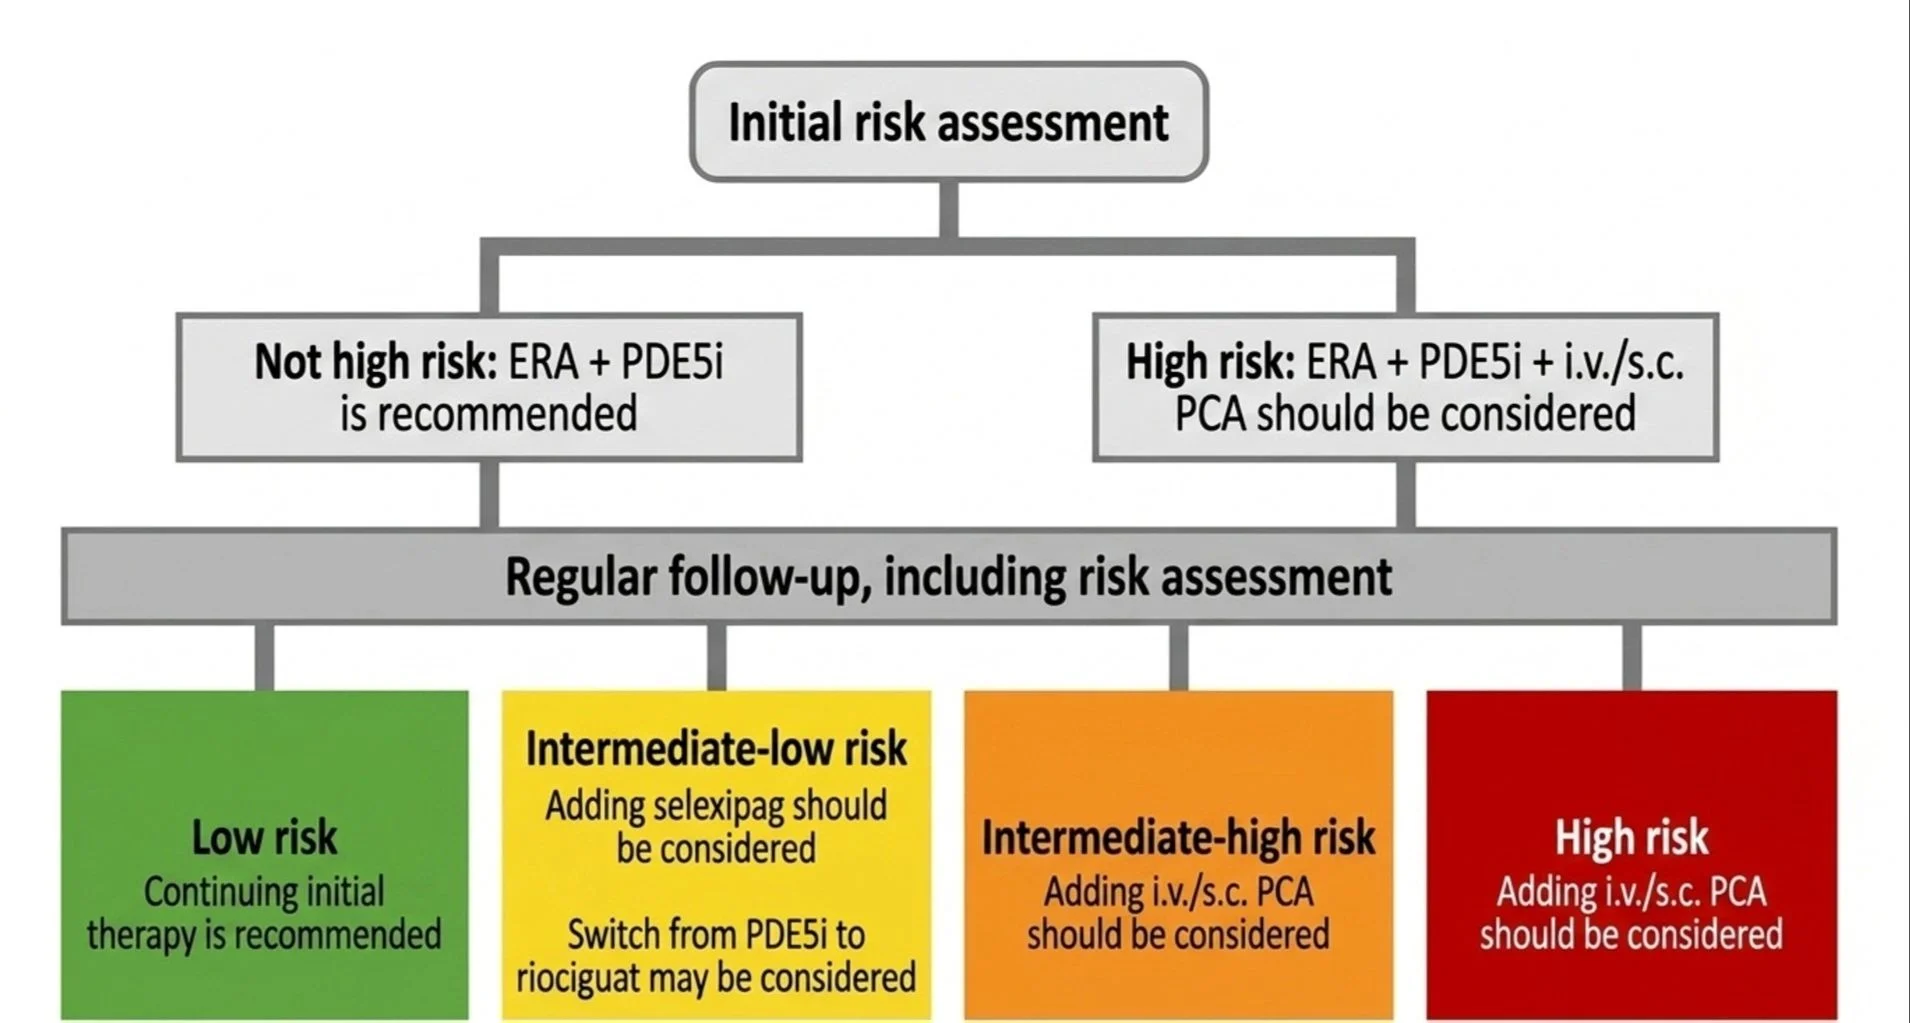
Importantly, the 2026 update retains the main principles of the 2022 guideline: risk-based treatment, the goal of achieving and maintaining low risk, initial combination therapy for suitable patients, timely use of parenteral prostacyclin in high-risk disease, and consideration of lung transplantation when appropriate.
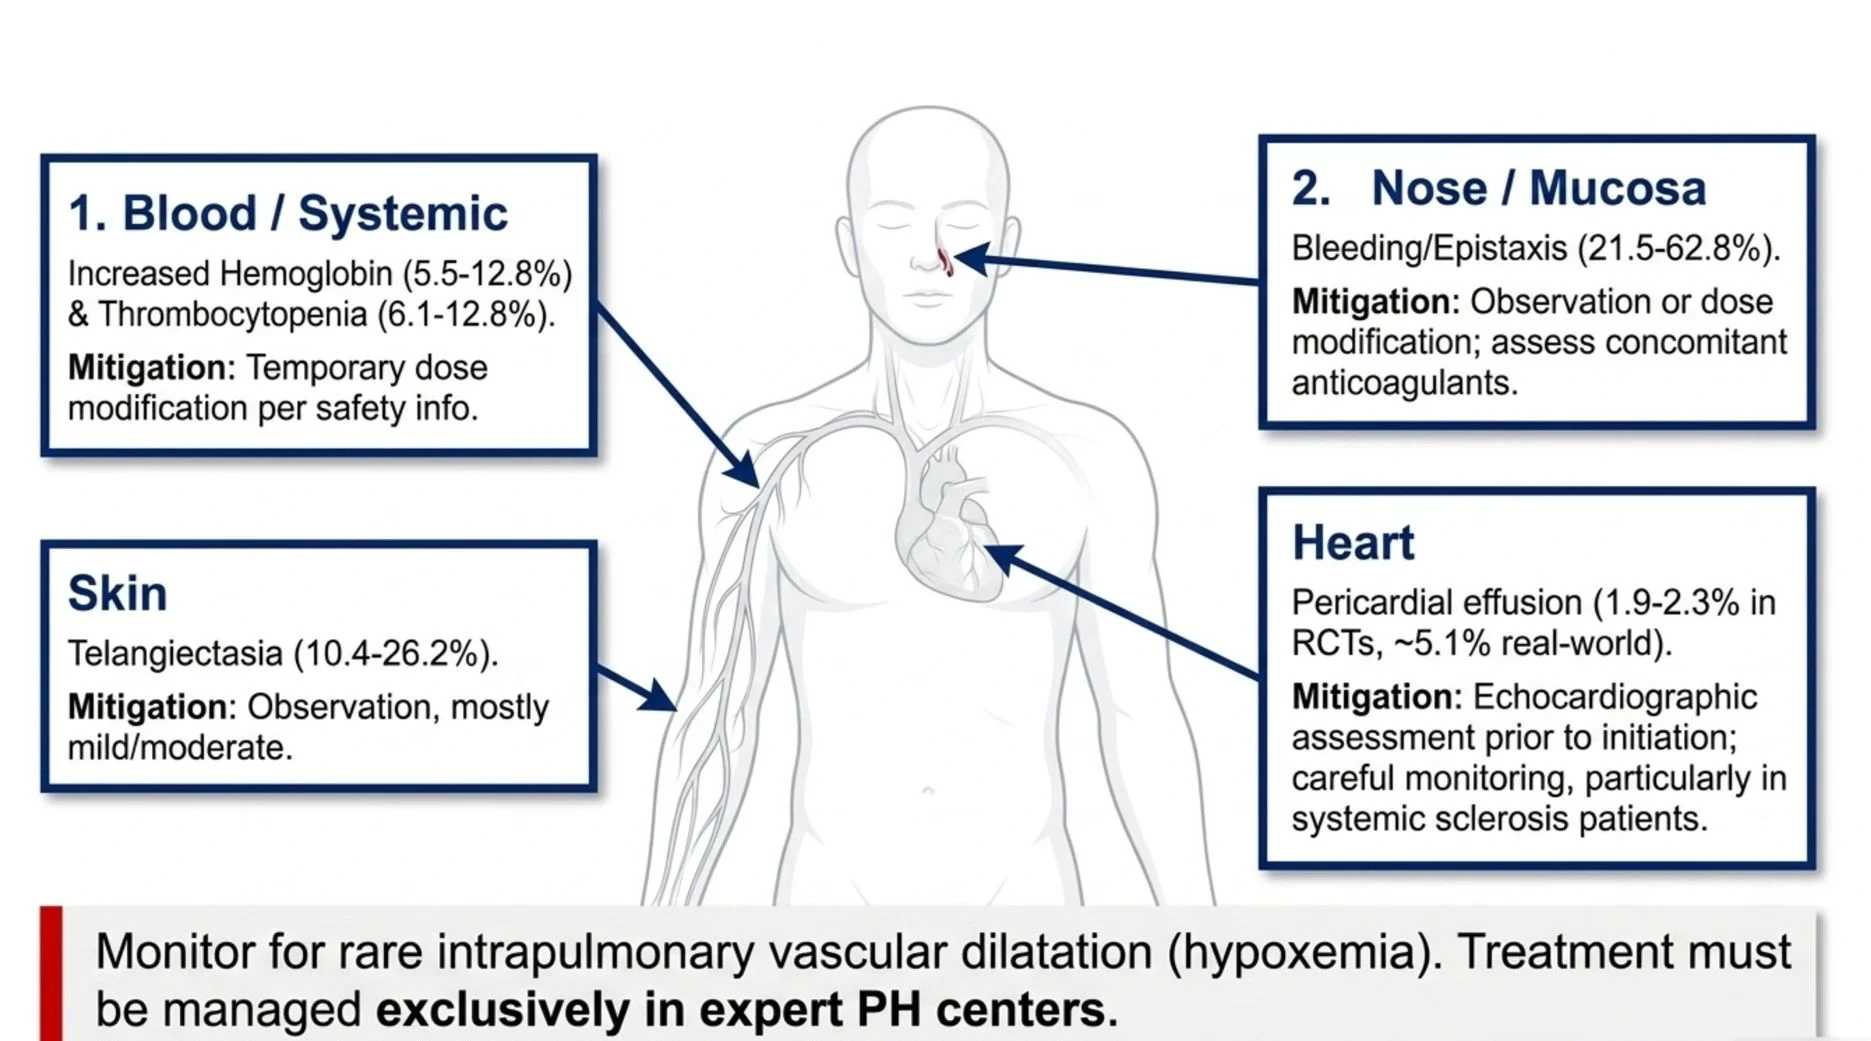
In my opinion this is a valuable and clinically relevant update because it incorporates sotatercept into modern PAH management while remaining cautious about its limitations and safety.
I consider the recommendation to use sotatercept in persistently higher-risk patients reasonable, but it should not delay prostacyclin therapy or specialist referral.
The cautious approach to low-risk patients and follow-up RHC is appropriate until stronger long-term evidence becomes available.”

Stay updated with Hemostasis Today.

-
Nov 2, 2026, 22:01Sakditad Saowapa: Anticoagulant Pharmacology and the Pursuit of Effective Therapy With Less Bleeding
-
Nov 2, 2026, 21:55Lucio D’Anna: Can Inflammatory Biomarkers Identify Residual Risk in Atrial Fibrillation?
-
Nov 2, 2026, 21:54Dawood Findakly: VTE Prophylaxis during Pregnancy
-
Nov 2, 2026, 21:52N. Mariana S. Vasquez: Five Rules That Help Identify the Cause of Hemolytic Anemia
-
Nov 2, 2026, 21:52Rob Maloney: Working Together to Strengthen Bleeding Disorders Care in the Dominican Republic
-
Nov 2, 2026, 18:08Jonathan Penm: Antithrombotic Stewardship Optimizes VTE Prophylaxis in ICU Patients
-
Nov 2, 2026, 14:48Heghine Khachatryan: Vitamin B12 Replacement Choosing the Right Route for Each Patient
-
Nov 2, 2026, 14:28Anastasia Conti: ASH Global Research Award Backs New Directions in AML Research
-
Nov 2, 2026, 14:22Sara Zalghout: Linking Bacterial Virulence to NETosis and Thromboinflammation