


Edward Lee Carter: Every Antithrombotic Regimen Needs an Exit Strategy – Lessons from the OPTIMA-AF Trial
Edward Lee Carter, Clinical Pharmacist Practitioner at U.S. Department of Veterans Affairs, shared a post on LinkedIn:
“Most antithrombotic regimens have a start date.
Far fewer have a documented stop date.
That may be one of the biggest opportunities we have to improve medication safety.
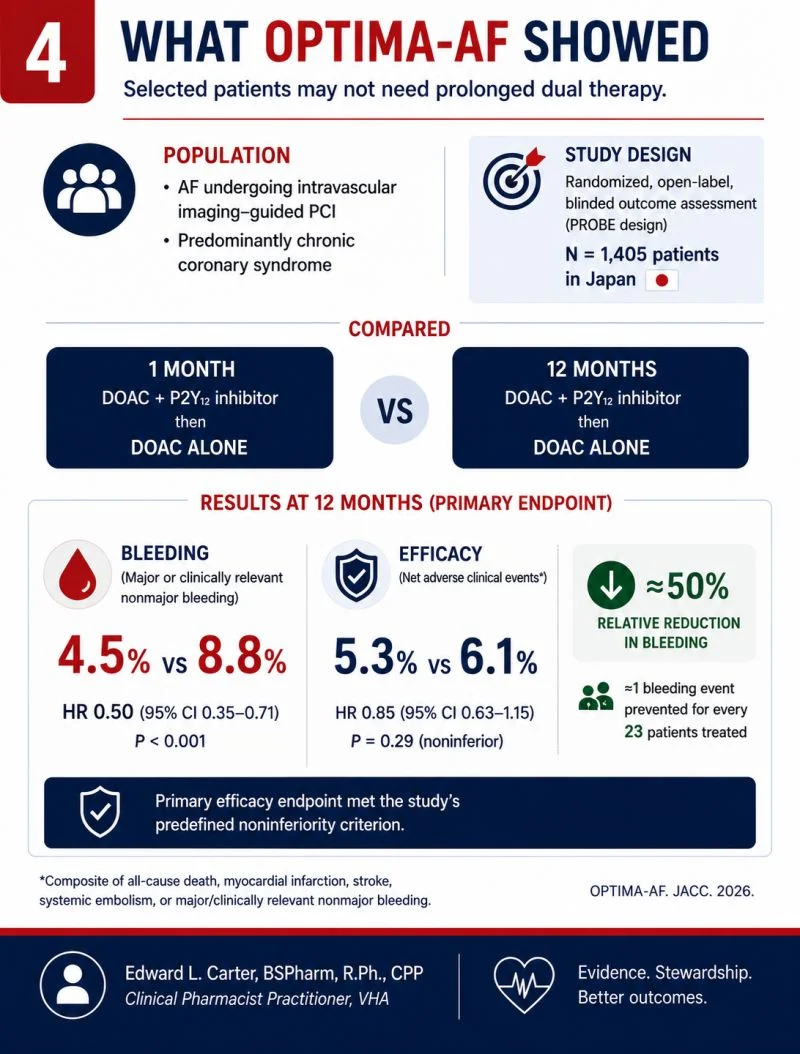
The OPTIMA-AF trial asked an important question:
After PCI in patients with atrial fibrillation, how long does dual therapy really need to continue?
In a carefully selected population undergoing imaging-guided PCI, 1 month of a DOAC plus a P2Y₁₂ inhibitor, followed by DOAC alone, significantly reduced clinically relevant bleeding while meeting the study’s predefined noninferiority criterion for ischemic outcomes.
But here’s what I found even more interesting…
OPTIMA-AF isn’t simply another PCI trial.
It’s another reminder that antithrombotic stewardship doesn’t end when therapy begins.
As clinicians, we routinely ask:
- Which anticoagulant?
- Which P2Y₁₂ inhibitor?
- Which dose?
Maybe we should spend just as much time asking:
- Does every antithrombotic still have a clear indication?
- Has the patient’s bleeding risk changed?
- Has the ischemic benefit diminished?
- Who owns the stop date?
The trial also deserves appropriate caution.
Its patients were predominantly those with stable coronary disease, all underwent intravascular imaging-guided PCI, and the study was conducted entirely in Japan. These results should inform practice—but they should not be interpreted as meaning every patient can safely discontinue a P2Y₁₂ inhibitor after 30 days.
Clinical judgment remains essential.
For me, the broader lesson is this:
Every additional day of combination antithrombotic therapy should be an intentional decision—not simply the default.
That may be the next frontier of antithrombotic stewardship.
- Swipe through the carousel for a summary of the trial, its limitations, and a practical stewardship framework.
How does your institution approach planned de-escalation of antithrombotic therapy after PCI? Is the anticipated stop date documented when the patient leaves the hospital?”

Other posts featuring Edward Lee Carter on Hemostasis Today.





-
Sep 20, 2026, 03:22The Voices of People Living With Bleeding Disorders – EHC
-
Sep 20, 2026, 01:18Sebastian Mafeld: Has 2026 Changed How We Treat Pulmonary Embolism?
-
Sep 20, 2026, 01:16Pall T. Onundarson: DOACs – Monitoring, Tailoring Dose and Identifying Problems
-
Sep 20, 2026, 01:15Thierry Fumeaux: From Efficacy to Effectiveness – The Value of Real-World Evidence
-
Sep 20, 2026, 01:14Said El Shamieh: VEGFA Genetic Variants and Bleeding Risk During Warfarin Therapy
-
Sep 20, 2026, 01:04Omar Danoun: Levetiracetam May Increase Thromboembolic Risk With DOACs
-
Sep 20, 2026, 01:02Mohamed Abo-Aly: Which Antiseizure Medication is Safest for Patients on DOACs?
-
Sep 20, 2026, 00:58Hamza Rafiq: How Does a Deep Vein Thrombosis Become a PE?
-
Sep 20, 2026, 00:50A Shared Platelet Factor 4–Targeted Immune Mechanism in Adenovirus Infection – NEJM